Read this tutorial on the use of point of care ultrasonography (POCUS) for pediatric intussusception. Then test your skills on the ALiEMU course page to receive your PEM POCUS badge worth 2 hours of ALiEMU course credit.
PATIENT CASE
Johnny is a 2-year-old boy who comes into the emergency department for abdominal pain for the last day. His parents are concerned that he has been having intermittent abdominal pain and has seemed very tired all day. Parents deny bloody stool.
On arrival, his vital signs are:
| Vital Sign | Finding |
|---|---|
| Temperature | 36.9C |
| Heart rate | 110 bpm |
| Blood pressure | 97/50 |
| Respiratory rate | 22 |
| Oxygen saturation (room air) | 99% |
He is tired appearing, and his abdominal exam is soft but diffusely tender. Given his intermittent abdominal pain, you decide to perform an intussusception point of care ultrasound (POCUS) exam.
ULTRASOUND TECHNIQUE
Intussusception is when one part of the bowel telescopes, or gets stuck, in another part of the bowel. Typically intussusception refers to ileocolic intussusception where the ileum becomes stuck in the colon. To perform the ultrasound, start in the right lower quadrant and trace the colon. See below for a step-by-step technique.

Technique
- The patient should be positioned supine.
- To aid in comforting the child, the child can be positioned supine in the parent’s lap while undergoing the scan. Having the parent or another provider offer a toy, book, or phone/tablet to distract the child during the scan can also help ease anxiety.
- Begin in the right lower quadrant (RLQ), using a high frequency linear probe with the probe marker to patient’s right.
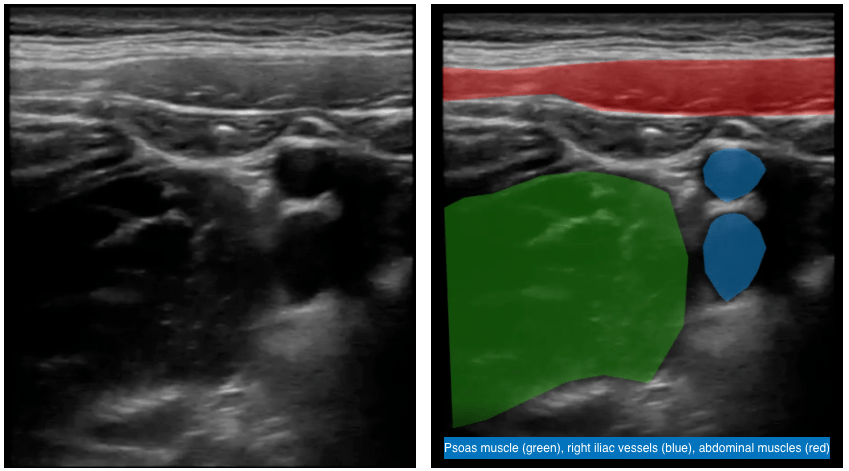
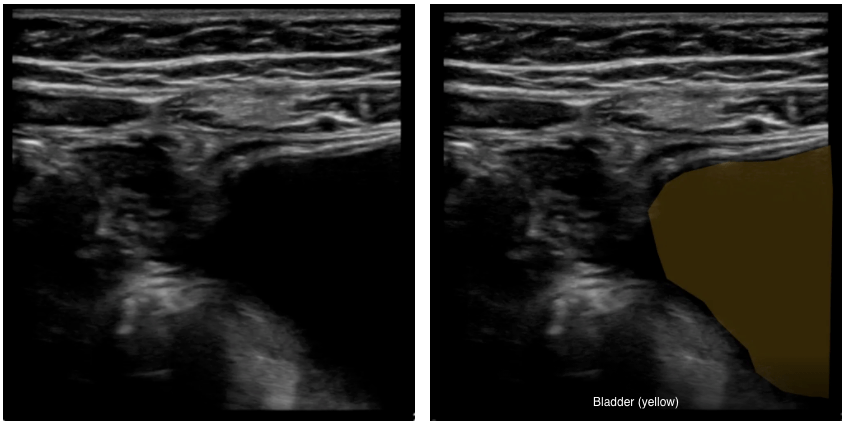
- First, identify the anatomical landmarks in the RLQ (see ultrasound images below):
- Psoas muscle (green) laterally
- Right iliac vessels (blue)
- Abdominal muscles (red)
- Bladder (yellow) medially
Ultrasound image: Anterior Abdomen (RLQ) View
Ultrasound Image: Anterior Abdomen RLQ (More Medial) View
- Perform graded compression, with slow steady pressure to displace bowel gas
- Follow the colon from the RLQ to right upper quadrant (RUQ) until the liver (purple) and gallbladder are identified
Ultrasound Image: Anterior Abdomen (RUQ) View

- Rotate the probe marker to patient’s head and scan the entire length of the transverse colon.
- Rotate the probe marker back to patient’s right and scan the entire length of the descending colon, making sure to scan all four quadrants.
- Save representative video clips and still images of each quadrant.
- If an intussusception is found, measure its diameter in transverse view and note in which quadrant(s) it is found.
- At the end of scan, if you have found an intussusception, re-image the abdomen to make sure it was not transient.
- The provider should maintain awareness of the patient’s comfort throughout the scan.
INTUSSUSCEPTION CLASSIC FINDINGS
Normal (no intussusception)
Abnormal findings
- Look for findings of a sandwich sign (or pseudo-kidney sign) in the longitudinal view and target sign (or donut sign) in the transverse view.
- If visualized, measure the diameter of the intussusception in short axis (transverse) and note which in which quadrant(s) it is located.
Sandwich
Target Sign

Additional Anterior Abdominal Ultrasound Videos
Pro Tip
It can be difficult to distinguish intussusception of the small bowel-small bowel (i.e., when the ileum or part of the small bowel telescopes into itself) versus ileocolic (i.e., when the ileum becomes telescopes into the colon). The former often does not require a procedure for reduction, while the latter typically does. If the target sign diameter is <2 cm and transient, a small bowel-small bowel intussusception should be suspected. The length of the intussusception, or how many quadrants are involved, can also be measured for an idea of how much bowel is involved.
Small bowel-small bowel intussusception
Ileo-colic intussusception
FACTS and LITERATURE REVIEW
Mimickers of Intussusception
There are additional pathologies that can be mistaken for intussusception such as an intussuscepted appendix, appendicitis surrounded by abscess, and Meckel’s diverticulum, which are beyond the scope of this course. Any concerning finding for intussusception should be followed by a confirmatory study by the radiology department.
Benefits of intussusception POCUS scans
There have been several studies examining point-of-care ultrasonography (POCUS) for intussusception, which have shown excellent test characteristics and a decreased length of stay when using POCUS. POCUS also has no radiation exposure and may further help reduce morbidity by reducing delays in diagnosis of intussusception [1].
POCUS performed by PEM physicians has demonstrated a high level of accuracy in diagnostic agreement with radiologist-performed ultrasounds. For example, in a study by Arroyo et al., POCUS agreement with radiologist-performed ultrasounds occurred in 97 of 100 cases [1]. There is also research comparing positive ultrasound diagnosis (including POCUS and radiologist-performed ultrasound) of intussusception to confirmatory surgical or contrast enema, as exhibited by the table below.
Below is a table of test characteristics of POCUS for intussusception.
| Publication | Methodology | Sensitivity | Specificity |
|---|---|---|---|
| Riera et al. (2012) [2] | Prospective study of 82 patients who underwent POCUS by pediatric emergency medicine (PEM) providers. The gold standard was a comprehensive radiology ultrasound. | 85% | 97% |
| Trigylidas et al. (2019) [3] | Retrospective study of 102 POCUS exams in 101 patients by PEM providers. The gold standard was pediatric radiologist confirmation by review of the POCUS images, a radiology department ultrasound, or an air enema. | 96.0% | 92.6% |
| Lee et al. (2020) [4] | This retrospective study included 575 scans from 549 patients aged 1 month to 6 years with clinically suspected ileocolic intussusception, who underwent POCUS performed by PEM physicians of a tertiary hospital. The gold standard for comparison was radiologist-performed ultrasound. | 100% | 95.6% |
| Bergmann et al. (2021) [5] | This prospective study of 256 children across 17 sites (35 PEM physicians with experience/extra training in POCUS) compared POCUS and radiologist-performed ultrasound using a gold standard of clinically important intussusception which was defined as an intussusception that required radiographic or surgical reduction during or within 7 days of the incident ED visit. | 96.6% | 98% |
| Tonson la Tour et al. (2021) [6] | This prospective study included 131 children evaluated by POCUS, of whom 45 (34%) had an intussusception. Twenty-four PEM physicians with various levels of training performed POCUS and were able to identify 39 of 45 intussusception cases. PEM-performed POCUS was then compared to the gold standard, radiologist-performed ultrasound. Interestingly, diagnostic accuracy did not differ significantly between novice and experienced sonographers. | 87% | 97% |
| Lin-Martore et al. (2022) [7] | This systematic review and meta-analysis of diagnostic accuracy of POCUS for intussusception included 2400 patients and 11 studies. The POCUS evaluation of the lesion was performed by an adult or pediatric emergency physician. Each study consisted of a gold standard test including radiologist-performed ultrasonography, other radiology diagnostic imaging, air enema, or patient follow-up. | 95.1% | 98.1% |
| Rahmani et al. (2023) [8] | This meta-analysis included 37 studies to calculate the pooled sensitivity and specificity of ultrasound diagnosis of intussusception. The studies included used POCUS results from EM physicians and residents, sonography technicians, and one used a PEM physician certified in pediatric gastroenterology. It also included radiology-performed ultrasound. Each study consisted of comparison to a gold standard including radiologist-performed ultrasound, clinical follow-up, surgical report, and air or barium enema. | 96% | 97% |
| Alsabri et al. (2026) [9] | This meta-analysis includes a total of 44 studies (prospective and retrospective cohort studies, cross-sectional studies, and case-control studies) for pooled sensitivity and specificity of ultrasound for diagnosing intussusception. It includes POCUS from PEM physicians and radiology ultrasounds. The gold standard of confirmation included surgical findings, clinical follow-up, and contrast enema (barium and air). | 96.3% | 95.7% |
In terms of Emergency Department (ED) length of stay (LOS), Kim et al. (2020) reported that after the introduction of an intussusception POCUS scanning protocol for PEM physicians to implement in the ED, the LOS decreased by more than 200 minutes [10]. An additional study has shown that a POCUS-first pathway can be a way to expedite care for children with suspected intussusception in the ED, leading to reduced physician initial assessment to reduction time by an average of 69.9 min when compared to traditionally waiting for radiologist-performed ultrasound evaluation [11].
Differentiating small bowel-small bowel from ileocolic intussusception
In general, true ileocolic intussusceptions are:
- Found on the right side of the abdomen
- >2 cm in diameter
- Have mesenteric fat (which is white) and lymph nodes in the center
- Do not self-resolve
There have been studies looking at distinguishing small bowel-small bowel intussusception (SB-SBI) from ileocolic intussusception (ICI). Most of these, however, have been radiology-based rather than POCUS studies, making generalizability to the ED setting challenging. Thus, if there is a concern for an intussusception, a radiology ultrasound should be ordered.
In a small study of 27 patients, Wiersma et al. (2006) [12] found that SB-SBI had smaller mean diameters and shorter lengths than ICI. Consistent with these findings, a more recent study reported similar findings, with all ICI cases in the study having lesion diameters greater than 2 cm [13]. This study also suggested a difference in age distribution between the two intussusception lesions studied: patients with SB-SBI tended to be older and exhibited a wider age range, whereas the ICI group consisted predominantly of infants younger than 1 year [13].
| Study author and year | N (patients) | Age (mean or median) | Mean diameter | Mean length | Notes |
|---|---|---|---|---|---|
| Wiersma et al. (2006) [12] | SB-SBI: 10 ICI: 14 |
SB-SBI: 3.1 yr (mean) ICI: 1.9 yr (mean) |
SB-SBI: 1.5 cm ICI: 3.7 cm |
SB-SBI: 2.5 cm ICI: 8.2 cm |
SB-SBI: Lesions were located throughout the abdomen (6 paraumbilical, 2 RUQ, 2 RLQ, 1 LLQ). All ICI lesions were located on the right side of the abdomen. |
| Park et al. (2019) [13] | SB-SBI: 21 ICI: 16 |
SB-SBI: 54 mo (median) ICI: 8 mo (median) |
SB-SBI: 1.68 cm ICI: 2.74 cm |
Not reported | SB-SBI was identified more frequently than ICI in this cohort when using POCUS screening tool, which may be due to rapid detection by POCUS and/or lower threshold for evaluating for intussusception. |
| Goel et al. (2020) [14] | SB-SBI: 21 ICI: 33 |
SB-SBI: 17.3 mo ICI: 22.2 mo |
SB-SBI: 2.13 cm ICI: 3.24 cm |
SB-SBI: 3.17 cm for obstructive cases and 1.93 cm for transient cases ICI: Not reported |
The team noted an optimal threshold of 2.5 cm to distinguish between transient and obstructive SB-SBIs. Lymph nodes were present in 18 (33.3%) out of 54 surgically confirmed cases, and all were ICI. |
Lioubashevsky et al. (2013) [15] evaluated a larger cohort of 174 patients and reported similar findings. In addition to assessing the inner fat core-to-outer wall thickness ratio, the authors examined the presence or absence of lymph nodes within the intussusception. These findings were supported by Zhang et al. (2021) [16], who identified lymph nodes in only one case of SB-SBI, compared with 56 cases (93%) of ICI. Zhang et al. also found that the fat core was visible on ultrasound in all cases of ICI but was absent in 16% of SB-SBI cases [16]. Similarly, Goel et al. reported an inner fat core-to-outer wall thickness ratio > 1 in all cases of ICI and < 1 in all cases of SB-SBI, further supporting the diagnostic utility of this sonographic feature [14].
These differences may be explained by the underlying anatomical and physiological characteristics of the involved bowel segments [14,15]. The mesentery associated with the ileocolic region contains greater amounts of adipose tissue and lymph nodes than the mesentery involved in SB-SBI [14-16]. This could explain why ileocolic intussusceptions tend to demonstrate greater lymph node and fat involvement, appearing as hyperechoic structures on ultrasound [15-17]. The increased proportion of mesenteric fat and lymphatic tissue may also contribute to the larger diameter of ICI lesions [14,16,17]. In contrast, the shorter length of SB-SBI lesions reported in previous studies may be attributable to active bowel peristalsis and the greater likelihood of spontaneous resolution in these cases [16,17].
Subramaniam et al. (2022) [18] looked at POCUS differentiating SB-SBI from ICI. Similar to above, they noted the predominant location of SB-SBI in the periumbilical or left abdomen compared with the right-sided predominance of ICI; the larger diameter of ICI, typically greater than 2.5 cm; the greater length of ICI, typically exceeding 3 cm; the presence of lymph nodes within ICI; the presence of peristalsis within SB-SBI; and the larger core-to-wall index associated with ICI [18].
While beyond the scope of this module, there is some evidence that POCUS may facilitate the treatment of intussusception in addition to its diagnostic utility. Zymerman et al. (2026) [19] reported a case series of 9 reductions with an 88.9% success rate for POCUS-guided hydrostatic reduction of ICI performed at the bedside by a pediatric emergency medicine physician. Similarly, Atia et al. (2026) [20] reported a retrospective chart review with 24 of 28 ICI (86%) successfully reduced when ICI was diagnosed using POCUS and bedside ultrasound-guided hydrostatic reduction was performed by a pediatric radiologist. This study also reported a mean time from admission to reduction of 126 minutes and a mean hospital length of stay of 407 minutes [20]. Together, these findings suggest that POCUS may serve not only as a reliable diagnostic tool for differentiating ICI from SB-SBI but also as a means of facilitating timely and effective bedside therapeutic intervention.
References [click to expand] +
- Arroyo AC, Zerzan J, Vazquez H et al. Diagnostic accuracy of point-of-care ultrasound for intussusception performed by pediatric emergency medicine physicians. J Emerg Med. 2021;60(5):626-632. doi:10.1016/j.jemermed.2020.11.030. PMID: 33483198.
- Riera A, Hsiao A, Langhan M, Goodman T, Chen L. Diagnosis of intussusception by physician novice sonographers in the emergency department. Ann Emerg Med. 2012;60(3):264-268. doi:10.1016/j.annemergmed.2012.02.007. PMID: 22424652.
- Trigylidas TE, Hegenbarth MA, Patel L, Kennedy C, O’Rourke K, Kelly JC. Pediatric emergency medicine point-of-care ultrasound for the diagnosis of intussusception. J Emerg Med. 2019;57(3):367-374. doi:10.1016/j.jemermed.2019.06.007. PMID: 31405782.
- Lee JY, Kim JH, Choi SJ, Lee JS, Ryu JM. Point-of-care ultrasound may be useful for detecting pediatric intussusception at an early stage. BMC Pediatr. 2020;20(1):155. doi:10.1186/s12887-020-02060-6. PMID: 32284038.
- Bergmann KR, Arroyo AC, Tessaro MO et al; P2Network. Diagnostic Accuracy of Point-of-Care Ultrasound for Intussusception: A Multicenter, Noninferiority Study of Paired Diagnostic Tests. Ann Emerg Med. 2021;78(5):606-615. doi:10.1016/j.annemergmed.2021.04.033. PMID: 34226072.
- Tonson la Tour A, Desjardins MP, Gravel J. Evaluation of bedside sonography performed by emergency physicians to detect intussusception in children in the emergency department. Acad Emerg Med. 2021;28(8):866-872. doi:10.1111/acem.14226. PMID: 33548161.
- Lin-Martore M, Firnberg MT, Kohn MA, Kornblith AE, Gottlieb M. Diagnostic accuracy of point-of-care ultrasonography for intussusception in children: A systematic review and meta-analysis. Am J Emerg Med. 2022;58:255-264. doi:10.1016/j.ajem.2022.06.025. PMID: 35749802.
- Rahmani E, Amani-Beni R, Hekmatnia Y et al. Diagnostic Accuracy of Ultrasonography for Detection of Intussusception in Children; a Systematic Review and Meta-Analysis. Arch Acad Emerg Med. 2023;11(1):e24. doi:10.22037/aaem.v11i1.1914. PMID: 36919137.
- Alsabri M, Rath S, Elkarargy MA et al. Accuracy of ultrasound for intussusception in pediatric emergency presentations: a systematic review and diagnostic meta-analysis. Int J Emerg Med. 2026;19(1):41. doi:10.1186/s12245-026-01134-z. PMID: 41667954.
- Kim JH, Lee JY, Kwon JH, Cho HR, Lee JS, Ryu JM. Point-of-Care Ultrasound Could Streamline the Emergency Department Workflow of Clinically Nonspecific Intussusception. Pediatr Emerg Care. 2020;36(2):e90-e95. doi:10.1097/PEC.0000000000001283. PMID: 28926507.
- Katz-Dana H, Harel-Sterling M, Vincent D, Dana E, Navarro OM, McLean LJ. A POCUS-first pathway to streamline care for children with suspected ileocolic intussusception. CJEM. 2024;26(4):235-243. doi:10.1007/s43678-024-00673-9. PMID: 38538954.
- Wiersma F, Allema JH, Holscher HC. Ileoileal intussusception in children: ultrasonographic differentiation from ileocolic intussusception. Pediatr Radiol. 2006;36(11):1177-1181. doi:10.1007/s00247-006-0311-2. PMID: 17019589.
- Park BL, Rabiner JE, Tsung JW. Point-of-care ultrasound diagnosis of small bowel-small bowel vs ileocolic intussusception. Am J Emerg Med. 2019;37(9):1746-1750. doi:10.1016/j.ajem.2019.06.024. PMID: 31257125.
- Goel I, Anand R, Choudhury SR, Agarwal S. Evolving Concepts in Ultrasonography of Pediatric Intussusceptions: Unequivocal Differentiation of Ileocolic, Obstructive and Transient Small-Bowel Intussusceptions. Ultrasound Med Biol. 2020;46(3):589-597. doi:10.1016/j.ultrasmedbio.2019.12.011. PMID: 31924421.
- Lioubashevsky N, Hiller N, Rozovsky K, Segev L, Simanovsky N. Ileocolic versus small-bowel intussusception in children: can US enable reliable differentiation? Radiology. 2013;269(1):266-271. doi:10.1148/radiol.13122639. PMID: 23801771.
- Zhang M, Zhou X, Hu Q, Jin L. Accurately distinguishing pediatric ileocolic intussusception from small-bowel intussusception using ultrasonography. J Pediatr Surg. 2021;56(4):721-726. doi:10.1016/j.jpedsurg.2020.06.014. PMID: 32682542.
- Wang Q, Luo M, Xie X, Wu Y, Xiang B. Can intussusceptions of small bowel and colon be transient? A prospective study. Eur J Pediatr. 2019;178(10):1537-1544. doi:10.1007/s00431-019-03455-z. PMID: 31446463.
- Subramaniam S, Chen AE, Khwaja A, Rempell R. Point-of-care ultrasound for differentiating ileocolic from small bowel-small bowel intussusception. J Emerg Med. 2022;62(1):72-82. doi:10.1016/j.jemermed.2021.07.002. PMID: 34521545.
- Zymerman SA, Cramer N, Klein A, Cohen S, Nadir E, Katzir Y. Point-of-care ultrasound-guided hydrostatic reduction of ileocolic intussusception in the pediatric emergency department. Ann Emerg Med. Published online July 2, 2026. doi:10.1016/j.annemergmed.2026.06.006. PMID: 42390396.
- Atia N, Koppel JH, Brutman-Barazani T, Soudack M, Feldman O. Bedside Intussusception Diagnosis and Reduction: A Comprehensive Emergency Department Process for Bedside Intussusception Diagnosis and Reduction. J Am Coll Emerg Physicians Open. 2026;7(3):100360. doi:10.1016/j.acepjo.2026.100360. PMID: 42267092.
Case Resolution
You place a linear, high-frequency probe on the right side of the patient’s abdomen. You perform a bedside ultrasound scan, viewing transversely and longitudinally through the upper and lower abdomen. You observe the following:
What is the diagnosis?
This is an intussusception!

The intussusceptum (red) is the part of the bowel that has telescoped into the intussuscipiens (blue). When ileum becomes trapped in the colon, this can lead to ischemia and necrosis over time. This is what causes the classic “currant jelly stools”, which are bloody stools.
Tip: The classic triad of colicky abdominal pain, palpable mass and bloody stool are present in less than 50% of patients, and intussusception should be suspected for patients with vomiting, abdominal pain, and/or lethargy.1
Hospital course
Johnny underwent an air enema reduction in the Radiology department, which successfully reduced the ileocolic intussusception.
Reference
- Daneman A, Alton D. Intussusception. Issues and controversies related to diagnosis and reduction. Radiol Clin North Am. 1996;34(4):743-756. PMID 8677307.
The PEM POCUS series was created by the UCSF Division of Pediatric Emergency Medicine to help advance pediatric care by the thoughtful use of bedside ultrasonography.
Learn more about bedside ultrasonography on the ALiEM Ultrasound for the Win series

Assistant Clinical Professor of Emergency Medicine and Pediatrics
University of California, San Francisco
Benioff Children's Hospital San Francisco
Latest posts by Margaret Lin-Martore, MD (see all)
- PEM POCUS Series: Pediatric First-Trimester Pregnancy - May 22, 2026
- PEM POCUS Series: Pediatric Appendicitis - May 31, 2022
- PEM POCUS Series: Pediatric Peripheral IV Access - May 24, 2021

Nicole Jacobs, MD
Department of Pediatrics
University of California San Francisco
Latest posts by Nicole Jacobs, MD (see all)
- PEM POCUS Series: Hip Effusion - May 17, 2021
- PEM POCUS Series: Intussusception - May 10, 2021