About Nicole Jacobs, MD

Resident Physician
Department of Pediatrics
University of California San Francisco

PEM POCUS Series: Hip Effusion

Read this tutorial on the use of point of care ultrasonography (POCUS) for pediatric hip effusion. Then test your skills on the ALiEMU course page to receive your PEM POCUS badge worth 2 hours of ALiEMU course credit.


PATIENT CASE: Child with a Limp

Sarah is a 4-year-old girl who comes into the emergency department complaining of a limp for the last day. She had an upper respiratory infection which started a week ago for which she had been taking acetaminophen and ibuprofen with her last dose of either being 2 days ago. Those symptoms have improved. Yesterday, she started complaining of diffuse right leg pain primarily at her hip, thigh, and knee. Today, her parents noted she was walking with a limp.

On arrival, her vital signs are:

Vital SignFinding
Temperature100.1F
Heart rate100 bpm
Blood pressure97/50
Respiratory rate19
Oxygen saturation (room air)100%

She is well appearing and walks with an antalgic gait favoring the left leg. She has a normal HEENT, neck, cardiac, respiratory, abdominal, and back examination. She points to her right anterior thigh when you ask her where her pain is. She has limited range of motion with internal and external rotation of her right hip and complains of pain. She cries when you palpate any part of her leg, but is able to range her knee, ankle, and foot fully. She has 2+ dorsalis pedis and posterior tibialis pulses and intact sensation to light touch throughout. 

Given her pain with range of motion at her hip, you order a hip radiograph, but while waiting for it, decide to perform a hip point of care ultrasound (POCUS) examination.

PEDIATRIC HIP EFFUSION: Ultrasound Technique

It can be difficult for children to locate the exact area of pain and often hip pain can present with referred knee and thigh pain. A thorough physical examination along with hip POCUS can help localize the area of discomfort. When we use POCUS to evaluate the hip, we are primarily looking for a joint effusion in the synovial space. This is best visualized anterior to the femoral neck.  

hip anatomy hip effusion
Figure 2. Hip anatomy with target landmark being the femoral neck (red arrow) 

Technique

  1. The patient should be positioned supine.
    • Depending on the age of the child, the child can be positioned supine in the guardian’s lap while undergoing the examination. 
    • Offering the child a toy, book, or phone/tablet for distraction during the examination can also help ease anxiety.
  2. Use a linear high frequency transducer with a wide footprint.
  3. Place the transducer along the anterior hip.
    • Use the greater trochanter as a lateral landmark and place the probe on top of the femoral head and neck (Figure 3)
  4. Aim the probe marker towards the patient’s umbilicus.
hip effusion ultrasound
Figure 3. Linear transducer at the hip with probe marker (red dot) aimed towards the patient’s umbilicus
  1. Identify the anatomical landmarks on ultrasound (figure 4) 
    • Hip muscles: Sartorius, quadriceps, and iliopsoas
    • Bones: Femoral head, femoral neck
  2. The area of interest in looking for a hip effusion is the synovial space anterior to the femoral neck and NOT anterior to the femoral head. This area is also referred to as the anterior synovial recess.
Figure 4. Ultrasound image showing the normal landmarks for a pediatric hip without an effusion and the location of the femoral head (X) and synovial space (circle) with the linear transducer positioned overlying and longitudinal to the femoral neck
  • Tips:
    • It is often helpful to ultrasound the unaffected side as a comparison.
    • Be aware of the patient’s comfort throughout the examination.

ABNORMAL ULTRASOUND FINDINGS

A hip effusion will appear anechoic (black) in the synovial space anterior to the femoral neck (anterior synovial recess). Measure the distance between the anterior surface of the femoral neck and the posterior surface of the iliopsoas muscle. Examples are illustrated in figures 5 and 6.

hip effusion PEM POCUS ultrasound

There have been different methods used to assess if an effusion is present including:​1,2​

  • Measured effusion is >0.5 cm 
  • Measured effusion with >0.2 cm difference compared to the contralateral hip
  • Gestalt view with the anterior synovial recess areas appearing asymmetric compared to the other hip

Limitations of the Hip POCUS

Note that hip POCUS does not tell you the cause of an effusion but rather only whether an effusion is present or not. Effusions can result from infectious, inflammatory, and traumatic etiologies, and thus it is important to take into account the context of the patient’s presentation. 

References

  1. Vieira R, Levy J. Bedside ultrasonography to identify hip effusions in pediatric patients. Ann Emerg Med. 2010;55(3):284-289. PMID 19695738
  2. Cruz C, Vieira R, Mannix R, Monuteaux M, Levy J. Point-of-care hip ultrasound in a pediatric emergency department. Am J Emerg Med. 2018;36(7):1174-7. PMID 29223689 

FACTS and LITERATURE REVIEW

There have been multiple case reports of hip POCUS identifying hip effusions in children with fractures, septic joints, and in the work-up of children with limps [1–4]. There are limited studies examining the accuracy of hip POCUS compared to radiology-performed ultrasounds in children. The studies that exist show high sensitivity and specificity when hip POCUS is performed by pediatric emergency medicine (PEM) physicians (Table 1).

Additional studies have explored the development of hip effusion clinical decision-making tools to support POCUS in the diagnosis of transient synovitis and differentiate it from other causes of non-traumatic arthritis in patients with a hip effusion, including septic arthritis, Lyme arthritis, and osteomyelitis [5]. For example, one retrospective pilot study found that the combination of POCUS performed by PEM physicians and a clinical decision rule could correctly rule in transient synovitis in 63 of 67 patients with a hip effusion [6].

The use of POCUS in the ED has also been associated with cost savings and greater clinical efficiency. In pediatric patients, hip POCUS has demonstrated potential cost-saving benefits compared with radiology-performed ultrasound. One Australian economic evaluation estimated annual savings of approximately AU$35,800 (about US$25,000), mainly by shortening the time children spent in an ED bed waiting for an ultrasound [7]. Additionally, in a case series of 10 children with septic arthritis of the hip, POCUS-guided hip aspiration by a PEM-trained physician was associated with a shorter time to antibiotic administration [1].

Although standardized training requirements for hip effusion POCUS in pediatric patients have not been established, scanning accuracy appears to be influenced by operator experience and confidence. As illustrated in Table 1, sensitivity and specificity were higher among physicians who had performed more hip POCUS scans and among those with greater confidence in their ultrasound skills [8,9,11]. These findings highlight the importance of continued practice and experience in developing proficiency in hip POCUS, ultimately improving diagnostic accuracy and supporting timely clinical decision-making. So, make sure to keep scanning!

StudyNSensitivitySpecificityComments
Vieira et al., Ann Emerg Med, 2010 [8]2885%93%If the pediatric emergency physician had a high confidence in ultrasound accuracy, the sensitivity increased to 90% and specificity to 100%.
Cruz et al., Am J Emerg Med, 2018 [9]51685%98%For each additional hip POCUS performed, the odds of an accurate scan increased by 2.4%.
Katz-Dana et al., CJEM, 2024 [10]9589.8%91.3%Strong positive LR of 10.33 and negative LR of 0.11 for PEM physician-performed POCUS.
Jones et al., Ann Emerg Med, 2025 [11]161 (322 hips)89.3%99.2%For the 3 high-volume pediatric emergency physicians, sensitivity and specificity increased to 98.1% and 97.8%, respectively. Sensitivity and specificity are per hip.
Table 1. Published studies comparing pediatric hip POCUS to radiology-performed ultrasound


References [click to expand] +

  1. Berant R, Bder M, Kaufman-Shriqui V, Shahar-Nissan K. Point-of-Care Ultrasound-Guided Aspiration of the Hip Joint by an Emergency Medicine Physician: A Pediatric Retrospective Case Series. Pediatr Emerg Care. 2022;38(3):139-142. doi:10.1097/PEC.0000000000002650. PMID: 35226624.
  2. Deanehan J, Gallagher R, Vieira R, Levy J. Bedside hip ultrasonography in the pediatric emergency department: a tool to guide management in patients presenting with limp. Pediatr Emerg Care. 2014;30(4):285-287. doi:10.1097/PEC.0000000000000113. PMID: 24694889.
  3. Garrison J, Nguyen M, Marin J. Emergency Department Point-of-Care Hip Ultrasound and Its Role in the Diagnosis of Septic Hip Arthritis: A Case Report. Pediatr Emerg Care. 2016;32(8):555-557. doi:10.1097/PEC.0000000000000874. PMID: 27490732.
  4. Tsung J, Blaivas M. Emergency department diagnosis of pediatric hip effusion and guided arthrocentesis using point-of-care ultrasound. J Emerg Med. 2008;35(4):393-399. doi:10.1016/j.jemermed.2007.10.054. PMID: 18403170.
  5. Chan N, McCreary DJ, Nedyalkova A, Snelling PJ. Point-of-care ultrasound for the diagnosis of hip effusion in children presenting to the emergency department with atraumatic limp or hip pain: a scoping review. J Ultrasound Med. 2026;45(10):2109-2118. doi:10.1002/jum.70286. PMID: 42104527.
  6. McCreary DJ, Chowdhury R, Hamilton C. Can a POCUS Clinical Decision Rule Improve Reliability in the Diagnosis of Paediatric Transient Synovitis of the Hip? A Single Centre Pilot Study. POCUS J. 2025;10(2):103-108. doi:10.24908/pocusj.v10i02.18290. PMID: 41322175.
  7. Bailey C, Deane H, O’Brien A, Dalziel K. An economic evaluation of point-of-care ultrasound for children presenting to the emergency department with suspected septic arthritis of the hip. Aust Health Rev. 2024;48(1):37-44. doi:10.1071/AH23214. PMID: 38266497.
  8. Vieira R, Levy J. Bedside ultrasonography to identify hip effusions in pediatric patients. Ann Emerg Med. 2010;55(3):284-289. doi:10.1016/j.annemergmed.2009.06.527. PMID: 19695738.
  9. Cruz C, Vieira R, Mannix R, Monuteaux M, Levy J. Point-of-care hip ultrasound in a pediatric emergency department. Am J Emerg Med. 2018;36(7):1174-1177. doi:10.1016/j.ajem.2017.11.059. PMID: 29223689.
  10. Katz-Dana H, Stackievicz R, Dana E, et al. Diagnostic accuracy of point-of-care ultrasound (PoCUS) for the diagnosis of hip effusion in the pediatric emergency department. CJEM. 2024;26(12):875-882. doi:10.1007/s43678-024-00788-z. PMID: 39352610.
  11. Jones RM, Malia L, Snelling PJ, et al. Diagnostic Accuracy of Point-of-Care Ultrasound for Hip Effusion: A Multicenter Diagnostic Study. Ann Emerg Med. 2025;86(6):566-575. doi:10.1016/j.annemergmed.2025.04.033. PMID: 40481828.

CASE RESOLUTION

The patient’s hip plain film radiographs are unremarkable. You decide to incorporate hip POCUS to your evaluation. You place a linear, high-frequency transducer and visualize the patient’s bilateral hips. You observe the following:

Right Hip (Affected Side) POCUS Video and Key View

Though the child complained of hip, knee, and thigh pain, your POCUS evaluation identifies a right hip effusion which helps you narrow the location of her pain.

Video 1. A hip POCUS of the case patient’s right hip (affected side)


PEM POCUS hip effusion
Figure 7. Right (affected side) hip POCUS with a hip effusion measuring 0.77 cm

Left Hip (Normal Side) POCUS Video and Key View

Video 2. A hip POCUS of the case patient’s left hip (unaffected side) for comparison


PEM POCUS hip no effusion normal
Figure 8. Left (unaffected side) hip POCUS with no effusion

ED Course

The patient’s labs result, and she has reassuring labs, which include a serum WBC 8.3 x109/L and ESR 34 mm/hr. The patient receives ibuprofen during her visit and within 1 hour is able to walk without a significant limp and states she feels better. The patient’s family notes they have spent the last few weeks of summer in a Lyme-endemic region, and so you send off Lyme titers.

Given the resolution of limp, lack of fever, and reassuring lab values, you do not believe the patient has a septic joint. Her effusion is more likely the result of a transient synovitis. You recommend close pediatrician follow-up.

Pediatrician Clinic Follow-Up

At her pediatrician clinic visit 1 week later, her Lyme titers return negative, and the patient continues to be limp-free.  


The PEM POCUS series was created by the UCSF Division of Pediatric Emergency Medicine to help advance pediatric care by the thoughtful use of bedside ultrasonography.

Read other PEM POCUS tutorials. Learn more about bedside ultrasonography on the ALiEM Ultrasound for the Win series.

By |2026-10-15T12:39:29-07:00May 17, 2021|Orthopedic, PEM POCUS, Ultrasound|

PEM POCUS Series: Intussusception

PEM POCUS Intussusception badge

Read this tutorial on the use of point of care ultrasonography (POCUS) for pediatric intussusception. Then test your skills on the ALiEMU course page to receive your PEM POCUS badge worth 2 hours of ALiEMU course credit.

PATIENT CASE

Johnny is a 2-year-old boy who comes into the emergency department for abdominal pain for the last day. His parents are concerned that he has been having intermittent abdominal pain and has seemed very tired all day. Parents deny bloody stool.

On arrival, his vital signs are:

Vital Sign Finding
Temperature 36.9C
Heart rate 110 bpm
Blood pressure 97/50
Respiratory rate 22
Oxygen saturation (room air) 99%

He is tired appearing, and his abdominal exam is soft but diffusely tender. Given his intermittent abdominal pain, you decide to perform an intussusception point of care ultrasound (POCUS) exam.

ULTRASOUND TECHNIQUE

Intussusception is when one part of the bowel telescopes, or gets stuck, in another part of the bowel. Typically intussusception refers to ileocolic intussusception where the ileum becomes stuck in the colon. To perform the ultrasound, start in the right lower quadrant and trace the colon. See below for a step-by-step technique.

intussusception
Overview of sequential ultrasound transducer positioning on the anterior abdomen to assess for intussusception

Technique

  • The patient should be positioned supine.
  • To aid in comforting the child, the child can be positioned supine in the parent’s lap while undergoing the scan. Having the parent or another provider offer a toy, book, or phone/tablet to distract the child during the scan can also help ease anxiety.
  • Begin in the right lower quadrant (RLQ), using a high frequency linear probe with the probe marker to patient’s right.
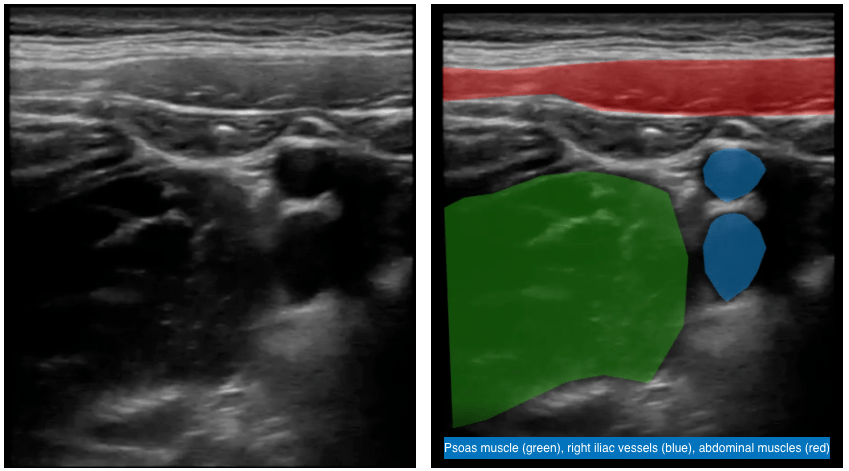
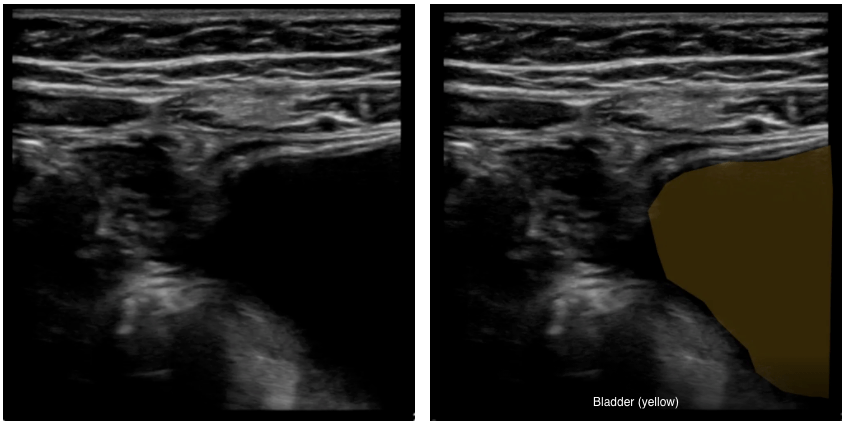
  • First, identify the anatomical landmarks in the RLQ (see ultrasound images below):
    • Psoas muscle (green) laterally
    • Right iliac vessels (blue)
    • Abdominal muscles (red)
    • Bladder (yellow) medially

Ultrasound image: Anterior Abdomen (RLQ) View

intussusception RLQ ultrasound

Ultrasound Image: Anterior Abdomen RLQ (More Medial) View

PEM POCUS intussusception RLQ More Medial
  • Perform graded compression, with slow steady pressure to displace bowel gas
  • Follow the colon from the RLQ to right upper quadrant (RUQ) until the liver (purple) and gallbladder are identified

Ultrasound Image: Anterior Abdomen (RUQ) View

PEM POCUS intussusception RUQ
  • Rotate the probe marker to patient’s head and scan the entire length of the transverse colon.
  • Rotate the probe marker back to patient’s right and scan the entire length of the descending colon, making sure to scan all four quadrants.
  • Save representative video clips and still images of each quadrant.
  • If an intussusception is found, measure its diameter in transverse view and note in which quadrant(s) it is found.
  • At the end of scan, if you have found an intussusception, re-image the abdomen to make sure it was not transient.
  • The provider should maintain awareness of the patient’s comfort throughout the scan.

INTUSSUSCEPTION CLASSIC FINDINGS

Normal (no intussusception)

Normal: There is no target or sandwich sign, but rather just folded normal bowel. (To replay, press circular arrow in bottom left corner)

Abnormal findings

  • Look for findings of a sandwich sign (or pseudo-kidney sign) in the longitudinal view and target sign (or donut sign) in the transverse view.
  • If visualized, measure the diameter of the intussusception in short axis (transverse) and note which in which quadrant(s) it is located.

Sandwich

Anterior abdomen ultrasound: Intussusception – Presence of a sandwich sign (long axis view) and target sign (short axis view)

Target Sign

Intussusception diameter ultrasound
Measurement: The diameter of an intussusception (i.e., target sign) in transverse view involves measuring the distance from outer wall to outer wall.

Additional Anterior Abdominal Ultrasound Videos

Pro Tip
It can be difficult to distinguish intussusception of the small bowel-small bowel (i.e., when the ileum or part of the small bowel telescopes into itself) versus ileocolic (i.e., when the ileum becomes telescopes into the colon). The former often does not require a procedure for reduction, while the latter typically does. If the target sign diameter is <2 cm and transient, a small bowel-small bowel intussusception should be suspected. The length of the intussusception, or how many quadrants are involved, can also be measured for an idea of how much bowel is involved.

Small bowel-small bowel intussusception

Small bowel-small bowel intussusception – Note the small size of the target lesion. Because the ultrasound video scans to a depth of 3.3 cm (see bottom right side of the screen), the target sign appears to be approximately only 1 cm in diameter.


Small bowel-small bowel intussusception – There is a target sign, but it is small (<2 cm) with a small fat (white) core.


Ileo-colic intussusception

Ileo-colic intussusception with classic target sign – Note the lymph nodes (black) inside the mesenteric fat (white) in the center of the target.

FACTS and LITERATURE REVIEW

Mimickers of Intussusception

There are additional pathologies that can be mistaken for intussusception such as an intussuscepted appendix, appendicitis surrounded by abscess, and Meckel’s diverticulum, which are beyond the scope of this course. Any concerning finding for intussusception should be followed by a confirmatory study by the radiology department.

Benefits of intussusception POCUS scans

There have been several studies examining point-of-care ultrasonography (POCUS) for intussusception, which have shown excellent test characteristics and a decreased length of stay when using POCUS. POCUS also has no radiation exposure and may further help reduce morbidity by reducing delays in diagnosis of intussusception [1].

POCUS performed by PEM physicians has demonstrated a high level of accuracy in diagnostic agreement with radiologist-performed ultrasounds. For example, in a study by Arroyo et al., POCUS agreement with radiologist-performed ultrasounds occurred in 97 of 100 cases [1]. There is also research comparing positive ultrasound diagnosis (including POCUS and radiologist-performed ultrasound) of intussusception to confirmatory surgical or contrast enema, as exhibited by the table below.

Below is a table of test characteristics of POCUS for intussusception.

Publication Methodology Sensitivity Specificity
Riera et al. (2012) [2] Prospective study of 82 patients who underwent POCUS by pediatric emergency medicine (PEM) providers. The gold standard was a comprehensive radiology ultrasound. 85% 97%
Trigylidas et al. (2019) [3] Retrospective study of 102 POCUS exams in 101 patients by PEM providers. The gold standard was pediatric radiologist confirmation by review of the POCUS images, a radiology department ultrasound, or an air enema. 96.0% 92.6%
Lee et al. (2020) [4] This retrospective study included 575 scans from 549 patients aged 1 month to 6 years with clinically suspected ileocolic intussusception, who underwent POCUS performed by PEM physicians of a tertiary hospital. The gold standard for comparison was radiologist-performed ultrasound. 100% 95.6%
Bergmann et al. (2021) [5] This prospective study of 256 children across 17 sites (35 PEM physicians with experience/extra training in POCUS) compared POCUS and radiologist-performed ultrasound using a gold standard of clinically important intussusception which was defined as an intussusception that required radiographic or surgical reduction during or within 7 days of the incident ED visit. 96.6% 98%
Tonson la Tour et al. (2021) [6] This prospective study included 131 children evaluated by POCUS, of whom 45 (34%) had an intussusception. Twenty-four PEM physicians with various levels of training performed POCUS and were able to identify 39 of 45 intussusception cases. PEM-performed POCUS was then compared to the gold standard, radiologist-performed ultrasound. Interestingly, diagnostic accuracy did not differ significantly between novice and experienced sonographers. 87% 97%
Lin-Martore et al. (2022) [7] This systematic review and meta-analysis of diagnostic accuracy of POCUS for intussusception included 2400 patients and 11 studies. The POCUS evaluation of the lesion was performed by an adult or pediatric emergency physician. Each study consisted of a gold standard test including radiologist-performed ultrasonography, other radiology diagnostic imaging, air enema, or patient follow-up. 95.1% 98.1%
Rahmani et al. (2023) [8] This meta-analysis included 37 studies to calculate the pooled sensitivity and specificity of ultrasound diagnosis of intussusception. The studies included used POCUS results from EM physicians and residents, sonography technicians, and one used a PEM physician certified in pediatric gastroenterology. It also included radiology-performed ultrasound. Each study consisted of comparison to a gold standard including radiologist-performed ultrasound, clinical follow-up, surgical report, and air or barium enema. 96% 97%
Alsabri et al. (2026) [9] This meta-analysis includes a total of 44 studies (prospective and retrospective cohort studies, cross-sectional studies, and case-control studies) for pooled sensitivity and specificity of ultrasound for diagnosing intussusception. It includes POCUS from PEM physicians and radiology ultrasounds. The gold standard of confirmation included surgical findings, clinical follow-up, and contrast enema (barium and air). 96.3% 95.7%
Table 1. Test characteristics of ultrasound for intussusception

In terms of Emergency Department (ED) length of stay (LOS), Kim et al. (2020) reported that after the introduction of an intussusception POCUS scanning protocol for PEM physicians to implement in the ED, the LOS decreased by more than 200 minutes [10]. An additional study has shown that a POCUS-first pathway can be a way to expedite care for children with suspected intussusception in the ED, leading to reduced physician initial assessment to reduction time by an average of 69.9 min when compared to traditionally waiting for radiologist-performed ultrasound evaluation [11].

Differentiating small bowel-small bowel from ileocolic intussusception

In general, true ileocolic intussusceptions are:

  • Found on the right side of the abdomen
  • >2 cm in diameter
  • Have mesenteric fat (which is white) and lymph nodes in the center
  • Do not self-resolve

There have been studies looking at distinguishing small bowel-small bowel intussusception (SB-SBI) from ileocolic intussusception (ICI). Most of these, however, have been radiology-based rather than POCUS studies, making generalizability to the ED setting challenging. Thus, if there is a concern for an intussusception, a radiology ultrasound should be ordered.

In a small study of 27 patients, Wiersma et al. (2006) [12] found that SB-SBI had smaller mean diameters and shorter lengths than ICI. Consistent with these findings, a more recent study reported similar findings, with all ICI cases in the study having lesion diameters greater than 2 cm [13]. This study also suggested a difference in age distribution between the two intussusception lesions studied: patients with SB-SBI tended to be older and exhibited a wider age range, whereas the ICI group consisted predominantly of infants younger than 1 year [13].

Study author and year N (patients) Age (mean or median) Mean diameter Mean length Notes
Wiersma et al. (2006) [12] SB-SBI: 10
ICI: 14
SB-SBI: 3.1 yr (mean)
ICI: 1.9 yr (mean)
SB-SBI: 1.5 cm
ICI: 3.7 cm
SB-SBI: 2.5 cm
ICI: 8.2 cm
SB-SBI: Lesions were located throughout the abdomen (6 paraumbilical, 2 RUQ, 2 RLQ, 1 LLQ).
All ICI lesions were located on the right side of the abdomen.
Park et al. (2019) [13] SB-SBI: 21
ICI: 16
SB-SBI: 54 mo (median)
ICI: 8 mo (median)
SB-SBI: 1.68 cm
ICI: 2.74 cm
Not reported SB-SBI was identified more frequently than ICI in this cohort when using POCUS screening tool, which may be due to rapid detection by POCUS and/or lower threshold for evaluating for intussusception.
Goel et al. (2020) [14] SB-SBI: 21
ICI: 33
SB-SBI: 17.3 mo
ICI: 22.2 mo
SB-SBI: 2.13 cm
ICI: 3.24 cm
SB-SBI: 3.17 cm for obstructive cases and 1.93 cm for transient cases
ICI: Not reported
The team noted an optimal threshold of 2.5 cm to distinguish between transient and obstructive SB-SBIs. Lymph nodes were present in 18 (33.3%) out of 54 surgically confirmed cases, and all were ICI.
Table 2. Studies comparing SB-SBI versus ICI

Lioubashevsky et al. (2013) [15] evaluated a larger cohort of 174 patients and reported similar findings. In addition to assessing the inner fat core-to-outer wall thickness ratio, the authors examined the presence or absence of lymph nodes within the intussusception. These findings were supported by Zhang et al. (2021) [16], who identified lymph nodes in only one case of SB-SBI, compared with 56 cases (93%) of ICI. Zhang et al. also found that the fat core was visible on ultrasound in all cases of ICI but was absent in 16% of SB-SBI cases [16]. Similarly, Goel et al. reported an inner fat core-to-outer wall thickness ratio > 1 in all cases of ICI and < 1 in all cases of SB-SBI, further supporting the diagnostic utility of this sonographic feature [14].

These differences may be explained by the underlying anatomical and physiological characteristics of the involved bowel segments [14,15]. The mesentery associated with the ileocolic region contains greater amounts of adipose tissue and lymph nodes than the mesentery involved in SB-SBI [14-16]. This could explain why ileocolic intussusceptions tend to demonstrate greater lymph node and fat involvement, appearing as hyperechoic structures on ultrasound [15-17]. The increased proportion of mesenteric fat and lymphatic tissue may also contribute to the larger diameter of ICI lesions [14,16,17]. In contrast, the shorter length of SB-SBI lesions reported in previous studies may be attributable to active bowel peristalsis and the greater likelihood of spontaneous resolution in these cases [16,17].

Subramaniam et al. (2022) [18] looked at POCUS differentiating SB-SBI from ICI. Similar to above, they noted the predominant location of SB-SBI in the periumbilical or left abdomen compared with the right-sided predominance of ICI; the larger diameter of ICI, typically greater than 2.5 cm; the greater length of ICI, typically exceeding 3 cm; the presence of lymph nodes within ICI; the presence of peristalsis within SB-SBI; and the larger core-to-wall index associated with ICI [18].

While beyond the scope of this module, there is some evidence that POCUS may facilitate the treatment of intussusception in addition to its diagnostic utility. Zymerman et al. (2026) [19] reported a case series of 9 reductions with an 88.9% success rate for POCUS-guided hydrostatic reduction of ICI performed at the bedside by a pediatric emergency medicine physician. Similarly, Atia et al. (2026) [20] reported a retrospective chart review with 24 of 28 ICI (86%) successfully reduced when ICI was diagnosed using POCUS and bedside ultrasound-guided hydrostatic reduction was performed by a pediatric radiologist. This study also reported a mean time from admission to reduction of 126 minutes and a mean hospital length of stay of 407 minutes [20]. Together, these findings suggest that POCUS may serve not only as a reliable diagnostic tool for differentiating ICI from SB-SBI but also as a means of facilitating timely and effective bedside therapeutic intervention.

References [click to expand] +

  1. Arroyo AC, Zerzan J, Vazquez H et al. Diagnostic accuracy of point-of-care ultrasound for intussusception performed by pediatric emergency medicine physicians. J Emerg Med. 2021;60(5):626-632. doi:10.1016/j.jemermed.2020.11.030. PMID: 33483198.
  2. Riera A, Hsiao A, Langhan M, Goodman T, Chen L. Diagnosis of intussusception by physician novice sonographers in the emergency department. Ann Emerg Med. 2012;60(3):264-268. doi:10.1016/j.annemergmed.2012.02.007. PMID: 22424652.
  3. Trigylidas TE, Hegenbarth MA, Patel L, Kennedy C, O’Rourke K, Kelly JC. Pediatric emergency medicine point-of-care ultrasound for the diagnosis of intussusception. J Emerg Med. 2019;57(3):367-374. doi:10.1016/j.jemermed.2019.06.007. PMID: 31405782.
  4. Lee JY, Kim JH, Choi SJ, Lee JS, Ryu JM. Point-of-care ultrasound may be useful for detecting pediatric intussusception at an early stage. BMC Pediatr. 2020;20(1):155. doi:10.1186/s12887-020-02060-6. PMID: 32284038.
  5. Bergmann KR, Arroyo AC, Tessaro MO et al; P2Network. Diagnostic Accuracy of Point-of-Care Ultrasound for Intussusception: A Multicenter, Noninferiority Study of Paired Diagnostic Tests. Ann Emerg Med. 2021;78(5):606-615. doi:10.1016/j.annemergmed.2021.04.033. PMID: 34226072.
  6. Tonson la Tour A, Desjardins MP, Gravel J. Evaluation of bedside sonography performed by emergency physicians to detect intussusception in children in the emergency department. Acad Emerg Med. 2021;28(8):866-872. doi:10.1111/acem.14226. PMID: 33548161.
  7. Lin-Martore M, Firnberg MT, Kohn MA, Kornblith AE, Gottlieb M. Diagnostic accuracy of point-of-care ultrasonography for intussusception in children: A systematic review and meta-analysis. Am J Emerg Med. 2022;58:255-264. doi:10.1016/j.ajem.2022.06.025. PMID: 35749802.
  8. Rahmani E, Amani-Beni R, Hekmatnia Y et al. Diagnostic Accuracy of Ultrasonography for Detection of Intussusception in Children; a Systematic Review and Meta-Analysis. Arch Acad Emerg Med. 2023;11(1):e24. doi:10.22037/aaem.v11i1.1914. PMID: 36919137.
  9. Alsabri M, Rath S, Elkarargy MA et al. Accuracy of ultrasound for intussusception in pediatric emergency presentations: a systematic review and diagnostic meta-analysis. Int J Emerg Med. 2026;19(1):41. doi:10.1186/s12245-026-01134-z. PMID: 41667954.
  10. Kim JH, Lee JY, Kwon JH, Cho HR, Lee JS, Ryu JM. Point-of-Care Ultrasound Could Streamline the Emergency Department Workflow of Clinically Nonspecific Intussusception. Pediatr Emerg Care. 2020;36(2):e90-e95. doi:10.1097/PEC.0000000000001283. PMID: 28926507.
  11. Katz-Dana H, Harel-Sterling M, Vincent D, Dana E, Navarro OM, McLean LJ. A POCUS-first pathway to streamline care for children with suspected ileocolic intussusception. CJEM. 2024;26(4):235-243. doi:10.1007/s43678-024-00673-9. PMID: 38538954.
  12. Wiersma F, Allema JH, Holscher HC. Ileoileal intussusception in children: ultrasonographic differentiation from ileocolic intussusception. Pediatr Radiol. 2006;36(11):1177-1181. doi:10.1007/s00247-006-0311-2. PMID: 17019589.
  13. Park BL, Rabiner JE, Tsung JW. Point-of-care ultrasound diagnosis of small bowel-small bowel vs ileocolic intussusception. Am J Emerg Med. 2019;37(9):1746-1750. doi:10.1016/j.ajem.2019.06.024. PMID: 31257125.
  14. Goel I, Anand R, Choudhury SR, Agarwal S. Evolving Concepts in Ultrasonography of Pediatric Intussusceptions: Unequivocal Differentiation of Ileocolic, Obstructive and Transient Small-Bowel Intussusceptions. Ultrasound Med Biol. 2020;46(3):589-597. doi:10.1016/j.ultrasmedbio.2019.12.011. PMID: 31924421.
  15. Lioubashevsky N, Hiller N, Rozovsky K, Segev L, Simanovsky N. Ileocolic versus small-bowel intussusception in children: can US enable reliable differentiation? Radiology. 2013;269(1):266-271. doi:10.1148/radiol.13122639. PMID: 23801771.
  16. Zhang M, Zhou X, Hu Q, Jin L. Accurately distinguishing pediatric ileocolic intussusception from small-bowel intussusception using ultrasonography. J Pediatr Surg. 2021;56(4):721-726. doi:10.1016/j.jpedsurg.2020.06.014. PMID: 32682542.
  17. Wang Q, Luo M, Xie X, Wu Y, Xiang B. Can intussusceptions of small bowel and colon be transient? A prospective study. Eur J Pediatr. 2019;178(10):1537-1544. doi:10.1007/s00431-019-03455-z. PMID: 31446463.
  18. Subramaniam S, Chen AE, Khwaja A, Rempell R. Point-of-care ultrasound for differentiating ileocolic from small bowel-small bowel intussusception. J Emerg Med. 2022;62(1):72-82. doi:10.1016/j.jemermed.2021.07.002. PMID: 34521545.
  19. Zymerman SA, Cramer N, Klein A, Cohen S, Nadir E, Katzir Y. Point-of-care ultrasound-guided hydrostatic reduction of ileocolic intussusception in the pediatric emergency department. Ann Emerg Med. Published online July 2, 2026. doi:10.1016/j.annemergmed.2026.06.006. PMID: 42390396.
  20. Atia N, Koppel JH, Brutman-Barazani T, Soudack M, Feldman O. Bedside Intussusception Diagnosis and Reduction: A Comprehensive Emergency Department Process for Bedside Intussusception Diagnosis and Reduction. J Am Coll Emerg Physicians Open. 2026;7(3):100360. doi:10.1016/j.acepjo.2026.100360. PMID: 42267092.

Case Resolution

You place a linear, high-frequency probe on the right side of the patient’s abdomen. You perform a bedside ultrasound scan, viewing transversely and longitudinally through the upper and lower abdomen. You observe the following:

What is the diagnosis?

This is an intussusception!

The intussusceptum (red) is the part of the bowel that has telescoped into the intussuscipiens (blue). When ileum becomes trapped in the colon, this can lead to ischemia and necrosis over time. This is what causes the classic “currant jelly stools”, which are bloody stools.

Tip: The classic triad of colicky abdominal pain, palpable mass and bloody stool are present in less than 50% of patients, and intussusception should be suspected for patients with vomiting, abdominal pain, and/or lethargy.​1​

Hospital course

Johnny underwent an air enema reduction in the Radiology department, which successfully reduced the ileocolic intussusception.

Reference

  1. Daneman A, Alton D. Intussusception. Issues and controversies related to diagnosis and reduction. Radiol Clin North Am. 1996;34(4):743-756. PMID 8677307.

The PEM POCUS series was created by the UCSF Division of Pediatric Emergency Medicine to help advance pediatric care by the thoughtful use of bedside ultrasonography.

Learn more about bedside ultrasonography on the ALiEM Ultrasound for the Win series

By |2026-10-27T10:08:37-07:00May 10, 2021|Gastrointestinal, PEM POCUS, Ultrasound|
Go to Top