Trick of the Trade: Mark your sites with a Sharpie
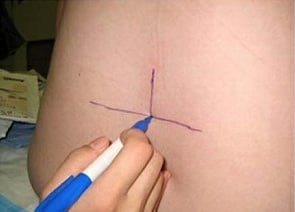
Marking the surface anatomy for procedures can significantly increase your chances for success, such as for lumbar punctures and central lines. I can never seem to find surgical skin markers.



Marking the surface anatomy for procedures can significantly increase your chances for success, such as for lumbar punctures and central lines. I can never seem to find surgical skin markers.
Sometimes classic techniques need to be revisited, especially when I get new photos from the collective readership. Let’s review a painless way to remove beads from the ear canal. You can’t exactly have the patient’s provider blow in the other ear to expulse the bead, similar to a nasal foreign body…

Three weeks ago, I talked about more safely reducing mandibular dislocations. After successful completion of the procedure, how do you make sure that the patient doesn’t re-dislocate the mandible? You definitely should tell the patient to keep their jaw closed as much as possible for the next 24 hours and avoid opening the mouth widely (eg. yawning/laughing).
How do you immobilize the mandible? Especially for the chronic dislocators, presumably with more lax TMJ ligaments, you should think about immobilization. This can be done with a head bandage which goes under the chin. You can use kerlix rolls or an ACE wrap.

You identify a great external jugular (EJ) vein to cannulate for IV access. You are having a hard time keeping the angle of the angiocatheter aimed at a shallow angle because the mandible is in the way. This is typical of patients with chubby necks (eg. pediatric patients) or who are unable to rotate their neck.
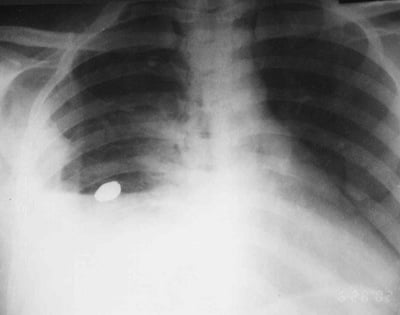 A 40 year-old man presents with a traumatic hemopneumothorax. He weighs 400 pounds.
Chest tubes can sometimes be challenge, especially for those with extra redundant tissue to tunnel through before reaching the intrathoracic cavity. You want to avoid placing the chest tube mistakenly in the subcutaneous space. How can you ensure that your chest tube actually reaches the intrathoracic space?
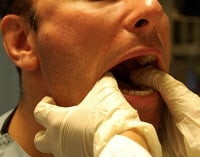
Does anyone think that this is generally a bad idea when closed-reducing mandible dislocations? Yes, it’s easiest to apply downward pressure on the mandible by pushing down on the occlusal surfaces of the molar teeth. Sometimes, however, when the mandible relocates into place, the teeth clamp shut abruptly – placing your thumbs at risk. How can you prevent any injuries to yourself?
One way is to slide gauze into the mouth during your procedure. Start the video around the 1:30 mark for an exam.
Apply a protective roll of gauze over each thumb. Additionally, you can wear a second glove to cover the gauze. No, those are NOT just fat thumbs under the gloves.

 Thanks to Dr. Liz Brown (UCSF-SFGH EM resident) for the trick!
 A few weeks ago, I gave a Tricks of the Trade talk for the Stanford-Kaiser Emergency Medicine residents and faculty. I was overwhelmed by the great, creative ideas that came up during our discussion. An always popular topic is the drainage of peritonsillar abscesses. Sometimes it can be difficult to aspirate from a syringe using only one hand, especially with the awkward angle that you might encounter.