Patwari Academy videos: Pediatric head injury – To CT or not?
When would you obtain a CT for a pediatric patient who sustained a head injury? Watch this nice 11-minute video review by Dr. Raul Patwari, discussing the 2009 Lancet PECARN study.



When would you obtain a CT for a pediatric patient who sustained a head injury? Watch this nice 11-minute video review by Dr. Raul Patwari, discussing the 2009 Lancet PECARN study.
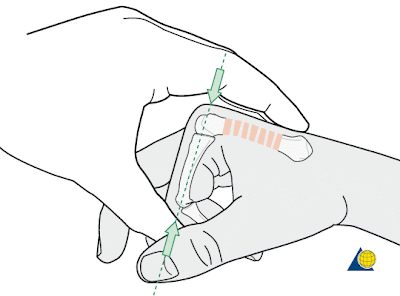
General principles of fracture reduction involve axially distracting or pulling on a fracture fragment and pushing the piece back into anatomical alignment. This can be seen in the video below (automatically starts at 2:25 for the actual procedure). What if this approach doesn’t work? The fracture fragment remains immobile despite your best efforts.
 Patients with rotation deformities of the fingers from a metacarpal fracture should be reduced. All fingers should normally point towards the patient’s scaphoid bone.
Metacarpal (MC) fractures are common injuries, which often spark discussions about whether they should be reduced in the ED urgently.
Here’s a quick-reference card to help guide your management decisions. These recommendations may vary slightly based on what references you use. You may need to tailor your decisions based on your regional practices.
Go to ALiEM (PV) Cards for more resources.
Thanks to Dr. Nicole Strauss at the UCSF-SFGH Orthopaedic Trauma Institute and my go-to hand expert for her input.
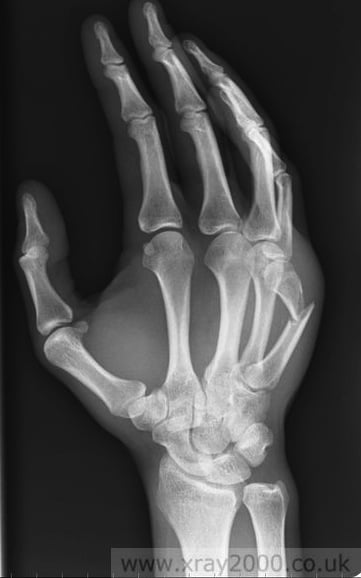
I am in the process of creating a PV card on metacarpal fractures, divided into anatomical areas (base, shaft, neck, head), and am realizing that the EM and orthopedic literature don’t quite agree. Actually they are quite vague on whether reductions should occur in the ED vs orthopedics clinic in the next few days.
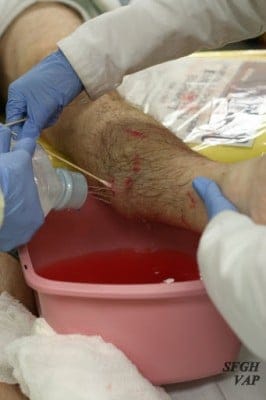
Open fractures come in all shapes and sizes. Sometimes fractures create only a small, innocuous-looking puncture through the skin. Other times they look grossly contaminated with organic material and have significant soft tissue injury. The major concern is wound infection. Prophylactic antibiotics are essential in the ED.
Typically antibiotics are first-generation cephalosporins. When do you start adding more coverage with high-dose penicillin or aminoglycosides?
Once you have significant soft tissue injury, you are automatically have a Type III fracture and should add an aminoglycoside.
Adapted from [1]
Go to ALiEM (PV) Cards for more resources.
 As a followup to the blog on the Captain Morgan technique for hip dislocations, I’d like to throw out another similar technique that also does NOT involve climbing up on the gurney.