PEM POCUS Series: Pediatric Peripheral IV Access

PEM POCUS peripheral IV ultrasound badge

Read this tutorial on the use of point of care ultrasonography (POCUS) for pediatric peripheral IV placement. Then test your skills on the ALiEMU course page to receive your PEM POCUS badge worth 2 hours of ALiEMU course credit.


PATIENT CASE: Child with Sickle Cell Pain

Abigail is a 10-year-old girl with known sickle cell disease, who presents with severe atraumatic pain in her hips and back. She is afebrile, but tachycardic and tachypneic with 10/10 pain. Nurses have made several attempts but have been unsuccessful in establishing a peripheral IV(PIV) for giving IV fluids and medications. They now ask you to obtain access. You decide to perform an ultrasound-guided PIV placement. 

Exam

Vital SignFinding
Temperature37.6C
Heart rate135 bpm
Blood pressure135/90
Respiratory rate23
Oxygen saturation (room air)99%
  • General: Well-developed, appears in significant distress due to pain.
  • Cardiovascular: Tachycardic with regular rhythm, good distal pulses, and capillary refill
  • Pulmonary: Tachypneic without retractions; good aeration without wheezes, rales, crackles.
  • Abdomen: Soft, normal bowel sounds
  • Neurologic: Alert and oriented x3 with GCS 15; no focal deficits on cranial and sensorimotor exam

What are some potential challenges in peripheral IV placement?

  • Dehydration: Veins may collapse as a result of dehydration, making them harder to identify and cannulate.
  • Vein mobility: Veins are more mobile than arteries. Particularly mobile veins can “roll” or move during cannulation attempts.
  • Overlying soft tissue: Large body habitus can interfere with visualization of veins.
  • Vein size: Some patients, especially infants, have small veins.
  • Repeated venipuncture: Some patients with chronic conditions, such as sickle cell disease, often require frequent venipuncture. Repeated venipuncture can cause veins to change morphologically over time, making them difficult to identify and cannulate.

How can POCUS be helpful in obtaining IV access?

  • Direct visualization and guidance: Real-time visualization of IV catheter/needle in real-time as it approaches and cannulates the vessel.
  • Surrounding anatomy: Visualization of surrounding structures (e.g., nerves, arteries, other veins) which may not be apparent on visual examination.
  • Differentiating vein from artery: Distinguishing between different types of vessels.

Ultrasound-Guided Peripheral IV Access: Normal Findings

1. Differentiating Veins from Arteries

Veins and arteries can be difficult to distinguish. Below is a table to help differentiate using ultrasonography. 

CharacteristicVeinsArteries
DiameterTypically larger than arteries (is dependent on fluid status)Relatively fixed in size, round in shape
Wall ThicknessThinThick
CompressibilityEasyMore difficult
Color Doppler FlowNon-pulsatilePulsatile
Vessel ValvesPresent (but not always visible)Absent
Table 1. Anatomical and ultrasonography differences between veins and arteries
  • Compressibility: Typically, veins are easily compressed, while arteries with their thick walls are more difficult to compress.  
Video 1: Ultrasound clip of a vein being compressed
  • Color Doppler Flow: Color Doppler can be used to differentiate pulsatile from non-pulsatile flow. Red and blue colors do NOT correlate with venous or arterial blood flow. Instead, the colors represent the direction of flow. A helpful acronym is BART – “Blue Away, Red Towards.”
Video 2: Ultrasound clip of a vein (red) with non-pulsatile flow and artery (blue) with pulsatile flow

2. Identifying Nerves

Nerves can be confused with blood vessels when looking on ultrasound. The following are ways to identify a nerve.

  • Honeycomb appearance: Classically nerves appear in cross-section with small hypoechoic (dark) areas separated by hyperechoic (bright) septae.
Video 3: Ultrasound clip of nerve (left) and artery (right). The nerve has a honeycomb appearance with several hypoechoic (dark) areas separated by hyperechoic (bright) septae whereas the artery is more uniformly hypoechoic. There is also a needle entering from the left of the screen. See below labeled still image of same anatomical structures below.
peripheral IV ultrasound nerve artery
Figure 1: Ultrasound still image with labeled nerve and artery. See Videos 3 and 4 for ultrasound videos of same structures with and without doppler flow. 
  •  No Color Doppler flow: While Color Doppler can be used to assess for pulsatile and non-pulsatile flow of arteries and nerves, respectively, nerves should not demonstrate any flow. 
Video 4: Ultrasound clip of nerve (left) and artery (right) with color Doppler. This is a clip of the same location on the same patient in Video 3 and Figure 1. The nerve (center of yellow box) shows no flow under color Doppler. In contrast, the artery (partially captured at right of yellow box) demonstrates pulsatile flow. 
  • Anisotropy: This ultrasound artifact is exhibited by nerves (as well as tendons and ligaments), whereby the nerve changes brightness depending on the angle of ultrasound beam.
Video 5: Ultrasound clip of nerve exhibiting anisotropy. The brightness of the nerve (in center, labeled in Figure 2 below) changes with the angle of the probe.

PEM POCUS peripheral IV anisotropy ultrasound
Figure 2: Still image from Video 5 above with nerve highlighted in yellow. 

Fun fact: Certain gemstones like tiger’s eye and figured woods like flamed maple exhibit chatoyance which is analogous to anisotropy, but occurs under visible light, rather than ultrasound beams like anisotropy.

gemstone anisotropy
Figure 3: Image of Tiger’s eye gemstone. These gemstones exhibit chatoyance, a characteristic of light reflection which is analogous to “anisotropy” under ultrasound. (Image: Benjamint444 [CC BY-SA])

3. Needle Artifact

Needles exhibit ultrasound artifacts which can help with identification.

  • Ring down artifact:  This resonance artifact describes when ultrasound beams encounter trapped gas and create a spotlight effect.  See additional information on Radiopaedia.org.
  • Reverberation artifact:  This artifact describes when ultrasound beams reflect back and forth between two strong parallel reflectors and the machine interprets additional objects deeper than the actual object.  See additional information on Radiopaedia.org.
Video 6: Ultrasound clip of needle in water bath with both ring down and reverberation artifacts. The tip of the needle appears to have a spotlight beam shining down,  this is an example of ring down artifact from trapped air at the needle tip. This video also demonstrates reverberation artifact where there appears to be a deeper hyperechoic (bright) needle at the bottom left of the video seen best at the beginning of the clip.

TECHNIQUE

Vein Selection: Upper Extremity

Typically, pediatric patients receive a peripheral IV in the upper extremity in one of 2 locations: 

  1. Antecubital fossa (Figure 4):
    • Access superficial veins, which includes the basilic, cephalic, and median cubital veins. 
    • Tip: Beware of tortuously curved paths of veins, branch points, and nearby nerves.
arm anatomy vein
Figure 4: Diagram of venous anatomy of the arm focused on antecubital fossa. The antecubital fossa area (the inside of the elbow) is shown in the blue box. Adapted from image By OpenStax College – Anatomy & Physiology, Connexions Web site. Jun 19, 2013. [CC BY 3.0]
  1. Upper arm near medial bicipital groove (Figure 5):
    • Access the deep brachial vein or more proximal aspect of the basilic vein.
upper arm vein anatomy
Figure 5: Diagram of venous anatomy of the upper extremity. By OpenStax College – Anatomy & Physiology, Connexions Web site. Jun 19, 2013. [CC BY 3.0]

Vein Selection: Lower Extremity

If unable obtain upper extremity access, the lower extremity can also be accessed. This is more typically performed in infants and young children. 

  • Lower medial leg (Figures 6, 7): This site allows for access to thegreat saphenous vein. 
leg vascular anatomy
Figure 6: Diagram of veins of the leg. Blausen.com staff (2014). “Medical gallery of Blausen Medical 2014“. WikiJournal of Medicine 1 (2). [CC BY 3.0]
Figure 7: Diagram of veins of the lower leg. Adapted from image by Blausen.com staff (2014). “Medical gallery of Blausen Medical 2014”. WikiJournal of Medicine 1 (2). [CC BY 3.0]

Set up for success

  • Prior to starting the procedure, set up the room for optimal visualization. 
  • Place ultrasound system monitor in direct line of site with the angiocatheter.
ultrasound set up position peripheral IV
Figure 8: Ultrasound machine positioning such that the probe, patient, and screen are in one line of sight.
  • Apply tourniquet around the extremity.
  • Use the high-frequency linear transducer (Figure 9) to identify potential veins before the procedure to map out the course, depth, and size of veins. Initial scanning can be done without sterile precautions. 
    • The best vein: The ideal vein is large, superficial, not near other anatomic structures, and relatively straight.
    • Depth: Set an appropriate depth on the ultrasound monitor such that the target vein is centered on the screen.
ultrasound linear probe
Figure 9: A high-frequency linear probe
  • Tip: Pre-scan multiple areas on both arms (or legs) to find the optimal site for ultrasound-guided peripheral IV placement. 
  • Cleaning and probe covers
    • Clean off any non-sterile gel from the patient’s skin.
    • Prepare the skin with chlorhexidine or an alcohol swab.
    • Use a single-use probe cover.
      • Consider a Tegaderm patch, sterile glove, condom, or sterile probe cover.
      • For further discussion of the relevant literature around probe covers, see this ALiEM post.
    • Use sterile ultrasound gel between the skin and the covered probe.
linear ultrasound probe cover glove
Figure 10: Sterile glove as a makeshift probe cover. Here the entire probe fits into a single finger of a sterile glove. For another method of using a sterile glove as a probe cover see this Trick of the Trade.

Probe Positioning

  • Proper orientation and terminology
    • In this procedure, there are 3 objects to coordinate in space. All of these relationships should be in a perpendicular or parallel orientation (not oblique). 
      • The vein
      • The probe
      • The needle 
    • The needle should always be parallel with (i.e., directly overlying) the vein. This leaves two other positional relationships: probe/vein and probe/needle. 
      • Probe/vein: The probe is either transverse or longitudinal relative to the vein (Figure 11).
      • Probe/needle:The needle is either out of plane (i.e., perpendicular) or in plane (i.e., parallel) relative to the length of probe. When using the transverse orientation, the needle is typically also perpendicular, or out of plane, with the length of the probe. Conversely, when using longitudinal orientation, the needle will be parallel, or in plane, with the probe.
ultrasound short and long axis linear probe
Figure 11: Labeled axes of linear ultrasound probe

POCUS-Guided IV Cannulation Technique

There are 2 approaches in using POCUS for cannulating peripheral veins based on if the operator is using the transverse or longitudinal orientation.

  1. Transverse orientation: This view is particularly helpful for keeping adjacent structures in view and requires less precision to keep the vein in view. It is important to keep in mind the distance the needle must travel to successfully enter the vein, which will depend on the angle of the needle and the depth of the vein. Videos 7 and 8 show the transverse orientation ultrasound views. Note that in this view, once the needle passes into the plane of the ultrasound beam,  it can be difficult to distinguish the tip of the needle from the shaft. 
Video 7: Ultrasound clip of a phantom model vein in transverse orientation with vein cannulation at end of clip. The needle can be identified based on the ring down artifact as it passes into the plane of the ultrasound beam.

Video 8: Ultrasound clip of a patient’s vein in transverse orientation with vein cannulation. The vessel is in the top center of the screen. The needle is the bright white (hyperechoic) dot entering it, seen out of plane.
  • Transverse technique (out of plane) with dynamic needle tip visualization: The shaft of the needle can appear indistinguishable from the tip of needle in the transverse or out-of-plane approach. The dynamic needle tip visualization technique allows the operator to continuously identify the location of the tip of the needle. 
    • As soon as the skin is entered, slide the probe closer towards the tip of the needle. 
    • Advance the probe just beyond the tip of the needle. As soon as the needle is no longer in view (i.e., just beyond the tip), it is clear where tip of the needle is. 
    • Hold the probe steady just beyond the needle tip, and advance the needle forward, returning it into the field of view. 
    • Advanced the probe just beyond the tip of the needle again.
    • Repeat the previous steps until the needle is visualized entering the vein.
      • Tip: Make small movements and attempt to keep the vein in the center of the screen. For beginners with this technique, it is recommended to alternate moving either the probe or the needle, one at a time.
Video 9: Ultrasound clip of a phantom model in transverse orientation with vein cannulation using dynamic needle tip visualization. The operator alternates moving the probe just beyond the tip of the needle and advancing the needle toward the vessel until cannulation. 

Video 10: Demonstration of the dynamic needle tip visualization technique, showing alternating movements of the probe and needle
  1. Longitudinal orientation: Conceptually, this orientation is more straightforward (probe, vein and needle are all parallel), but the precision involved requires a steady hand and a stationary patient. The needle must stay parallel to the probe within the slice thickness of the ultrasound beam. This value will vary depending on the machine and the probe, but is on the order of millimeters. Video 12 demonstrates the importance of maintaining the vein and needle parallel to the ultrasound beam or else the vein and/or needle disappears from view.
Video 11: Ultrasound clip with needle in and out of view using the longitudinal orientation technique. Being slightly out-of-plane makes it difficult to visualize the needle and needle tip. Of note, this needle has a guidewire extended past the needle tip which is curved slightly upward from the length of the needle.
  • Longitudinal (in plane) technique
    • Align the probe parallel to the vein. Ideally, the vein should be the same depth and thickness across the screen. 
    • Introduce the needle in-plane (parallel) to the probe marker at a shallow angle. Depending on the depth and size of the vein, this may be close to parallel with the skin.
    • Maintain visualization of the needle tip as it enters the vessel.
    • Tip: If it is unclear where the needle tip is, first stop moving the needle and assess if the probe has drifted or rotated. While keeping the needle still, make corrections with the probe until the needle and needle tip is once again visualized in plane. 

Video 12: Ultrasound clip of needle cannulating vessel in longitudinal view using in-plane technique

After Cannulation

After the needle tip is visualized entering the vein and a flash of blood appears in the hub of the needle, advance the needle forward an additional 1-2 mm before threading the catheter. Why? The catheter does not extend fully to the tip of the needle. Thus the needle must be advanced past the initial flash of blood to ensure that the catheter has also penetrated the vein. If there is resistance when threading the angiocatheter into the vein, reassess the needle tip position using the ultrasound and confirm the needle is still positioned intravascularly. 

Peripheral IV catheter with needle
Figure 12: Typical angiocatheter for peripheral IV access. The first few millimeters of the needle tip extend beyond the catheter.

After successful threading, retract the needle, attach pre-primed IV tubing, and flush and lock the tubing. Secure the catheter in place.

LITERATURE REVIEW

There have been many studies evaluating ultrasound-guided peripheral IVs in patients, and below are several key articles involving pediatric patients. Overall, ultrasound-guidance appears to be helpful in pediatric patients with difficult access, but the exact technique involved and the experience of the operator likely have an effect. 

YearAuthorsTitleMajor Findings
2009Doniger et al. [1]Randomized controlled trial of ultrasound-guided peripheral intravenous catheter placement versus traditional techniques in difficult-access pediatric patientsUltrasound-guided peripheral IV placement in difficult-access patients took less time, was more often successful, and required fewer needle re-directions.
2010Oakley and Wong [2]Ultrasound-assisted peripheral vascular access in a paediatric EDUltrasound-guidance was associated with slightly increased success rates in peripheral IV placement. This effect was more pronounced in cases with difficult-access patient.
2018Otani et al. [3]Ultrasound-guided peripheral intravenous access placement for children in the emergency department In contrast to many other publications on ultrasound-guided peripheral IV procedures, the authors report a LOWER success rate for patients that had one failed IV attempt, as compared to the conventional method. An important potential confounder was that this study used a “dual-operator” method, in which one clinician operates the ultrasound, and the other places the IV. 
2018Desai et al. [4]Longevity and complication rates of ultrasound guided versus traditional peripheral intravenous catheters in a pediatric emergency departmentUltrasound-guided peripheral IVs had a longer catheter survival time compared with traditionally-placed peripheral IVs. Complications from the peripheral IVs were similar between the two groups. 
Table: Key literature on pediatric cases studying ultrasound-guided peripheral IV access

References [click to expand] +

  1. Doniger SJ, Ishimine P, Fox JC, Kanegaye JT. Randomized Controlled Trial of Ultrasound-Guided Peripheral Intravenous Catheter Placement Versus Traditional Techniques in Difficult-Access Pediatric Patients. Pediatr Emerg Care. 2009;25(3):154-9. doi:10.1097/pec.0b013e31819a8946.
  2. Oakley E, Wong A-M. Ultrasound-assisted peripheral vascular access in a paediatric ED. Emerg Med Australas. 2010;22(2):166-70. doi:10.1111/j.1742-6723.2010.01281.x.
  3. Otani T, Morikawa Y, Hayakawa I, et al. Ultrasound-guided peripheral intravenous access placement for children in the emergency department. Eur JPediatr. 2018;177(10):1443-49. doi:10.1007/s00431-018-3201-3.
  4. Desai K, Vinograd AM, Abbadessa MKF, Chen AE. Longevity and Complication Rates of Ultrasound Guided Versus Traditional Peripheral Intravenous Catheters in a Pediatric Emergency Department. J Assoc Vascular Access. 2018;23(3):149-54. doi:10.1016/j.java.2018.06.002.

CASE RESOLUTION

Using POCUS, you begin by visualizing Abigail’s veins at the antecubital fossa and are able to identify the basilic and cephalic veins. Tracing the basilic vein proximally, you note that it is relatively large and straight; however, you see a honeycomb-like structure nearby it, which displays anisotropy and appears to be a nerve. You opt instead to follow the cephalic vein. There do not appear to be any nerves or other vessels nearby. You clean her skin appropriately and apply a sterile glove over the probe, and apply sterile gel. After these preparations, you re-identify the vessel in the transverse plane, use dynamic needle tip visualization with an out-of-plane approach, and successfully guide the tip of the needle into the vein. 

Video 13: Ultrasound clip of a vein in transverse orientation being successfully cannulated.

After visualizing the tip of the needle in the vein, you slightly advance the needle another 2 mm and then thread the catheter. You are able to obtain bloodwork. After flushing the catheter and cleaning the surrounding skin, you secure the catheter. Abigail is now able to get pain medications and fluids.

She soon feels much improved after 3 hours. Her laboratory results are similar to her baseline values. She is able to return home with ongoing management as an outpatient basis with close follow-up. 

The PEM POCUS series was created by the UCSF Division of Pediatric Emergency Medicine to help advance pediatric care by the thoughtful use of bedside ultrasonography.

Read other PEM POCUS tutorials. Learn more about bedside ultrasonography on the ALiEM Ultrasound for the Win series.

By |2026-05-21T10:09:19-07:00May 24, 2021|PEM POCUS, Ultrasound|

PEM POCUS Series: Hip Effusion

Read this tutorial on the use of point of care ultrasonography (POCUS) for pediatric hip effusion. Then test your skills on the ALiEMU course page to receive your PEM POCUS badge worth 2 hours of ALiEMU course credit.


PATIENT CASE: Child with a Limp

Sarah is a 4-year-old girl who comes into the emergency department complaining of a limp for the last day. She had an upper respiratory infection which started a week ago for which she had been taking acetaminophen and ibuprofen with her last dose of either being 2 days ago. Those symptoms have improved. Yesterday, she started complaining of diffuse right leg pain primarily at her hip, thigh, and knee. Today, her parents noted she was walking with a limp.

On arrival, her vital signs are:

Vital SignFinding
Temperature100.1F
Heart rate100 bpm
Blood pressure97/50
Respiratory rate19
Oxygen saturation (room air)100%

She is well appearing and walks with an antalgic gait favoring the left leg. She has a normal HEENT, neck, cardiac, respiratory, abdominal, and back examination. She points to her right anterior thigh when you ask her where her pain is. She has limited range of motion with internal and external rotation of her right hip and complains of pain. She cries when you palpate any part of her leg, but is able to range her knee, ankle, and foot fully. She has 2+ dorsalis pedis and posterior tibialis pulses and intact sensation to light touch throughout. 

Given her pain with range of motion at her hip, you order a hip radiograph, but while waiting for it, decide to perform a hip point of care ultrasound (POCUS) examination.

PEDIATRIC HIP EFFUSION: Ultrasound Technique

It can be difficult for children to locate the exact area of pain and often hip pain can present with referred knee and thigh pain. A thorough physical examination along with hip POCUS can help localize the area of discomfort. When we use POCUS to evaluate the hip, we are primarily looking for a joint effusion in the synovial space. This is best visualized anterior to the femoral neck.  

hip anatomy hip effusion
Figure 2. Hip anatomy with target landmark being the femoral neck (red arrow) 

Technique

  1. The patient should be positioned supine.
    • Depending on the age of the child, the child can be positioned supine in the guardian’s lap while undergoing the examination. 
    • Offering the child a toy, book, or phone/tablet for distraction during the examination can also help ease anxiety.
  2. Use a linear high frequency transducer with a wide footprint.
  3. Place the transducer along the anterior hip.
    • Use the greater trochanter as a lateral landmark and place the probe on top of the femoral head and neck (Figure 3)
  4. Aim the probe marker towards the patient’s umbilicus.
hip effusion ultrasound
Figure 3. Linear transducer at the hip with probe marker (red dot) aimed towards the patient’s umbilicus
  1. Identify the anatomical landmarks on ultrasound (figure 4) 
    • Hip muscles: Sartorius, quadriceps, and iliopsoas
    • Bones: Femoral head, femoral neck
  2. The area of interest in looking for a hip effusion is the synovial space anterior to the femoral neck and NOT anterior to the femoral head. This area is also referred to as the anterior synovial recess.
Figure 4. Ultrasound image showing the normal landmarks for a pediatric hip without an effusion and the location of the femoral head (X) and synovial space (circle) with the linear transducer positioned overlying and longitudinal to the femoral neck
  • Tips:
    • It is often helpful to ultrasound the unaffected side as a comparison.
    • Be aware of the patient’s comfort throughout the examination.

ABNORMAL ULTRASOUND FINDINGS

A hip effusion will appear anechoic (black) in the synovial space anterior to the femoral neck (anterior synovial recess). Measure the distance between the anterior surface of the femoral neck and the posterior surface of the iliopsoas muscle. Examples are illustrated in figures 5 and 6.

hip effusion PEM POCUS ultrasound

There have been different methods used to assess if an effusion is present including:​1,2​

  • Measured effusion is >0.5 cm 
  • Measured effusion with >0.2 cm difference compared to the contralateral hip
  • Gestalt view with the anterior synovial recess areas appearing asymmetric compared to the other hip

Limitations of the Hip POCUS

Note that hip POCUS does not tell you the cause of an effusion but rather only whether an effusion is present or not. Effusions can result from infectious, inflammatory, and traumatic etiologies, and thus it is important to take into account the context of the patient’s presentation. 

References

  1. Vieira R, Levy J. Bedside ultrasonography to identify hip effusions in pediatric patients. Ann Emerg Med. 2010;55(3):284-289. PMID 19695738
  2. Cruz C, Vieira R, Mannix R, Monuteaux M, Levy J. Point-of-care hip ultrasound in a pediatric emergency department. Am J Emerg Med. 2018;36(7):1174-7. PMID 29223689 

FACTS and LITERATURE REVIEW

There have been multiple case reports of hip POCUS identifying hip effusions in children with fractures, septic joints, and in the work-up of children with limps [1–4]. There are limited studies examining the accuracy of hip POCUS compared to radiology-performed ultrasounds in children. The studies that exist show high sensitivity and specificity when hip POCUS is performed by pediatric emergency medicine (PEM) physicians (Table 1).

Additional studies have explored the development of hip effusion clinical decision-making tools to support POCUS in the diagnosis of transient synovitis and differentiate it from other causes of non-traumatic arthritis in patients with a hip effusion, including septic arthritis, Lyme arthritis, and osteomyelitis [5]. For example, one retrospective pilot study found that the combination of POCUS performed by PEM physicians and a clinical decision rule could correctly rule in transient synovitis in 63 of 67 patients with a hip effusion [6].

The use of POCUS in the ED has also been associated with cost savings and greater clinical efficiency. In pediatric patients, hip POCUS has demonstrated potential cost-saving benefits compared with radiology-performed ultrasound. One Australian economic evaluation estimated annual savings of approximately AU$35,800 (about US$25,000), mainly by shortening the time children spent in an ED bed waiting for an ultrasound [7]. Additionally, in a case series of 10 children with septic arthritis of the hip, POCUS-guided hip aspiration by a PEM-trained physician was associated with a shorter time to antibiotic administration [1].

Although standardized training requirements for hip effusion POCUS in pediatric patients have not been established, scanning accuracy appears to be influenced by operator experience and confidence. As illustrated in Table 1, sensitivity and specificity were higher among physicians who had performed more hip POCUS scans and among those with greater confidence in their ultrasound skills [8,9,11]. These findings highlight the importance of continued practice and experience in developing proficiency in hip POCUS, ultimately improving diagnostic accuracy and supporting timely clinical decision-making. So, make sure to keep scanning!

StudyNSensitivitySpecificityComments
Vieira et al., Ann Emerg Med, 2010 [8]2885%93%If the pediatric emergency physician had a high confidence in ultrasound accuracy, the sensitivity increased to 90% and specificity to 100%.
Cruz et al., Am J Emerg Med, 2018 [9]51685%98%For each additional hip POCUS performed, the odds of an accurate scan increased by 2.4%.
Katz-Dana et al., CJEM, 2024 [10]9589.8%91.3%Strong positive LR of 10.33 and negative LR of 0.11 for PEM physician-performed POCUS.
Jones et al., Ann Emerg Med, 2025 [11]161 (322 hips)89.3%99.2%For the 3 high-volume pediatric emergency physicians, sensitivity and specificity increased to 98.1% and 97.8%, respectively. Sensitivity and specificity are per hip.
Table 1. Published studies comparing pediatric hip POCUS to radiology-performed ultrasound


References [click to expand] +

  1. Berant R, Bder M, Kaufman-Shriqui V, Shahar-Nissan K. Point-of-Care Ultrasound-Guided Aspiration of the Hip Joint by an Emergency Medicine Physician: A Pediatric Retrospective Case Series. Pediatr Emerg Care. 2022;38(3):139-142. doi:10.1097/PEC.0000000000002650. PMID: 35226624.
  2. Deanehan J, Gallagher R, Vieira R, Levy J. Bedside hip ultrasonography in the pediatric emergency department: a tool to guide management in patients presenting with limp. Pediatr Emerg Care. 2014;30(4):285-287. doi:10.1097/PEC.0000000000000113. PMID: 24694889.
  3. Garrison J, Nguyen M, Marin J. Emergency Department Point-of-Care Hip Ultrasound and Its Role in the Diagnosis of Septic Hip Arthritis: A Case Report. Pediatr Emerg Care. 2016;32(8):555-557. doi:10.1097/PEC.0000000000000874. PMID: 27490732.
  4. Tsung J, Blaivas M. Emergency department diagnosis of pediatric hip effusion and guided arthrocentesis using point-of-care ultrasound. J Emerg Med. 2008;35(4):393-399. doi:10.1016/j.jemermed.2007.10.054. PMID: 18403170.
  5. Chan N, McCreary DJ, Nedyalkova A, Snelling PJ. Point-of-care ultrasound for the diagnosis of hip effusion in children presenting to the emergency department with atraumatic limp or hip pain: a scoping review. J Ultrasound Med. 2026;45(10):2109-2118. doi:10.1002/jum.70286. PMID: 42104527.
  6. McCreary DJ, Chowdhury R, Hamilton C. Can a POCUS Clinical Decision Rule Improve Reliability in the Diagnosis of Paediatric Transient Synovitis of the Hip? A Single Centre Pilot Study. POCUS J. 2025;10(2):103-108. doi:10.24908/pocusj.v10i02.18290. PMID: 41322175.
  7. Bailey C, Deane H, O’Brien A, Dalziel K. An economic evaluation of point-of-care ultrasound for children presenting to the emergency department with suspected septic arthritis of the hip. Aust Health Rev. 2024;48(1):37-44. doi:10.1071/AH23214. PMID: 38266497.
  8. Vieira R, Levy J. Bedside ultrasonography to identify hip effusions in pediatric patients. Ann Emerg Med. 2010;55(3):284-289. doi:10.1016/j.annemergmed.2009.06.527. PMID: 19695738.
  9. Cruz C, Vieira R, Mannix R, Monuteaux M, Levy J. Point-of-care hip ultrasound in a pediatric emergency department. Am J Emerg Med. 2018;36(7):1174-1177. doi:10.1016/j.ajem.2017.11.059. PMID: 29223689.
  10. Katz-Dana H, Stackievicz R, Dana E, et al. Diagnostic accuracy of point-of-care ultrasound (PoCUS) for the diagnosis of hip effusion in the pediatric emergency department. CJEM. 2024;26(12):875-882. doi:10.1007/s43678-024-00788-z. PMID: 39352610.
  11. Jones RM, Malia L, Snelling PJ, et al. Diagnostic Accuracy of Point-of-Care Ultrasound for Hip Effusion: A Multicenter Diagnostic Study. Ann Emerg Med. 2025;86(6):566-575. doi:10.1016/j.annemergmed.2025.04.033. PMID: 40481828.

CASE RESOLUTION

The patient’s hip plain film radiographs are unremarkable. You decide to incorporate hip POCUS to your evaluation. You place a linear, high-frequency transducer and visualize the patient’s bilateral hips. You observe the following:

Right Hip (Affected Side) POCUS Video and Key View

Though the child complained of hip, knee, and thigh pain, your POCUS evaluation identifies a right hip effusion which helps you narrow the location of her pain.

Video 1. A hip POCUS of the case patient’s right hip (affected side)


PEM POCUS hip effusion
Figure 7. Right (affected side) hip POCUS with a hip effusion measuring 0.77 cm

Left Hip (Normal Side) POCUS Video and Key View

Video 2. A hip POCUS of the case patient’s left hip (unaffected side) for comparison


PEM POCUS hip no effusion normal
Figure 8. Left (unaffected side) hip POCUS with no effusion

ED Course

The patient’s labs result, and she has reassuring labs, which include a serum WBC 8.3 x109/L and ESR 34 mm/hr. The patient receives ibuprofen during her visit and within 1 hour is able to walk without a significant limp and states she feels better. The patient’s family notes they have spent the last few weeks of summer in a Lyme-endemic region, and so you send off Lyme titers.

Given the resolution of limp, lack of fever, and reassuring lab values, you do not believe the patient has a septic joint. Her effusion is more likely the result of a transient synovitis. You recommend close pediatrician follow-up.

Pediatrician Clinic Follow-Up

At her pediatrician clinic visit 1 week later, her Lyme titers return negative, and the patient continues to be limp-free.  


The PEM POCUS series was created by the UCSF Division of Pediatric Emergency Medicine to help advance pediatric care by the thoughtful use of bedside ultrasonography.

Read other PEM POCUS tutorials. Learn more about bedside ultrasonography on the ALiEM Ultrasound for the Win series.

By |2026-10-15T12:39:29-07:00May 17, 2021|Orthopedic, PEM POCUS, Ultrasound|

Caring for the Fasting Patient in the ED

Ramadan

Millions of Muslims around the world observe the holy month of Ramadan. Some may have mild or chronic medical conditions that can become exacerbated, requiring emergent medical attention. Emergency Physicians ought to have a working knowledge about the religious rules of Ramadan and their medical implications. In this article, we will provide an overview of the significance of Ramadan to Muslims, its practices, and discuss the important considerations for emergency physicians when providing care to Muslim patients in the Emergency Department (ED). Lastly, we will explore ways to mitigate the ethical dilemma when a fasting patient refuses a life-saving treatment or intervention.

The significance of the holy month

Ramadan is the holiest month of the year for 1.9 billion Muslims around the world [1]. Muslims believe that the month of Ramadan is the month during which the prophet Muhammad received the initial revelations of the Quran, the holy book for Muslims [2].

Ramadan is a time of spiritual reflection, self-improvement, heightened devotion, and worship. Muslims are expected to put more effort into following the teachings of Islam. Fasting is one of the five fundamental principles of Islam; known as the Five Pillars of Islam. The pillars include shahada (a declaration of faith: “There is no deity but God, and Muhammad is the messenger of God”); prayer (Muslims pray five times a day); zakat (charitable giving); fasting and pilgrimage (Muslims are supposed to make a trip, or “hajj,” to the city of Mecca, Saudi Arabia, at least once in a lifetime if they are physically and financially able).

The fast begins at dawn and ends at sunset [3]. The act of fasting is said to redirect the heart away from worldly activities. It serves the purpose of cleansing the soul by freeing it from harmful impurities. Muslims believe that Ramadan teaches them to practice self-discipline, self-control, sacrifice, and empathy for those who are less fortunate, thus encouraging actions of generosity and communal charity.

Many mosques (Islamic places of worship) host daily community dinners where Muslims can break their fast together. Since Ramadan is a time for Muslims to be especially charitable and fasting helps Muslims feel compassion for the hungry and less fortunate, many mosques hold food drives or fundraisers for charity during Ramadan. It is also common for mosques to host open houses for their friends and neighbors of other faiths to join them for their fast-breaking feast or iftar at the end of the fasting day.

A 2017 study estimated that 3.45 million Muslims were living in the United States, about 1.1 percent of the total U.S. population [4]. Emergency physicians should be aware of the health considerations for their Muslim patients during the month of Ramadan.

How long do Muslims fast? Are there exemptions to fasting?

Ramadan is the ninth month of the 12-month Islamic calendar, a lunar calendar that’s based on the phases of the moon. The lunar calendar falls short of the solar calendar by 11 days. As a result, Ramadan doesn’t start on the same date each year and instead, over time, passes through all the seasons. In 2021, Ramadan began on April 13th and ended on May 13th. Depending on its timing of the year and the location in the world, some patients may be fasting for up to 20 hours. This extended period without food, water, and medications may pose a serious health risk to patients with certain medical conditions.

Exemptions to fasting include anyone who is traveling, women who are pregnant, breastfeeding, or menstruating, or those with acute or chronic illnesses [5].

However, many Muslims with medical conditions insist on fasting to satisfy their spiritual needs. Although Islam does not recommend it, as medical professionals, we must respect our patients’ choices. Those excused can make up the fast later or feed one poor person for each day missed. “And anyone who is ill or on a journey should make up for the lost days by fasting on other days later. God wants ease for you, not hardship.” (Quran 2:185)

I have a fasting patient in the ED. What should I do?

As previously stated, Muslims with acute or chronic conditions such as diabetes are exempt from fasting. However, they may still choose to fast. They may discontinue their medications or alter treatment regimens with or without involving their primary care physician. As a result, serious complications may develop. Patients can present to the ED with dehydration, syncope, hypo- or hyperglycemia, diabetic ketoacidosis, or congestive heart failure. ED clinicians need to approach the care of these patients with empathy and support, along with shared decision-making regarding their treatment plans and expectations.

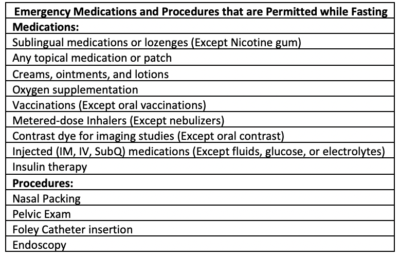
Another important aspect of caring for these patients is the knowledge that many ED interventions can invalidate fasting. Intravenous fluid is one such example. Before you empirically order that liter of saline solution for the fasting patient who presents to the ED with dehydration, recognize that it will invalidate their fast and consider other options or have a discussion with the patient and/or their family members. The table below lists some medications and procedures that can be applied without breaking the fast [4,6].

Ramadan

Empathy is key in the critically ill fasting patient who is refusing care

There are unique challenges in managing patients who are critically ill and refuse to break their fast. Spirituality, religiosity, and personal beliefs are essential components of the social determinants affecting patients’ health behavior and acceptance of treatment. Depending on their cultural and religious upbringing, some patients believe their hardship, patience, and perseverance through challenges will grant them God’s mercy and forgiveness. This religious context will help guide the emergency physician when caring for the critically ill fasting patient. Fasting that endangers health or increases morbidity is not in accordance with Islamic jurisprudence. For example, if a patient presents to the ED with an acute illness that requires a blood transfusion, then they are exempt from fasting. A gentle reminder to your patients that even if they break their fast, they can make it up on another day.

Fasting beyond Ramadan

The holy month of Ramadan ends with Eid al-Fitr which is a holiday celebrated by Muslims around the world to mark the end of the sunset-to-dawn fasting of Ramadan. The festivities start with a morning prayer followed by family gatherings and sharing of food and gifts with neighbors and the local communities. It is important for physicians and ED clinicians to know that some Muslims may elect to observe six days of fasting after the day of Eid al-Fitr. In Islamic traditions, these six days of fasting along with the Ramadan fast are equivalent to fasting all year. In Islam, every good deed is rewarded 10 times, hence fasting 30 days of Ramadan and 6 days during the following month (Shawwal) is equivalent to a whole year fast. Many Muslims religiously follow this practice throughout their lifetimes. Some Muslims will follow the tradition (or Sunna) of the prophet Muhammad by fasting on Mondays and Thursdays every week. Therefore, physicians could care for a fasting patient throughout the year, beyond Ramadan, and should have an understanding of the religious and cultural context of the Muslim traditions when caring for these patients in the ED.

Summary

  • Millions of Muslims around the world fast during the holy month of Ramadan from sunrise to sunset.
  • Muslims with chronic conditions, those who are critically ill, or present to the ED with acute exacerbation of their chronic conditions are exempt from fasting. However, some may choose to continue to fast despite their underlying illnesses.
  • Some medications and medical procedures are allowed during fasting. Providing IV fluid for hydration will invalidate fasting.
  • It is important for emergency physicians to understand the cultural and religious context of fasting for Muslims in order to improve the experiences of these patients when they are cared for in the ED. Empathy and shared decision-making go a long way.
  • Finally, ways to greet your patients during Ramadan and Eid al-Fitr:
    • Ramadan Mubarak: Blessed Ramadan
    • Ramadan Kareem: Generous Ramadan
    • Aid Mubarak: Blessed Aid (day of festivities after Ramadan)

References

  1. Islamic world, countries with a cultural Islamic population – Nations Online Project. Accessed May 13, 2021. https://www.nationsonline.org/oneworld/muslim-countries.htm.
  2.  Mubārakpūrī, Ṣafī R. (1998). When the Moon Split (A Biography of the Prophet Muhammad). Riyadh: Darussalam. p. 32.
  3.  Ramadan 2015: Facts, History, Dates, Greeting, And Rules About The Muslim Fast Archived 10 July 2015 at the Wayback Machine, Huffington Post, 15 June 2015.
  4. “New estimates show U.S. Muslim population continues to grow”. Pew Research Center. January 3, 2018.
  5. El-Bahay El-Kholi. Al Siyam, “Fasting”. The Supreme Council for Islamic Affairs, Arab Republic of Egypt. p. 36
  6. Al-Munajjid SM. He Needs to Have an Injection into a Vein – Will that Affect His Fast?  http://www.islam-qa.com/
  7. Al-Munajjid SM. Types of Asthma Medication and the Ruling on Taking Them during the Day in Ramadan. http://www.islam-qa.com/

PEM POCUS Series: Intussusception

PEM POCUS Intussusception badge

Read this tutorial on the use of point of care ultrasonography (POCUS) for pediatric intussusception. Then test your skills on the ALiEMU course page to receive your PEM POCUS badge worth 2 hours of ALiEMU course credit.

PATIENT CASE

Johnny is a 2-year-old boy who comes into the emergency department for abdominal pain for the last day. His parents are concerned that he has been having intermittent abdominal pain and has seemed very tired all day. Parents deny bloody stool.

On arrival, his vital signs are:

Vital Sign Finding
Temperature 36.9C
Heart rate 110 bpm
Blood pressure 97/50
Respiratory rate 22
Oxygen saturation (room air) 99%

He is tired appearing, and his abdominal exam is soft but diffusely tender. Given his intermittent abdominal pain, you decide to perform an intussusception point of care ultrasound (POCUS) exam.

ULTRASOUND TECHNIQUE

Intussusception is when one part of the bowel telescopes, or gets stuck, in another part of the bowel. Typically intussusception refers to ileocolic intussusception where the ileum becomes stuck in the colon. To perform the ultrasound, start in the right lower quadrant and trace the colon. See below for a step-by-step technique.

intussusception
Overview of sequential ultrasound transducer positioning on the anterior abdomen to assess for intussusception

Technique

  • The patient should be positioned supine.
  • To aid in comforting the child, the child can be positioned supine in the parent’s lap while undergoing the scan. Having the parent or another provider offer a toy, book, or phone/tablet to distract the child during the scan can also help ease anxiety.
  • Begin in the right lower quadrant (RLQ), using a high frequency linear probe with the probe marker to patient’s right.
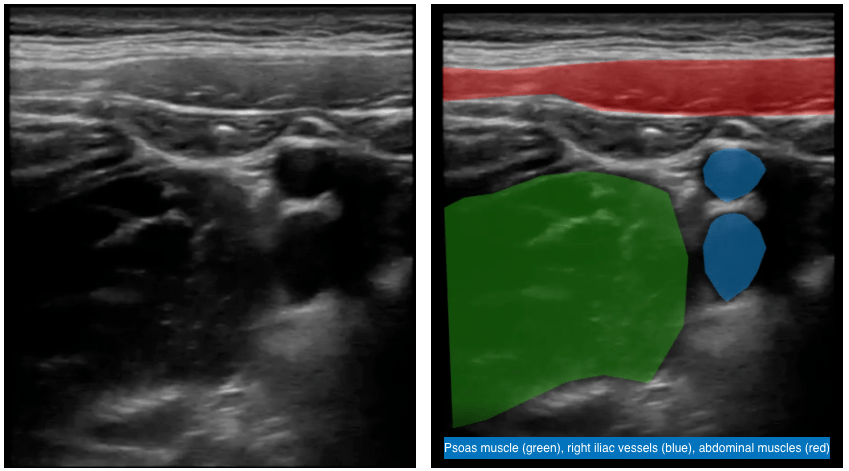
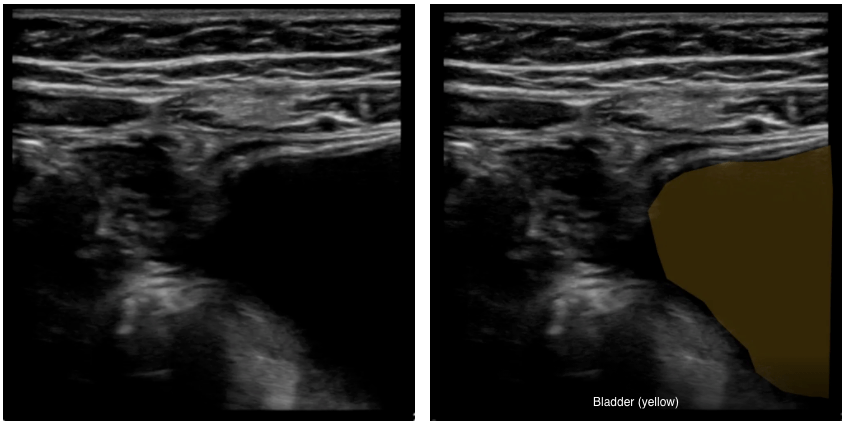
  • First, identify the anatomical landmarks in the RLQ (see ultrasound images below):
    • Psoas muscle (green) laterally
    • Right iliac vessels (blue)
    • Abdominal muscles (red)
    • Bladder (yellow) medially

Ultrasound image: Anterior Abdomen (RLQ) View

intussusception RLQ ultrasound

Ultrasound Image: Anterior Abdomen RLQ (More Medial) View

PEM POCUS intussusception RLQ More Medial
  • Perform graded compression, with slow steady pressure to displace bowel gas
  • Follow the colon from the RLQ to right upper quadrant (RUQ) until the liver (purple) and gallbladder are identified

Ultrasound Image: Anterior Abdomen (RUQ) View

PEM POCUS intussusception RUQ
  • Rotate the probe marker to patient’s head and scan the entire length of the transverse colon.
  • Rotate the probe marker back to patient’s right and scan the entire length of the descending colon, making sure to scan all four quadrants.
  • Save representative video clips and still images of each quadrant.
  • If an intussusception is found, measure its diameter in transverse view and note in which quadrant(s) it is found.
  • At the end of scan, if you have found an intussusception, re-image the abdomen to make sure it was not transient.
  • The provider should maintain awareness of the patient’s comfort throughout the scan.

INTUSSUSCEPTION CLASSIC FINDINGS

Normal (no intussusception)

Normal: There is no target or sandwich sign, but rather just folded normal bowel. (To replay, press circular arrow in bottom left corner)

Abnormal findings

  • Look for findings of a sandwich sign (or pseudo-kidney sign) in the longitudinal view and target sign (or donut sign) in the transverse view.
  • If visualized, measure the diameter of the intussusception in short axis (transverse) and note which in which quadrant(s) it is located.

Sandwich

Anterior abdomen ultrasound: Intussusception – Presence of a sandwich sign (long axis view) and target sign (short axis view)

Target Sign

Intussusception diameter ultrasound
Measurement: The diameter of an intussusception (i.e., target sign) in transverse view involves measuring the distance from outer wall to outer wall.

Additional Anterior Abdominal Ultrasound Videos

Pro Tip
It can be difficult to distinguish intussusception of the small bowel-small bowel (i.e., when the ileum or part of the small bowel telescopes into itself) versus ileocolic (i.e., when the ileum becomes telescopes into the colon). The former often does not require a procedure for reduction, while the latter typically does. If the target sign diameter is <2 cm and transient, a small bowel-small bowel intussusception should be suspected. The length of the intussusception, or how many quadrants are involved, can also be measured for an idea of how much bowel is involved.

Small bowel-small bowel intussusception

Small bowel-small bowel intussusception – Note the small size of the target lesion. Because the ultrasound video scans to a depth of 3.3 cm (see bottom right side of the screen), the target sign appears to be approximately only 1 cm in diameter.


Small bowel-small bowel intussusception – There is a target sign, but it is small (<2 cm) with a small fat (white) core.


Ileo-colic intussusception

Ileo-colic intussusception with classic target sign – Note the lymph nodes (black) inside the mesenteric fat (white) in the center of the target.

FACTS and LITERATURE REVIEW

Mimickers of Intussusception

There are additional pathologies that can be mistaken for intussusception such as an intussuscepted appendix, appendicitis surrounded by abscess, and Meckel’s diverticulum, which are beyond the scope of this course. Any concerning finding for intussusception should be followed by a confirmatory study by the radiology department.

Benefits of intussusception POCUS scans

There have been several studies examining point-of-care ultrasonography (POCUS) for intussusception, which have shown excellent test characteristics and a decreased length of stay when using POCUS. POCUS also has no radiation exposure and may further help reduce morbidity by reducing delays in diagnosis of intussusception [1].

POCUS performed by PEM physicians has demonstrated a high level of accuracy in diagnostic agreement with radiologist-performed ultrasounds. For example, in a study by Arroyo et al., POCUS agreement with radiologist-performed ultrasounds occurred in 97 of 100 cases [1]. There is also research comparing positive ultrasound diagnosis (including POCUS and radiologist-performed ultrasound) of intussusception to confirmatory surgical or contrast enema, as exhibited by the table below.

Below is a table of test characteristics of POCUS for intussusception.

Publication Methodology Sensitivity Specificity
Riera et al. (2012) [2] Prospective study of 82 patients who underwent POCUS by pediatric emergency medicine (PEM) providers. The gold standard was a comprehensive radiology ultrasound. 85% 97%
Trigylidas et al. (2019) [3] Retrospective study of 102 POCUS exams in 101 patients by PEM providers. The gold standard was pediatric radiologist confirmation by review of the POCUS images, a radiology department ultrasound, or an air enema. 96.0% 92.6%
Lee et al. (2020) [4] This retrospective study included 575 scans from 549 patients aged 1 month to 6 years with clinically suspected ileocolic intussusception, who underwent POCUS performed by PEM physicians of a tertiary hospital. The gold standard for comparison was radiologist-performed ultrasound. 100% 95.6%
Bergmann et al. (2021) [5] This prospective study of 256 children across 17 sites (35 PEM physicians with experience/extra training in POCUS) compared POCUS and radiologist-performed ultrasound using a gold standard of clinically important intussusception which was defined as an intussusception that required radiographic or surgical reduction during or within 7 days of the incident ED visit. 96.6% 98%
Tonson la Tour et al. (2021) [6] This prospective study included 131 children evaluated by POCUS, of whom 45 (34%) had an intussusception. Twenty-four PEM physicians with various levels of training performed POCUS and were able to identify 39 of 45 intussusception cases. PEM-performed POCUS was then compared to the gold standard, radiologist-performed ultrasound. Interestingly, diagnostic accuracy did not differ significantly between novice and experienced sonographers. 87% 97%
Lin-Martore et al. (2022) [7] This systematic review and meta-analysis of diagnostic accuracy of POCUS for intussusception included 2400 patients and 11 studies. The POCUS evaluation of the lesion was performed by an adult or pediatric emergency physician. Each study consisted of a gold standard test including radiologist-performed ultrasonography, other radiology diagnostic imaging, air enema, or patient follow-up. 95.1% 98.1%
Rahmani et al. (2023) [8] This meta-analysis included 37 studies to calculate the pooled sensitivity and specificity of ultrasound diagnosis of intussusception. The studies included used POCUS results from EM physicians and residents, sonography technicians, and one used a PEM physician certified in pediatric gastroenterology. It also included radiology-performed ultrasound. Each study consisted of comparison to a gold standard including radiologist-performed ultrasound, clinical follow-up, surgical report, and air or barium enema. 96% 97%
Alsabri et al. (2026) [9] This meta-analysis includes a total of 44 studies (prospective and retrospective cohort studies, cross-sectional studies, and case-control studies) for pooled sensitivity and specificity of ultrasound for diagnosing intussusception. It includes POCUS from PEM physicians and radiology ultrasounds. The gold standard of confirmation included surgical findings, clinical follow-up, and contrast enema (barium and air). 96.3% 95.7%
Table 1. Test characteristics of ultrasound for intussusception

In terms of Emergency Department (ED) length of stay (LOS), Kim et al. (2020) reported that after the introduction of an intussusception POCUS scanning protocol for PEM physicians to implement in the ED, the LOS decreased by more than 200 minutes [10]. An additional study has shown that a POCUS-first pathway can be a way to expedite care for children with suspected intussusception in the ED, leading to reduced physician initial assessment to reduction time by an average of 69.9 min when compared to traditionally waiting for radiologist-performed ultrasound evaluation [11].

Differentiating small bowel-small bowel from ileocolic intussusception

In general, true ileocolic intussusceptions are:

  • Found on the right side of the abdomen
  • >2 cm in diameter
  • Have mesenteric fat (which is white) and lymph nodes in the center
  • Do not self-resolve

There have been studies looking at distinguishing small bowel-small bowel intussusception (SB-SBI) from ileocolic intussusception (ICI). Most of these, however, have been radiology-based rather than POCUS studies, making generalizability to the ED setting challenging. Thus, if there is a concern for an intussusception, a radiology ultrasound should be ordered.

In a small study of 27 patients, Wiersma et al. (2006) [12] found that SB-SBI had smaller mean diameters and shorter lengths than ICI. Consistent with these findings, a more recent study reported similar findings, with all ICI cases in the study having lesion diameters greater than 2 cm [13]. This study also suggested a difference in age distribution between the two intussusception lesions studied: patients with SB-SBI tended to be older and exhibited a wider age range, whereas the ICI group consisted predominantly of infants younger than 1 year [13].

Study author and year N (patients) Age (mean or median) Mean diameter Mean length Notes
Wiersma et al. (2006) [12] SB-SBI: 10
ICI: 14
SB-SBI: 3.1 yr (mean)
ICI: 1.9 yr (mean)
SB-SBI: 1.5 cm
ICI: 3.7 cm
SB-SBI: 2.5 cm
ICI: 8.2 cm
SB-SBI: Lesions were located throughout the abdomen (6 paraumbilical, 2 RUQ, 2 RLQ, 1 LLQ).
All ICI lesions were located on the right side of the abdomen.
Park et al. (2019) [13] SB-SBI: 21
ICI: 16
SB-SBI: 54 mo (median)
ICI: 8 mo (median)
SB-SBI: 1.68 cm
ICI: 2.74 cm
Not reported SB-SBI was identified more frequently than ICI in this cohort when using POCUS screening tool, which may be due to rapid detection by POCUS and/or lower threshold for evaluating for intussusception.
Goel et al. (2020) [14] SB-SBI: 21
ICI: 33
SB-SBI: 17.3 mo
ICI: 22.2 mo
SB-SBI: 2.13 cm
ICI: 3.24 cm
SB-SBI: 3.17 cm for obstructive cases and 1.93 cm for transient cases
ICI: Not reported
The team noted an optimal threshold of 2.5 cm to distinguish between transient and obstructive SB-SBIs. Lymph nodes were present in 18 (33.3%) out of 54 surgically confirmed cases, and all were ICI.
Table 2. Studies comparing SB-SBI versus ICI

Lioubashevsky et al. (2013) [15] evaluated a larger cohort of 174 patients and reported similar findings. In addition to assessing the inner fat core-to-outer wall thickness ratio, the authors examined the presence or absence of lymph nodes within the intussusception. These findings were supported by Zhang et al. (2021) [16], who identified lymph nodes in only one case of SB-SBI, compared with 56 cases (93%) of ICI. Zhang et al. also found that the fat core was visible on ultrasound in all cases of ICI but was absent in 16% of SB-SBI cases [16]. Similarly, Goel et al. reported an inner fat core-to-outer wall thickness ratio > 1 in all cases of ICI and < 1 in all cases of SB-SBI, further supporting the diagnostic utility of this sonographic feature [14].

These differences may be explained by the underlying anatomical and physiological characteristics of the involved bowel segments [14,15]. The mesentery associated with the ileocolic region contains greater amounts of adipose tissue and lymph nodes than the mesentery involved in SB-SBI [14-16]. This could explain why ileocolic intussusceptions tend to demonstrate greater lymph node and fat involvement, appearing as hyperechoic structures on ultrasound [15-17]. The increased proportion of mesenteric fat and lymphatic tissue may also contribute to the larger diameter of ICI lesions [14,16,17]. In contrast, the shorter length of SB-SBI lesions reported in previous studies may be attributable to active bowel peristalsis and the greater likelihood of spontaneous resolution in these cases [16,17].

Subramaniam et al. (2022) [18] looked at POCUS differentiating SB-SBI from ICI. Similar to above, they noted the predominant location of SB-SBI in the periumbilical or left abdomen compared with the right-sided predominance of ICI; the larger diameter of ICI, typically greater than 2.5 cm; the greater length of ICI, typically exceeding 3 cm; the presence of lymph nodes within ICI; the presence of peristalsis within SB-SBI; and the larger core-to-wall index associated with ICI [18].

While beyond the scope of this module, there is some evidence that POCUS may facilitate the treatment of intussusception in addition to its diagnostic utility. Zymerman et al. (2026) [19] reported a case series of 9 reductions with an 88.9% success rate for POCUS-guided hydrostatic reduction of ICI performed at the bedside by a pediatric emergency medicine physician. Similarly, Atia et al. (2026) [20] reported a retrospective chart review with 24 of 28 ICI (86%) successfully reduced when ICI was diagnosed using POCUS and bedside ultrasound-guided hydrostatic reduction was performed by a pediatric radiologist. This study also reported a mean time from admission to reduction of 126 minutes and a mean hospital length of stay of 407 minutes [20]. Together, these findings suggest that POCUS may serve not only as a reliable diagnostic tool for differentiating ICI from SB-SBI but also as a means of facilitating timely and effective bedside therapeutic intervention.

References [click to expand] +

  1. Arroyo AC, Zerzan J, Vazquez H et al. Diagnostic accuracy of point-of-care ultrasound for intussusception performed by pediatric emergency medicine physicians. J Emerg Med. 2021;60(5):626-632. doi:10.1016/j.jemermed.2020.11.030. PMID: 33483198.
  2. Riera A, Hsiao A, Langhan M, Goodman T, Chen L. Diagnosis of intussusception by physician novice sonographers in the emergency department. Ann Emerg Med. 2012;60(3):264-268. doi:10.1016/j.annemergmed.2012.02.007. PMID: 22424652.
  3. Trigylidas TE, Hegenbarth MA, Patel L, Kennedy C, O’Rourke K, Kelly JC. Pediatric emergency medicine point-of-care ultrasound for the diagnosis of intussusception. J Emerg Med. 2019;57(3):367-374. doi:10.1016/j.jemermed.2019.06.007. PMID: 31405782.
  4. Lee JY, Kim JH, Choi SJ, Lee JS, Ryu JM. Point-of-care ultrasound may be useful for detecting pediatric intussusception at an early stage. BMC Pediatr. 2020;20(1):155. doi:10.1186/s12887-020-02060-6. PMID: 32284038.
  5. Bergmann KR, Arroyo AC, Tessaro MO et al; P2Network. Diagnostic Accuracy of Point-of-Care Ultrasound for Intussusception: A Multicenter, Noninferiority Study of Paired Diagnostic Tests. Ann Emerg Med. 2021;78(5):606-615. doi:10.1016/j.annemergmed.2021.04.033. PMID: 34226072.
  6. Tonson la Tour A, Desjardins MP, Gravel J. Evaluation of bedside sonography performed by emergency physicians to detect intussusception in children in the emergency department. Acad Emerg Med. 2021;28(8):866-872. doi:10.1111/acem.14226. PMID: 33548161.
  7. Lin-Martore M, Firnberg MT, Kohn MA, Kornblith AE, Gottlieb M. Diagnostic accuracy of point-of-care ultrasonography for intussusception in children: A systematic review and meta-analysis. Am J Emerg Med. 2022;58:255-264. doi:10.1016/j.ajem.2022.06.025. PMID: 35749802.
  8. Rahmani E, Amani-Beni R, Hekmatnia Y et al. Diagnostic Accuracy of Ultrasonography for Detection of Intussusception in Children; a Systematic Review and Meta-Analysis. Arch Acad Emerg Med. 2023;11(1):e24. doi:10.22037/aaem.v11i1.1914. PMID: 36919137.
  9. Alsabri M, Rath S, Elkarargy MA et al. Accuracy of ultrasound for intussusception in pediatric emergency presentations: a systematic review and diagnostic meta-analysis. Int J Emerg Med. 2026;19(1):41. doi:10.1186/s12245-026-01134-z. PMID: 41667954.
  10. Kim JH, Lee JY, Kwon JH, Cho HR, Lee JS, Ryu JM. Point-of-Care Ultrasound Could Streamline the Emergency Department Workflow of Clinically Nonspecific Intussusception. Pediatr Emerg Care. 2020;36(2):e90-e95. doi:10.1097/PEC.0000000000001283. PMID: 28926507.
  11. Katz-Dana H, Harel-Sterling M, Vincent D, Dana E, Navarro OM, McLean LJ. A POCUS-first pathway to streamline care for children with suspected ileocolic intussusception. CJEM. 2024;26(4):235-243. doi:10.1007/s43678-024-00673-9. PMID: 38538954.
  12. Wiersma F, Allema JH, Holscher HC. Ileoileal intussusception in children: ultrasonographic differentiation from ileocolic intussusception. Pediatr Radiol. 2006;36(11):1177-1181. doi:10.1007/s00247-006-0311-2. PMID: 17019589.
  13. Park BL, Rabiner JE, Tsung JW. Point-of-care ultrasound diagnosis of small bowel-small bowel vs ileocolic intussusception. Am J Emerg Med. 2019;37(9):1746-1750. doi:10.1016/j.ajem.2019.06.024. PMID: 31257125.
  14. Goel I, Anand R, Choudhury SR, Agarwal S. Evolving Concepts in Ultrasonography of Pediatric Intussusceptions: Unequivocal Differentiation of Ileocolic, Obstructive and Transient Small-Bowel Intussusceptions. Ultrasound Med Biol. 2020;46(3):589-597. doi:10.1016/j.ultrasmedbio.2019.12.011. PMID: 31924421.
  15. Lioubashevsky N, Hiller N, Rozovsky K, Segev L, Simanovsky N. Ileocolic versus small-bowel intussusception in children: can US enable reliable differentiation? Radiology. 2013;269(1):266-271. doi:10.1148/radiol.13122639. PMID: 23801771.
  16. Zhang M, Zhou X, Hu Q, Jin L. Accurately distinguishing pediatric ileocolic intussusception from small-bowel intussusception using ultrasonography. J Pediatr Surg. 2021;56(4):721-726. doi:10.1016/j.jpedsurg.2020.06.014. PMID: 32682542.
  17. Wang Q, Luo M, Xie X, Wu Y, Xiang B. Can intussusceptions of small bowel and colon be transient? A prospective study. Eur J Pediatr. 2019;178(10):1537-1544. doi:10.1007/s00431-019-03455-z. PMID: 31446463.
  18. Subramaniam S, Chen AE, Khwaja A, Rempell R. Point-of-care ultrasound for differentiating ileocolic from small bowel-small bowel intussusception. J Emerg Med. 2022;62(1):72-82. doi:10.1016/j.jemermed.2021.07.002. PMID: 34521545.
  19. Zymerman SA, Cramer N, Klein A, Cohen S, Nadir E, Katzir Y. Point-of-care ultrasound-guided hydrostatic reduction of ileocolic intussusception in the pediatric emergency department. Ann Emerg Med. Published online July 2, 2026. doi:10.1016/j.annemergmed.2026.06.006. PMID: 42390396.
  20. Atia N, Koppel JH, Brutman-Barazani T, Soudack M, Feldman O. Bedside Intussusception Diagnosis and Reduction: A Comprehensive Emergency Department Process for Bedside Intussusception Diagnosis and Reduction. J Am Coll Emerg Physicians Open. 2026;7(3):100360. doi:10.1016/j.acepjo.2026.100360. PMID: 42267092.

Case Resolution

You place a linear, high-frequency probe on the right side of the patient’s abdomen. You perform a bedside ultrasound scan, viewing transversely and longitudinally through the upper and lower abdomen. You observe the following:

What is the diagnosis?

This is an intussusception!

The intussusceptum (red) is the part of the bowel that has telescoped into the intussuscipiens (blue). When ileum becomes trapped in the colon, this can lead to ischemia and necrosis over time. This is what causes the classic “currant jelly stools”, which are bloody stools.

Tip: The classic triad of colicky abdominal pain, palpable mass and bloody stool are present in less than 50% of patients, and intussusception should be suspected for patients with vomiting, abdominal pain, and/or lethargy.​1​

Hospital course

Johnny underwent an air enema reduction in the Radiology department, which successfully reduced the ileocolic intussusception.

Reference

  1. Daneman A, Alton D. Intussusception. Issues and controversies related to diagnosis and reduction. Radiol Clin North Am. 1996;34(4):743-756. PMID 8677307.

The PEM POCUS series was created by the UCSF Division of Pediatric Emergency Medicine to help advance pediatric care by the thoughtful use of bedside ultrasonography.

Learn more about bedside ultrasonography on the ALiEM Ultrasound for the Win series

By |2026-10-27T10:08:37-07:00May 10, 2021|Gastrointestinal, PEM POCUS, Ultrasound|
Go to Top