Peeing into the wind? Urine drug screens, part 2 (opiates)

Apart from benzodiazepines, the opiate urine drug screens (UDS) are probably the most frequently utilized and misunderstood.



 A 50 y/o man with a history of CHF and COPD is brought in by ambulance in severe respiratory distress. He is sitting upright with a RR 30 and O2 saturation of 79% on room air. Is this a CHF or COPD exacerbation? This is a common dilemma faced in the ED. Fortunately there are likelihood ratios to help you risk stratify using a Fagan nomogram.
Note that there are 3 tables:
See the blue font for the likelihood ratios ≥ 3.0.
Adapted from [1, 2]
Go to ALiEM (PV) Cards for more resources.
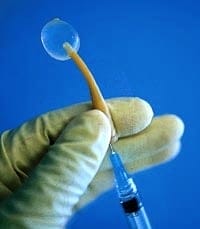 Bartholin abscesses are challenging to manage, partly because of Word catheter insertion. Sometimes, the space is not large enough (unable to fit the catheter) or too large (catheter falls out). How else can you “pack” the abscess space?
Let’s be honest. When was the last time results from urine drug screens (UDS) changed your management plan? Many times it takes hours for the patient to give the urine sample anyway. And, with all of the false positives out there, how do we know what the heck the result is actually telling us?
Do you order blood cultures for all your ED patients with a fever? Obviously no. What’s your decision making process on ordering this test? There are really no findings or tests with high specificity (rules-IN bacteremia), except interestingly “shaking chills”. Notice almost all the criteria listed below approach a likelihood ratio (LR) of 1.0. Two prediction rules do exist, however, to help you virtually rule-OUT bacteremia:
The list of LRs also will be helpful to show learners in the ED that an isolated serum WBC number is useless risk-stratifier.
A 55 y/o man with a PMH of hypertension presents with a community-acquired pneumonia on CXR, no fevers, no chills, no vomiting.
What is the patient’s pre-test and post-test probability for having bacteremia? Use these helpful stats from the Rational Clinical Examination series from JAMA.
Adapted from [1]
Go to ALiEM (PV) Cards for more resources.
This discussion doesn’t address WHETHER we should get blood cultures despite a risk for bacteremia in the setting of uncomplicated pneumonia receiving IV antibiotics or pyelonephritis with a pending urine culture.

I find it amazing that I know more non-emergency physicians virtually in the social media world rather than in person. Primarily through Twitter, I follow and am followed by medical educators from various specialties. If you haven’t joined Twitter yet, I think it might be time. There is a whole world of collaboration and conversation going on in this virtual community, which crosses specialties and geography.
Last week, Dr. Javier Benítez (@jvrbntz) was tweeting a Question of the Day, referencing a 2010 Paucis Verbis card on overanticoagulation, which was based on the 2008 American College of Chest Physicians (ACCP) guidelines. About 8 minutes after I retweeted his question, Dr. Roy Arnold (@cholerajoe), a pulmonary/critical care physician kindly informed me that the 2012 ACCP guidelines have been out since February.
So this PV card is replacing the 2010 card with revised recommendations. For more in-depth discussion, definitely take a look at Dr. Scott Weingart’s great podcast over at EMCrit. He helps to clarify holes which the 2012 ACCP guidelines don’t really address such as:
What if the patient is minorly bleeding with a high INR?
What if you only have the 3-factor PCC (factors II, IX, X) and not the recommended 4-factor PCC (factors II, IX, X plus factor VII)?
Adapted from [1]
Go to ALiEM (PV) Cards for more resources.
 To give or not to give a cephalosporin in penicillin-allergic patients?
I remember back to my days in pharmacy school when I learned that there was approximately a 10% risk of cross-reactivity, if a cephalosporin was given to a penicillin-allergic patient. They probably said something about the risk being less with 3rd and 4th generations cephalosporins, but lets be honest… who remembers anything but that magic 10%? When I started working more with physicians, I found that they also learned the same 10% rule in medical school. Well, I guess that means it’s fact, right? Not so fast!