ACMT Toxicology Visual Pearl – Sauté Gone Sour

Ingestion of the pictured mushroom is most associated with which toxicity?
- Disulfiram-like reaction
- Hallucinations
- Liver failure
- Seizures
[Image credit to William Morris via Creative Commons]
(more…)



Ingestion of the pictured mushroom is most associated with which toxicity?
[Image credit to William Morris via Creative Commons]
(more…)

For years, clinicians and researchers have debated a fundamental question in pediatric emergency care: does the type of fluid used in pediatric sepsis resuscitation matter?
The PRoMPT BOLUS trial was designed to answer this question. Conducted across 47 international sites in 5 countries and enrolling more than 9,000 children, this large, pragmatic randomized trial compared 0.9% saline with balanced crystalloids in children treated for suspected septic shock.
The results have just been released. Across a wide range of clinically meaningful outcomes (including kidney injury, mortality, and recovery), there was no difference between fluid types.
Sepsis remains a major global health concern, affecting approximately 50 million people each year, with children accounting for nearly half of these cases. Early fluid resuscitation is a cornerstone of treatment, making the choice of fluid a critical and historically debated decision.
Two primary types of crystalloid fluids are used in practice:
Prior research raised concerns that saline could contribute to metabolic acidosis and kidney injury, while balanced fluids were associated with improved outcomes in some adult and smaller pediatric studies. However, the pediatric literature remained inconsistent, with observational studies reaching conflicting conclusions. As a result, guidelines offered only weak recommendations favoring balanced fluids and called for more definitive trials.
PRoMPT BOLUS was designed to fill this gap.
This trial used a pragmatic, randomized design (NS vs. balanced fluids), intentionally embedded into routine clinical care. Pragmatic trials evaluate clinical interventions within typical practice, rather than highly controlled clinical settings. By incorporating fluid randomization without modifying additional aspects of clinical practice, this approach allowed investigators to study fluid choice in real-world conditions across diverse healthcare systems. PRoMPT BOLUS was a collaborative effort across multiple networks including PECARN (Pediatric Emergency Care Applied Research Network), PERC (Pediatric Emergency Research Canada), and PREDICT (Paediatric Research in Emergency Departments International Collaborative).
Children ages 2 months to <18 years were eligible if clinicians suspected sepsis and were planning to treat with more than one fluid bolus for abnormal perfusion consistent with septic shock. They were randomized to receive either balanced fluids or 0.9% saline, with clinicians otherwise managing care as they normally would.
The primary outcome was MAKE30 (Major Adverse Kidney Events within 30 days), a composite that includes mortality, need for renal replacement therapy, or persistent kidney dysfunction at hospital discharge or 30 days, whichever came first.
This pragmatic approach was critical to the study’s success. It allowed for:
The primary outcome, MAKE30, occurred at nearly identical rates in both groups:
This difference was neither statistically nor clinically significant. There were also no differences in any of the individual MAKE30 components between treatment groups.
Similarly, there were no meaningful differences in:
Together, these findings strongly support the conclusion that both fluids are equally safe and effective.
Although there were measurable and statistically significant biochemical differences between groups (such as higher rates of hyperchloremia and hypernatremia with saline and hyperlactatemia with balanced fluids), these changes did not translate into clinically meaningful outcomes.
Subgroup analyses across patient characteristics, illness severity, and total fluid volume showed no differences in outcomes. While there was a non-significant trend suggesting potential benefit of balanced fluids in the most severely ill patients, the study was not powered to confirm this finding.
The results of PRoMPT BOLUS can be distilled into several key conclusions:
Importantly, while the study cannot fully exclude a benefit of balanced fluids in the sickest patients, it provides strong evidence that for children presenting to the ED with suspected sepsis, either fluid is an appropriate choice.
These findings have immediate and meaningful implications for clinical practice.
First, they simplify decision-making. Clinicians can focus on timely recognition and treatment of children with suspected sepsis, and engage in fluid resuscitation with fluids that make sense for the clinical scenario.
Second, the results support flexibility in care. Fluid choice can now be guided by:
While the study is robust, several limitations should be considered.
The overall incidence of MAKE30 was lower than expected (~3% vs. an anticipated ~6%), which may reflect a less severely ill population than initially projected. This could limit the ability to detect small differences between groups.
Additionally, although subgroup analyses suggested a possible benefit of balanced fluids in more severely ill patients, the study was not powered to draw definitive conclusions in this population.
The PRoMPT BOLUS trial provides the strongest evidence to date addressing fluid choice in children presenting to the ED with suspected sepsis. Both 0.9% saline and balanced crystalloids are safe and effective for resuscitation in children with suspected septic shock.
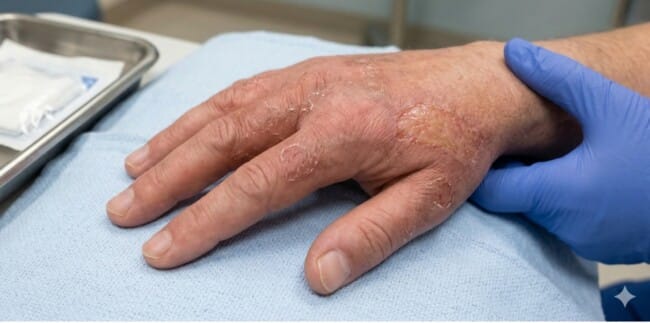
What type of burn may not develop findings shown until days to weeks after the exposure?
[Image generated via Google Gemini]

Welcome to the AIR Non-ACS Cardiology Module! After carefully reviewing all relevant posts in the past 12 months from the top 50 sites of the Digital Impact Factor [1], the ALiEM AIR Team is proud to present the highest quality online content related to non-ACS cardiology emergencies in the Emergency Department. 9 blog posts met our standard of online excellence and were approved for residency training by the AIR Series Board. More specifically, we identified 6 AIR and 3 Honorable Mentions. We recommend programs give 5 hours of III credit for this module.
In an effort to truly emphasize the highest quality posts, we have 2 subsets of recommended resources. The AIR stamp of approval is awarded only to posts scoring above a strict scoring cut-off of ≥30 points (out of 35 total), based on our scoring instrument. The other subset is for “Honorable Mention” posts. These posts have been flagged by and agreed upon by AIR Board members as worthwhile, accurate, unbiased, and appropriately referenced despite an average score.
Want asynchronous Individualized Interactive Instruction (III) credit?
Take the AIR quiz at ALiEMU. Free, 1-time login required.
| Site | Article | Author | Date | Label |
|---|---|---|---|---|
| EMCrit | Supraventricular Tachycardia | Dr. Josh Farkas | January 5, 2025 | AIR |
| EMCrit | Right Ventricular Failure | Dr. Josh Farkas | March 21, 2025 | AIR |
| EMCrit | Valvular Heart Disease | Dr. Josh Farkas | January 27, 2025 | AIR |
| EMCrit | Antiarrhythmics | Dr. Josh Farkas | January 8, 2025 | AIR |
| EM Cases | Acute heart failure risk stratification and disposition | Dr. Anton Helman | August 19, 2025 | AIR |
| EMCrit | SCAPE (sympathetic crashing acute pulmonary edema) | Dr. Josh Farkas | January 30, 2025 | AIR |
| RCEMlearning | Cardiogenic Pulmonary Oedema | Dr. Victoria Henson | May 30, 2025 | HM |
| EMCrit | Acute Pericarditis | Dr. Josh Farkas | September 20, 2025 | HM |
| EMCrit | Acute Myocarditis and evaluation of newly discovered HFrEF | Dr. Josh Farkas | October 1, 2024 | HM |
(AIR = Approved Instructional Resource; HM = Honorable Mention)
If you have any questions or comments on the AIR series, or this AIR module, please contact us!

What is the spider pictured below?
[Author’s own image]

What toxic gas is created by mixing these two household products?
[Author’s own image]

A 14-year-old Hispanic girl presents to the Emergency Department with her mother for suicidal ideation after a conflict at home. The girl is quiet and cooperative. Her mother, who speaks primarily Spanish, is trying to explain the situation. The nurse assigns an ESI level 2, the same score given to nearly every child who walks through the door with a behavioral health complaint. But does that score accurately capture this patient’s needs?
A new multicenter PECARN study published this week in JAMA Network Open takes a close look at triage accuracy for pediatric behavioral health ED visits. The findings: mistriaging errors are common, and they are not equally distributed [1].
Hoffmann et al. analyzed 78,411 ED visits by children aged 5 to 17 with behavioral health chief concerns across 15 PECARN Registry EDs from 2021 to 2023 [1]. They classified each visit as appropriately triaged, overtriaged, or undertriaged using vital signs, Glasgow Coma Scale, pain scores, emergency medication use, resource utilization, and disposition. Of the 74,564 visits with complete data:
The Emergency Severity Index (ESI) is used in over 90% of US EDs [2]. It sorts patients into 5 acuity levels. Level 1 is for patients needing lifesaving interventions. Level 2 is for high-risk situations, confused patients, or those in severe pain. Levels 3 through 5 are based on anticipated resource needs. In this study, 83.5% of all behavioral health visits were triaged as ESI level 2.
To assess triage accuracy, the authors compared each child’s assigned ESI level against what actually happened during their visit.
Overtriage means a child was assigned a higher acuity score than their clinical course supported. For a child assigned ESI level 2, overtriage was defined as meeting ALL of the following [1]:
In other words, the triage nurse predicted high acuity, but the visit didn’t bear that out.
Undertriage means the opposite: a child was assigned a lower acuity score than their clinical course warranted. For example, a child triaged as ESI level 4 (expected to need 1 resource) who ended up being admitted, needing emergency medications, or using multiple resources. The triage nurse underestimated how sick the child was or how much care they would need.
The most concerning equity finding was in undertriage.
After adjusting for clinical and visit characteristics, undertriage was significantly more likely for Hispanic children (AOR 1.46), non-Hispanic Black children (AOR 1.28), and children whose families preferred Spanish (AOR 1.31), all compared to non-Hispanic White and English-speaking patients [1]. The authors point to implicit clinician bias, systemic racism, and underutilization of professional interpreters as likely contributors.
The safety implications are real. Children whose acuity is underestimated may face longer waits, miss time-sensitive interventions, or leave the ED without being seen despite elevated risk.
More than half of all visits (57%) were overtriaged [1]. These children received a higher acuity triage score than their clinical course supported.
The strongest predictor was age. Children aged 5-9 had over 4-fold higher adjusted odds of overtriage compared to those aged 10-14 (AOR 4.43), possibly because younger children have a limited ability to communicate their symptoms and needs.
To a lesser degree, non-Hispanic Black children also had higher adjusted odds of overtriage compared to non-Hispanic White children (AOR 1.17). The authors cite research on adultification, the tendency to perceive Black youth as older or more threatening than they are, as a potential contributor. This means Black children in this study were more likely to be both undertriaged and overtriaged compared to White children. The errors are not unidirectional. They likely reflect different biases operating at different points in care.