ACMT Toxicology Visual Pearl – Master of Deceit

What venomous marine animal is pictured?
- Fire coral
- Lionfish
- Sea urchin
- Stonefish
[Image from Rapheal Duprat via Wikimedia]



What venomous marine animal is pictured?
[Image from Rapheal Duprat via Wikimedia]
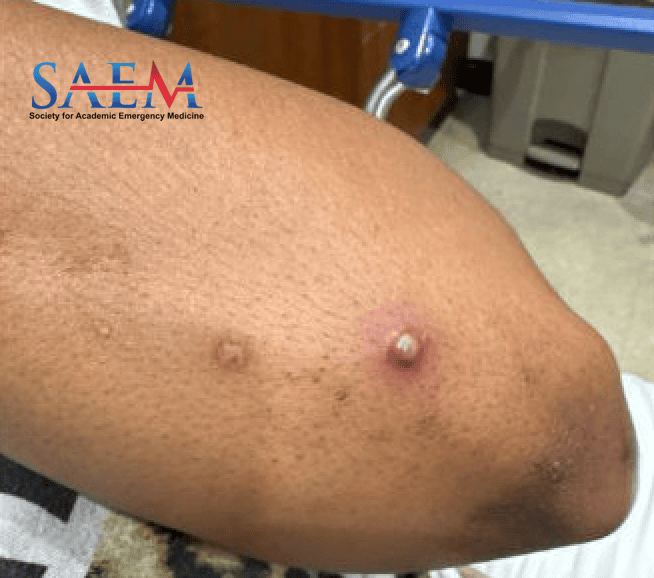
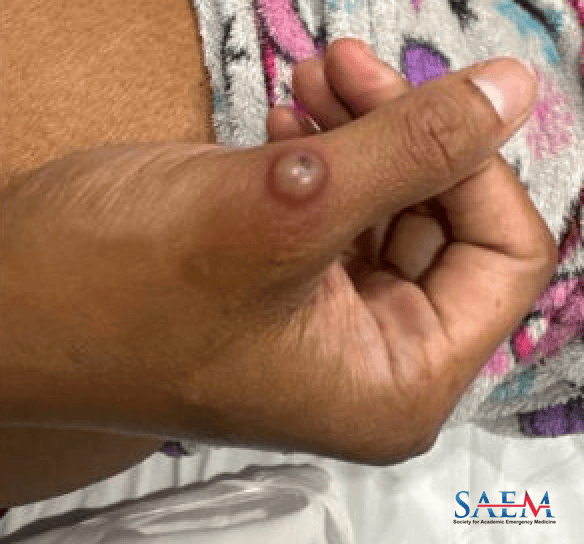
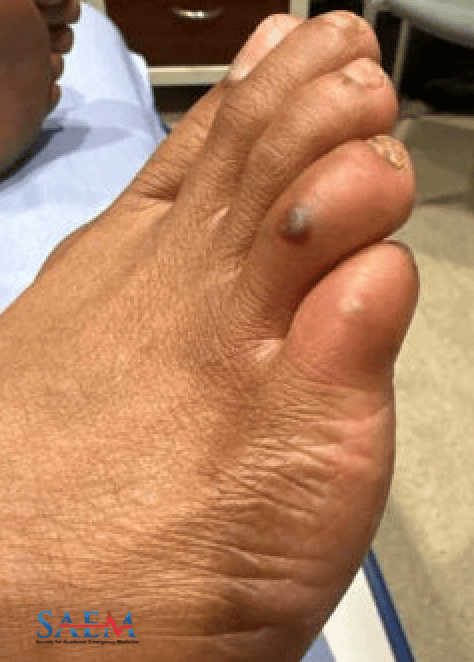
The patient is a 39-year-old female with past medical history of polysubstance use disorder and seizures who presents to the Emergency Department complaining of bilateral leg pain, primarily in her joints. She states that she was seen by her PCP today and was given a shot of Toradol, but she reports that her pain has continued to worsen to the point that she has difficulty ambulating. She states that two days ago she developed pruritic blisters on her feet and her feet began to swell. She reports the blisters have worsened and have spread to her hands and forearms as well as her calves and thighs. She denies ever having similar symptoms in the past. She reports some subjective fevers and chills as well as cough and congestion, but denies sore throat, chest pain, abdominal pain, vomiting, diarrhea, dysuria, vaginal bleeding, or vaginal discharge. She denies any recent travel and denies any animal exposure other than her mother’s dog but there are no fleas that she knows of. She denies any recent insect bites. She states that she has been sexually active with one male partner over the last six months and that she has tested negative for STIs in the last two months. She has no other complaints at this time.
Vitals: BP 121/77; HR 107; R 22; T 100.8°F; O2 sat 98% room air.
General: Appears mildly uncomfortable but no acute distress.
HEENT: Normal, no signs of pharyngitis.
Respiratory: Clear to auscultation bilaterally.
Cardiovascular: Tachycardia without murmur.
Abdomen: Non-tender, no masses.
Extremities: There are no signs of trauma. Full range of motion but complaints of joint pain with moving her legs and with walking.
Skin: Relevant findings as shown. Discrete, tender, erythematous macules and vesicles on the bilateral feet, calves, forearms and a singular vesicle of the right1st digit
Urinalysis: Small amount of bacteria
This patient has disseminated gonococcal infection.
Disseminated gonococcal infection (DGI) is a serious complication of untreated gonorrhea, potentially leading to severe complications such as septic arthritis, pustular skin lesions, tenosynovitis, and in rare cases, endocarditis or meningitis. DGI is characterized by fevers, polyarticular joint pain, and skin lesions. The diagnosis of disseminated gonorrhea should be considered in any patient presenting with polyarticular joint pain or swelling in the setting of petechial or pustular skin lesions, especially in high risk populations. The skin lesions of disseminated gonorrhea most commonly appear on the distal extremities, and may involve the palms and soles. Patients may also present with acute septic arthritis without an obvious source. Patients with gonoccocal bacteremia may show signs of perihepatitis, meningitis, endocarditis, or osteomyelitis. Disseminated gonococcal infection results from the hematogenous spread of N gonorrhoeae, and typically develops within 3 weeks of primary mucosal infection. Patients with disseminated gonoccocal infection should be admitted for intravenous antibiotics (ceftriaxone). Any sexual partners should be treated as well.
Consider disseminated gonorrhea when you have a patient with polyarticular joint pain/swelling with pustular skin lesions.
Complications of DGI may be severe; admission and aggressive treatment with intravenous antibiotics is warranted.
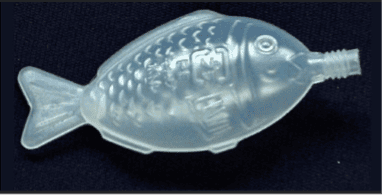
What recreationally used substance has been dispensed in this fish-shaped dropper?
[Author’s own image]
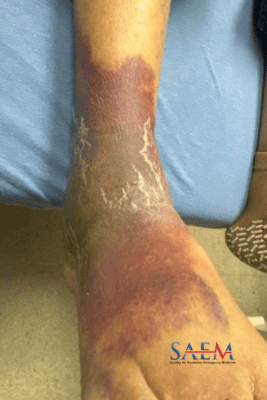
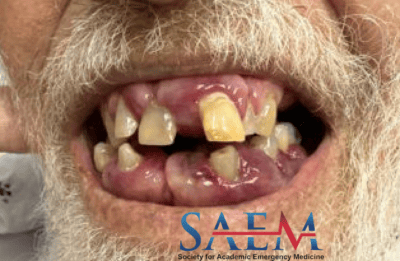
The patient is a 72-year-old male with multiple medical problems who presents to the Emergency Department complaining of dyspnea on exertion. The patient also complains of bruising that has developed on his right leg. He states that he previously had a similar episode for which she was admitted to the hospital and had warfarin discontinued due to thrombocytopenia. He also reports that he has been unable to eat or drink much lately due to gum swelling and tenderness, and states that when he begins chewing he feels as though his teeth are going to fall out. When asked about his usual diet, the patient states that he primarily eats raisin bran crunch and grits and that he does not really eat fruits or vegetables. He denies any chest pain, abdominal pain, nausea, vomiting, diarrhea, bloody stools, or any other complaints.
Vitals: All vital signs are normal.
General: Pleasantly interactive in no acute distress.
HEENT: Key findings are shown in the image provided.
Respiratory: Clear to auscultation, no increased work of breathing.
Extremities/Skin: Diffuse ecchymosis and petechiae are present. Bruising to the right foot and ankle as shown. Bilateral legs with significant petechiae diffusely. Hair as shown.
CBC: WBC 10.4 Hgb 7.8 Plt 98,000
RBC Morphology abnormal- Moderate Anisocytosis, Slight Poikilocytes
Moderate Polychromasia, Slight Elliptocytes, Slight Hyopchromia
CMP: Albumin 2.5, Total Protein 5.4
This patient has scurvy.
Vitamin C deficiency
Scurvy results in multiple symptoms including gingivitis with bleeding, periodontal disease, loss of dentition, mucocutaneous petechiae, ecchymosis, hyperkeratosis, and corkscrew hairs. Scurvy is due to Vitamin C deficiency and resultant impaired collagen biosynthesis. Petechiae, ecchymosis, follicular hyperkeratosis, perifollicular hemorrhages, corkscrew hairs, gingival bleeding, arthralgias, skin discoloration, impaired wound healing, koilonychias, and splinter hemorrhages may all be seen in patients with scurvy. These findings are primarily derived from inability to synthesize collagen due to lack of ascorbic acid, which is used as an electron donor to catalyze proline and lysine into hydroxyproline and hydroxylysine. Ascorbic acid also prevents epigenetic DNA hypermethylation, which is essential in the synthesis of certain collagen types.
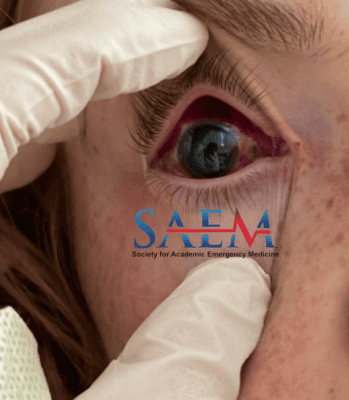
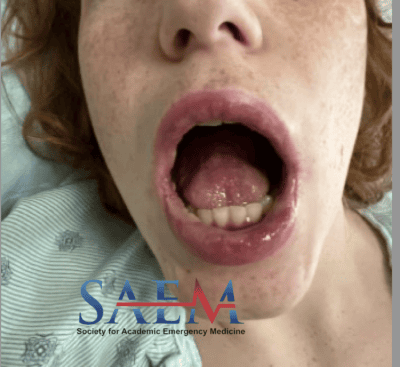
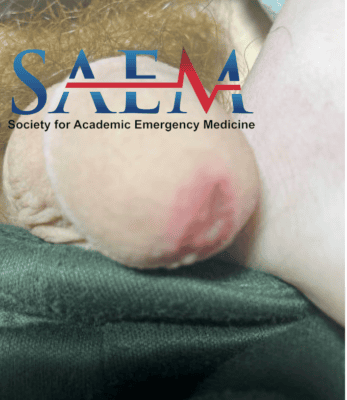
The patient is a healthy 14-year-old male without past medical history who presents to the Emergency Department with oral lesions, eye swelling, intermittent fevers, and pain with urination. Over the past 10 days he has been seen by his PCP and at an outside ED for a cough, sore throat, fevers, and oral pain. Three days ago he was seen by his PCP, had a positive rapid strep test, and was started on amoxicillin. His oral lesions and lip swelling have been progressively worsening over the past 2 days. Monospot testing was also performed yesterday and is negative. Today he was seen again by his PCP for new pain with urination and was sent to the ED for concern for Kawasaki disease. The patient has had decreased oral intact due to his pain, but otherwise has no other complaints.
Vitals: BP 124/88 HR 112 R 28 T 100.2 F O2sat 94% room air.
HEENT: Relevant findings are shown in the images provided. Tonsillar exudate is present. No meningismus. Voice is normal.
Respiratory: Coarse breath sounds with diffuse wheezing.
Cardiovascular: Tachycardic, no murmurs, no rubs.
Skin: No rash. Negative Nikolsky sign. No palmar desquamation.
Lymph: Cervical lymphadenopathy is present
Genitourinary: See image provided.
CBC, CMP, Urinalysis: negative
COVID/Flu/RSV: negative
Mycoplasma NAAT: positive.
CRP: 13.5 mg/L
ESR: 48 mm/Hr
This child has RIME (reactive infections mucocutaneous eruption), a rare post-infectious cause of mucositis in children and adolescents.
Mycoplasma pneumoniae
Prolonged fevers and illnesses are frequent reasons for pediatric ED visits. Children and adolescents can be more prone than adults to a variety of immune-mediated and other inflammatory reactions such as Kawasaki disease, serum sickness like reactions, erythema or urticaria multiforme, SJS/TEN, MISC, among others. RIME is a relatively recently described post-infectious condition characterized by mucositis in at least two mucus membranes, with or without an area of cutaneous eruption. It was previously called mycoplasma-induced rash and mucositis (MIRM), and mycoplasma is the most common trigger, though the designation RIME implies that other common infectious agents (covid, influenza, and other viral and bacterial pathogens) have been identified as causal agents. Management is supportive, including treatment of the underlying illness (in this case, treatment of mycoplasma). Corticosteroids and other immunomodulatory agents may be used in more severe cases.
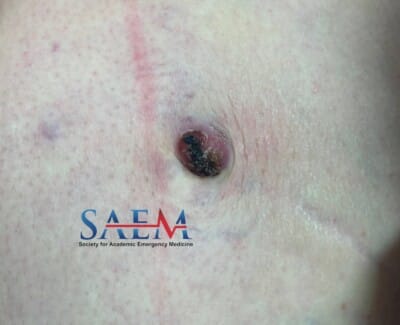
The patient is a 70-year-old female with a remote history of breast cancer who presents to the Emergency Department with family due to frequent falls and disorientation. Her family reports that she previously walked independently. However, over the last several months, she has had worsening weakness and has become wheelchair-bound. Nonetheless, she frequently attempts to walk and loses her balance, leading her to falling. She is brought in today due to another fall along with worsening confusion over the past few weeks. The family does not believe the patient suffered any significant injury today, but brings here in due to her worsening condition. The patient has no complaints at this time.
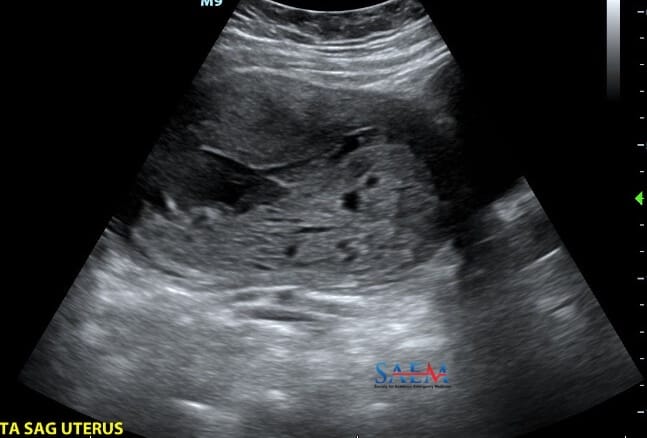
The patient is a 40-year-old female who presents to the Emergency Department with bilateral leg swelling. Her symptoms started six days prior and have progressively worsened. Her symptoms are associated with shortness of breath with no chest pain. The patient has taken an over-the-counter diuretic, which has helped with her symptoms. She also reports intermittent vaginal bleeding for the past two months, with a LMP that was two months prior. She is not currently on contraceptives, and does endorse unprotected intercourse over this time. The patient denies headache, blurry vision, nausea or vomiting, abdominal pain, urinary complaints, diarrhea or constipation. She has no other complaints at this time.
Vitals: BP 140/86; HR 97; R 14; T 99°F; O2 sat 99% on room air.
General: Well appearing, no acute distress.
Respiratory: Clear to auscultation.
Cardiovascular: Regular rate and rhythm, no murmur.
Abdomen: Soft, nondistended, nontender.
Extremities: Trace bilateral pitting edema. Normal range of motion, neurovascularly intact, equal pulses bilaterally.
Neurological: No focal neurological deficits.
Hgb: 9.6 (previously 13.3 two years prior)
Creatinine: Normal
BNP: 706 pg/mL
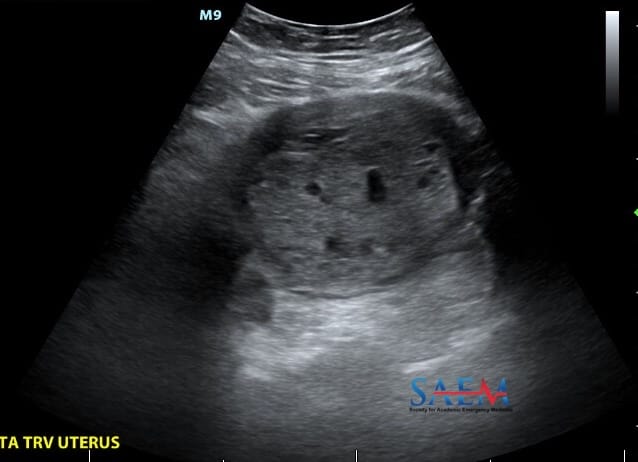
Serum ꞵ-HCG: 874,342 mIU/ml
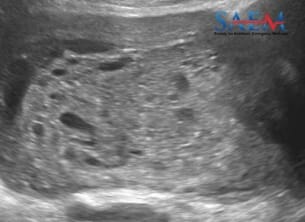
This patient has a complete molar pregnancy.
Molar pregnancy is part of a spectrum of gestational trophoblastic tumors that include benign hydatidiform moles, locally invasive moles, and choriocarcinoma. Patients classically present with painless first or early second trimester vaginal bleeding with uterine size larger than expected gestational age and excessively high β-hcg levels. Some patients develop anemia, hyperemesis gravidarum, clinical hyperthyroidism, and signs of preeclampsia including hypertension, headaches, proteinuria and edema. Acute respiratory distress can occur due to embolization of trophoblastic tissue into the pulmonary vasculature, thyrotoxicosis, or simple fluid overload. Management involves removal of molar tissue through D&C or dilation and suction evacuation. Histopathologic examination of the products of conception is the gold standard for the diagnosis of a molar pregnancy. β-hcg levels are then monitored to ensure complete resolution and to detect any signs of persistent trophoblastic disease. In some cases, adjunct chemotherapy or even hysterectomy may be needed.
Molar pregnancy can be diagnosed with excessively high β-hcg levels and an ultrasound that shows a classic “snowstorm” or “bunches of grapes” finding.
Consider gestational trophoblastic disease in any patient with signs and symptoms of preeclampsia prior to 20 weeks gestation.