Paucis Verbis card: TIMI risk score
 How do you risk-stratify undifferentiated chest pain patients in the Emergency Department? There are a multitude of causes for chest pain. We are always taught to think of the 5 big life-threats: ACS, PE, aortic dissection, tension pneumothorax, and pericardial tamponade.
So how do YOU risk-stratify your patients for unstable angina (UA) and non-ST elevation myocardial infarction (NSTEMI)? STEMI’s are usually obvious. UA and NSTEMIs — not so much.
Fortunately a 2000 JAMA article and a followup Academic Emergency Medicine 2006 study have solidified the TIMI risk scoring system as a reasonable risk-stratification tool for all-comer ED patients with chest pain requiring an ECG.
Generally there is an upslope in risk at a TIMI score of 3 and greater.
PV Card: TIMI Risk Score
Adapted from [1, 2]
Go to ALiEM (PV) Cards for more resources.
References
- Pollack C, Sites F, Shofer F, Sease K, Hollander J. Application of the TIMI risk score for unstable angina and non-ST elevation acute coronary syndrome to an unselected emergency department chest pain population. Acad Emerg Med. 2006;13(1):13-18. [PubMed]
- Antman E, Cohen M, Bernink P, et al. The TIMI risk score for unstable angina/non-ST elevation MI: A method for prognostication and therapeutic decision making. JAMA. 2000;284(7):835-842. [PubMed]

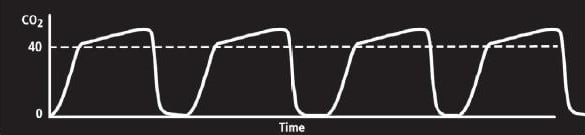 From time to time, our patients need moderated and deep sedation in order to tolerate painful procedures such as joint reductions or incision and drainage procedures. There are many medications available to us including some newer ones such as Ketofol and Dexmedetomidine.

 Have you heard of the Modified Centor Score for strep pharyngitis? Interestingly, it has been validated in adults and children. The methodology builds on the traditional Centor Score by incorporating the patient’s age, because this disease is more prevalent in kids than adults. In fact, you actually lose a scoring point if you are older than 44 years old.