SplintER Series: “Pop in the Posterior Thigh”

transverse view of the hamstring

A 20-year-old male presents with right posterior thigh pain and difficulty walking after he felt a “pop” while sprinting in a race. An ultrasound of the right posterior thigh is performed and the above image is seen on the transverse view without compression (Image 1. ST- semitendinosus; BF – bicep femoris; H – hematoma. Courtesy of Matthew Negaard, MD).


(more…)

SAEM Clinical Image Series: The Insidious Rash

rash

A 60-year-old African American female with a history of hypertension presents to the emergency department for an itchy, diffuse rash. She first noticed the lesions a few years prior, and they have progressively become larger and more inflamed. The lesions have become severely pruritic over the last couple of months. Steroid creams did not appear to improve symptoms. Currently, the lesions on her arm have become painful with yellow drainage. The patient denies nausea, vomiting, and fever.

(more…)

2020 ACLS Guidelines on Medications for Toxicology-Related Conditions

ACLS 2020 toxicology

The 2020 ACLS guidelines provide recommendations on the medication-specific management recommendations for toxicology [1]. Although the name of the guidelines emphasize they are ‘Advanced,’ these are still relatively basic toxicology recommendations and largely apply to patients in cardiac arrest or refractory shock. There are also our 2020 ACLS guideline summaries on vasopressor and non-vasopressor medications used during cardiac arrest and arrhythmia management.

Benzodiazepines

  • Flumazenil if NOT recommended in undifferentiated coma (COR3, LOE B-R)

Cocaine

  • Benzodiazepines, alpha blockers, calcium channel blockers, nitroglycerin, and/or morphine can be beneficial for hypertension, tachycardia, agitation, or chest discomfort (COR 2a, LOE B-NR)
  • Pure beta-adrenergic blockers may be reasonable to avoid, although “contradictory evidence exists (COR 2b, LOE C-LD)

Local Anesthetics

  • IV lipid emulsion may be reasonable (COR 2b, LOE C-LD)

Sodium Channel Blockers (e.g. tricyclic antidepressants)

  • Sodium bicarbonate can be beneficial for cardiac arrest or life-threatening conduction delays, such as QRS >120 msec (COR 2a, LOE C-LD)
  • Extracorporeal membrane oxygenation (ECMO) may be considered for cardiac arrest or refractory shock (COR 2b, LOE C-LD)

Digoxin

  • Antidigoxin Fab should be administered in severe toxicity (COR 2b, LOE B-R)

Carbon Monoxide

  • Hyperbaric oxygen may be helpful in severe toxicity (COR 2b, LOE B-R)

Cyanide

  • Hydroxocobalamin can be beneficial, along with oxygen +/- sodium thiosulfate (COR 2a, LOE C-LD)

Atrioventricular Nodal Blockers

Intervention Beta-adrenergic blocker Calcium channel blocker Evidence (COR/LOE)
High-dose insulin Reasonable Reasonable 2a/C-LD
Glucagon IV Reasonable May be considered 2a/C-LD and 2b/C-LD
Calcium May be considered Reasonable 2b/C-LD and 2a/C-LD
ECMO Might be considered Might be considered 2b/C-LD

Table: Medications and interventions in the management of beta-adrenergic and calcium channel blocker toxicity (COR: class of recommendation, LOE: level of evidence, ECMO: extracorporeal membrane oxygenation)

Reference

Panchal AR, Bartos JA, Cabañas JG, et al; Adult Basic and Advanced Life Support Writing Group. Part 3: Adult Basic and Advanced Life Support: 2020 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2020 Oct 20;142(16_suppl_2):S366-S468. doi: 10.1161/CIR.0000000000000916. Epub 2020 Oct 21. PMID: 33081529.

2020 ACLS Guidelines on Medications for Management of Specific Arrhythmias

ACLS 2020 arrhythmias

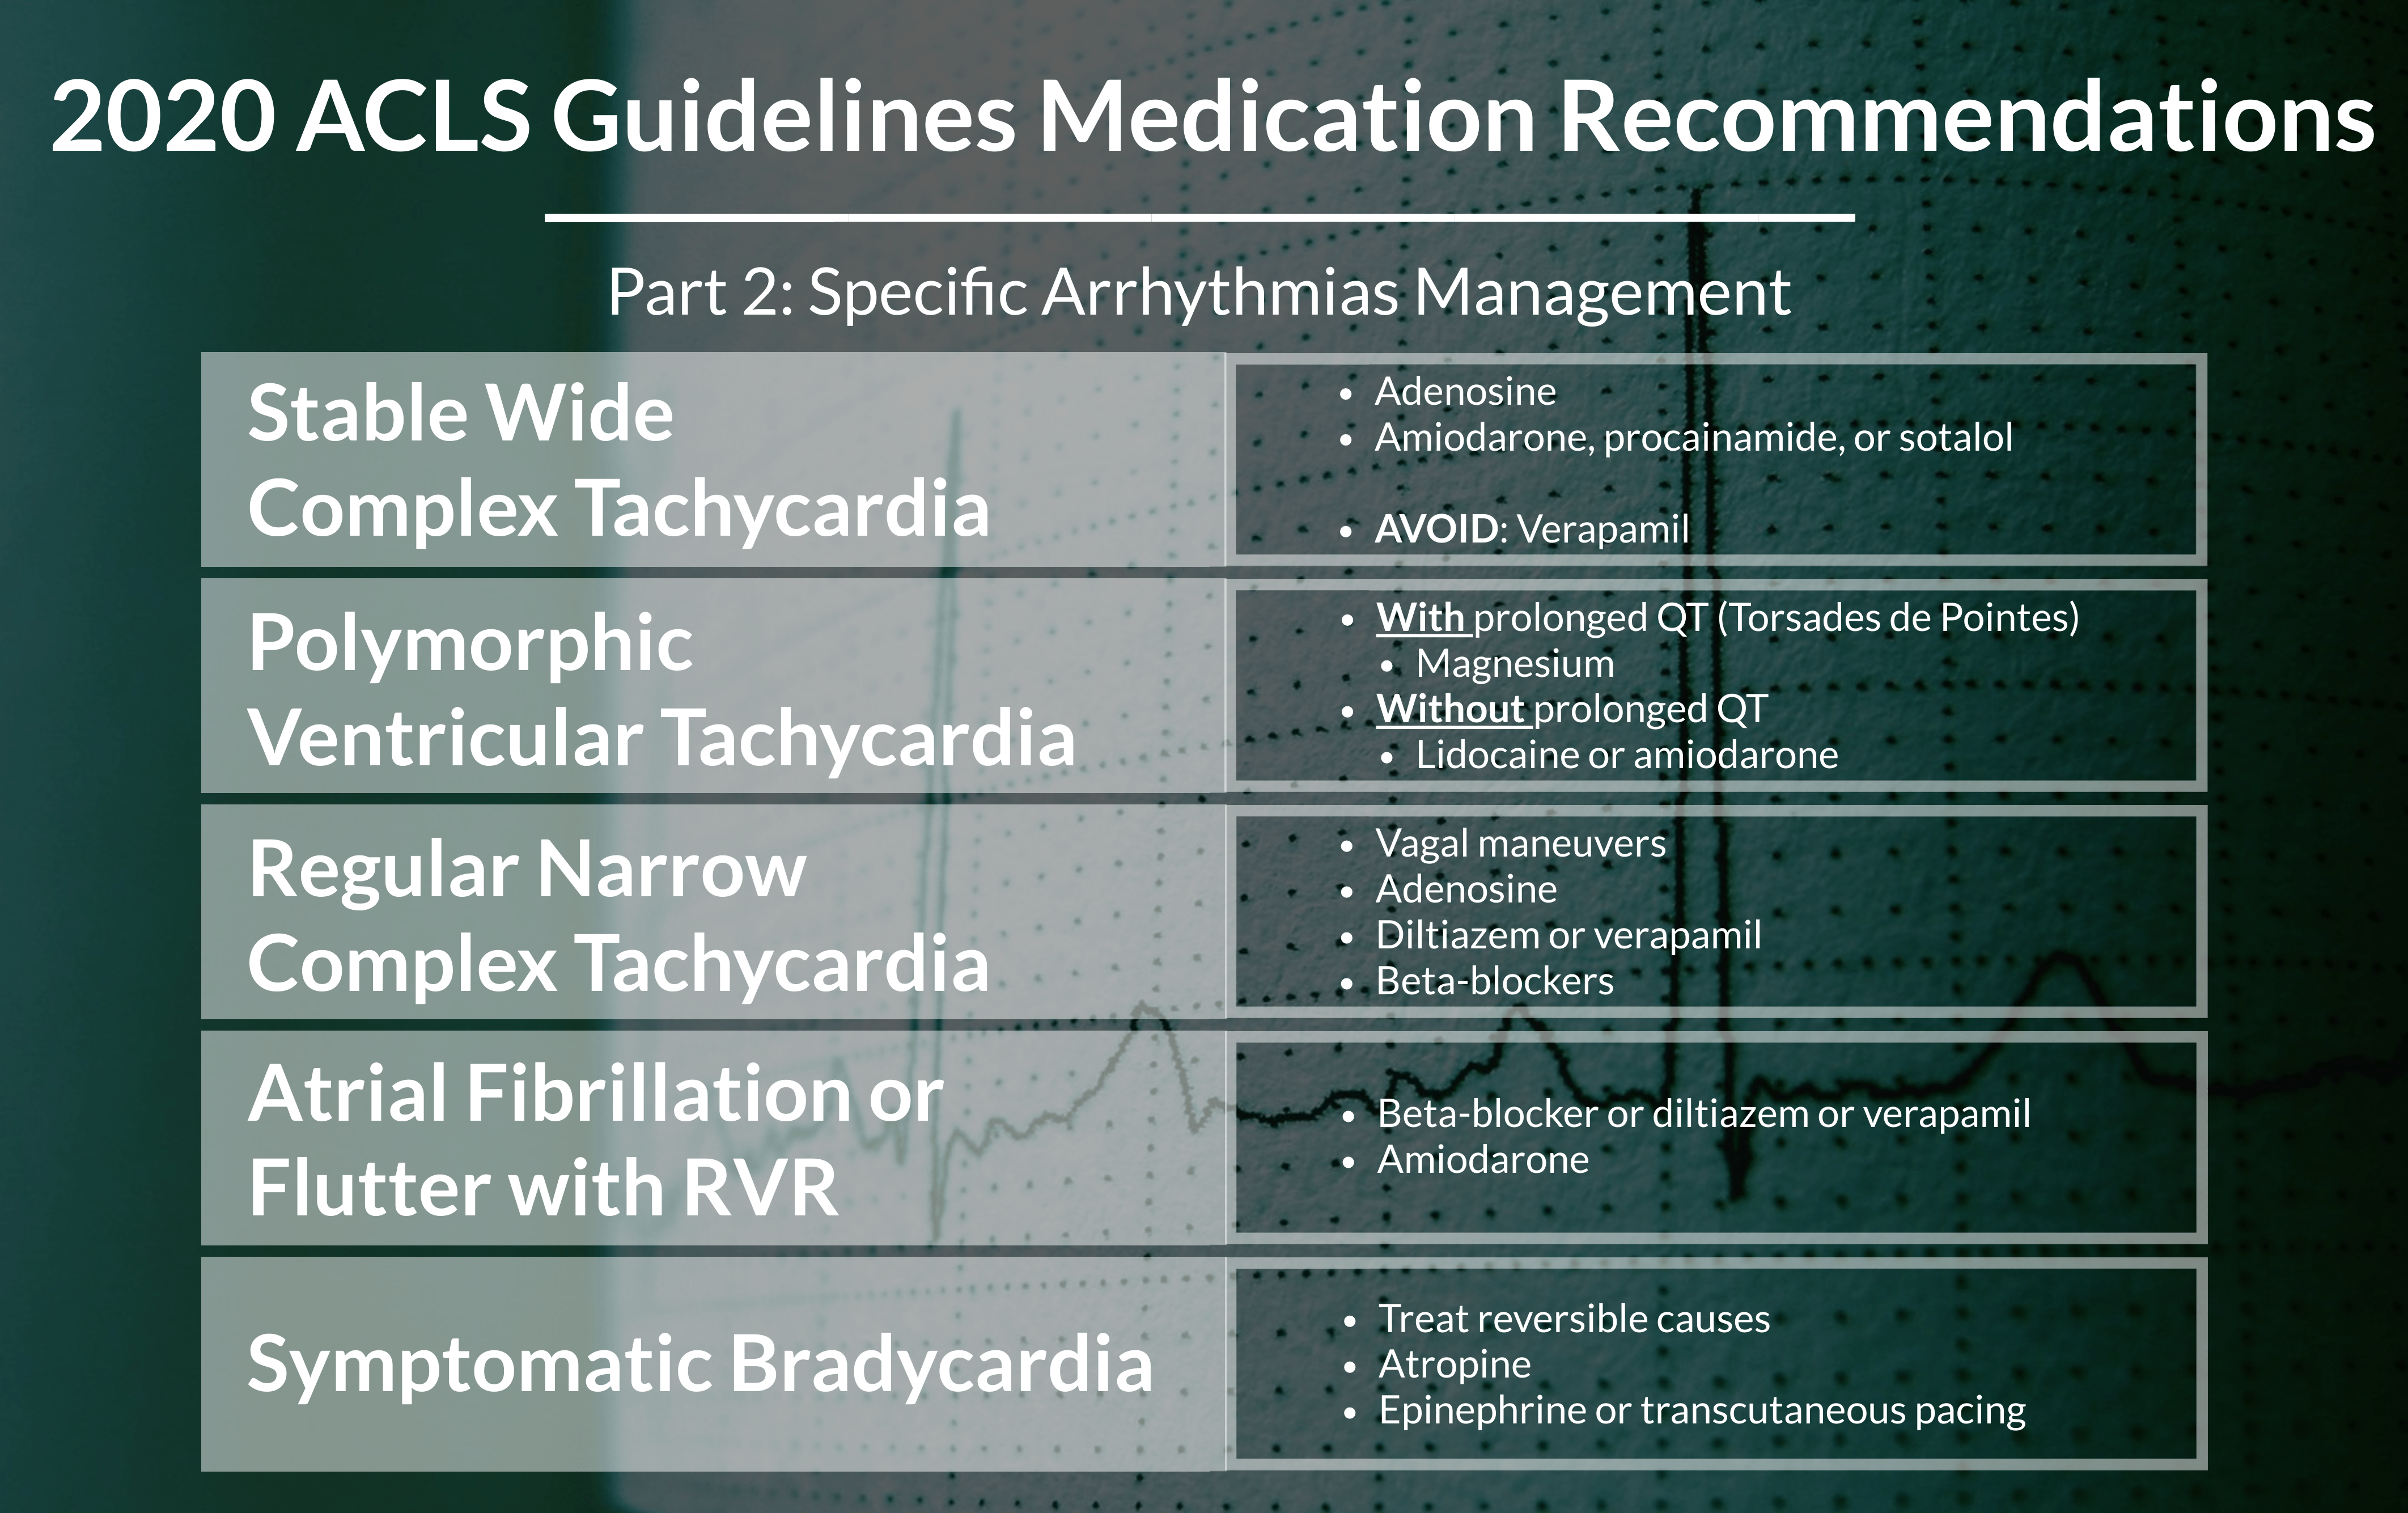
The 2020 ACLS guidelines provide recommendations on the medication-specific management for arrhythmias including wide-complex tachycardia, regular narrow-complex tachycardia, atrial fibrillation/flutter, and bradycardia [1]. There are also our 2020 ACLS guideline summaries on vasopressor and non-vasopressor medications used during cardiac arrest and toxicology-related conditions.

Wide-complex tachycardia (WCT)

Wide-complex tachycardia Medication(s) Evidence
Hemodynamically stable Adenosine COR 2b, LOE B-NR
Amiodarone, procainamide, or sotalol COR 2b, LOE B-R
NOTE: Verapamil is harmful COR 3, LOE B-NR
Polymorphic VT with long QT (torsades de points) Magnesium COR 2b, LOE C-LD
Polymorphic VT without long QT Lidocaine or amiodarone COR 2b, LOE C-LD

Regular narrow-complex tachycardia

  1. Vagal maneuvers (COR 1, LOE B-R)
  2. Adenosine (COR 1, LOE B-R)
  3. Diltiazem or verapamil (COR 2a, LOE B-R)
  4. Beta-blockers (COR 2a, LOE C-LD)

Atrial fibrillation/flutter with rapid ventricular rate

  1. Beta-blocker or diltiazem or verapamil (COR 1, LOE B-NR)
  2. Amiodarone (COR 2a, LOE B-NR)


Bradycardia

  1. Treat reversible causes (COE 1, LOE C-EO)
  2. Atropine if hemodynamic compromise (COR 2a, LOE B-NR)
  3. Epinephrine or transcutaneous pacing if unresponsive to atropine (COR 2b, LOE C-LD)

Reference

Panchal AR, Bartos JA, Cabañas JG, et al; Adult Basic and Advanced Life Support Writing Group. Part 3: Adult Basic and Advanced Life Support: 2020 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2020 Oct 20;142(16_suppl_2):S366-S468. doi: 10.1161/CIR.0000000000000916. Epub 2020 Oct 21. PMID: 33081529.

2020 ACLS Guidelines on Vasopressors and Non-Vasopressors During Cardiac Arrest

The 2020 ACLS Guidelines were published in October 2020 [1]. This first of 3 blog posts will focus on vasopressor and non-vasopressor medications during cardiac arrest. Part 2 will focus on specific arrhythmia management and Part 3 will focus on toxicologic interventions.

Summary

There were no major updates for vasopressors and non-vasopressors used during cardiac arrest. The American Heart Association (AHA) published Highlights of the 2020 Guidelines [PDF] as a clear and concise summary. Now that the AHA is releasing focused updates in the 5-year period between guidelines (like this one on lidocaine), fewer major changes likely will be needed when the full guidelines are published.


Vasopressor Non-Vasopressor

Epinephrine

  • Recommended for patients in cardiac arrest (COR 1, LOE B-R)
  • Reasonable to administer 1 mg every 3-5 minute (COR 2a, LOE B-R)
  • Reasonable to administer as soon as feasible in non-shockable rhythm (COR 2a, LOE C-LD)
  • May be reasonable to administer after initial defibrillation attempts have failed in shockable rhythm (COR 2b, LOE C-LD)

Amiodarone or lidocaine

  • May be considered for VF/pVT unresponsive to defibrillation (COR 2b, LOE B-R)


Vasopressin

  • Offers no advantage over epinephrine (COR 2b, LOE C-LD)

Steroids

  • During CPR, are of uncertain benefit in OHCA (COR 2b, LOE C-LD)
 

Calcium

  • Routine use NOT recommended (COR 3, LOE B-NR)
 

Sodium bicarbonate

  • Routine use NOT recommended (COR 3)
 

Magnesium

  • Routine use NOT recommended (LOE B-R)

Table: Vasopressors and non-vasopressors used during cardiac arrest (VF: ventricular fibrillation, pVT: pulseless ventricular tachycardia)


Reference:

Panchal AR, Bartos JA, Cabañas JG, et al; Adult Basic and Advanced Life Support Writing Group. Part 3: Adult Basic and Advanced Life Support: 2020 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2020 Oct 20;142(16_suppl_2):S366-S468. doi: 10.1161/CIR.0000000000000916. Epub 2020 Oct 21. PMID: 33081529.

SplintER Series: A Fateful FOOSH

A 66 year-old man presents with right anterior elbow pain, ecchymosis, and a “lump” in his right upper extremity after a ground level fall (Figure 1). What is your suspected diagnosis? What physical exam maneuver(s) can help you confirm your diagnosis? What is your initial workup in the ED? What imaging confirms the diagnosis? What is your management and disposition?

Figure 1: Case Courtesy of Dr. Peter M. Martin


(more…)

Go to Top