SAEM Clinical Images Series: When it is Not Just a Knot
knot

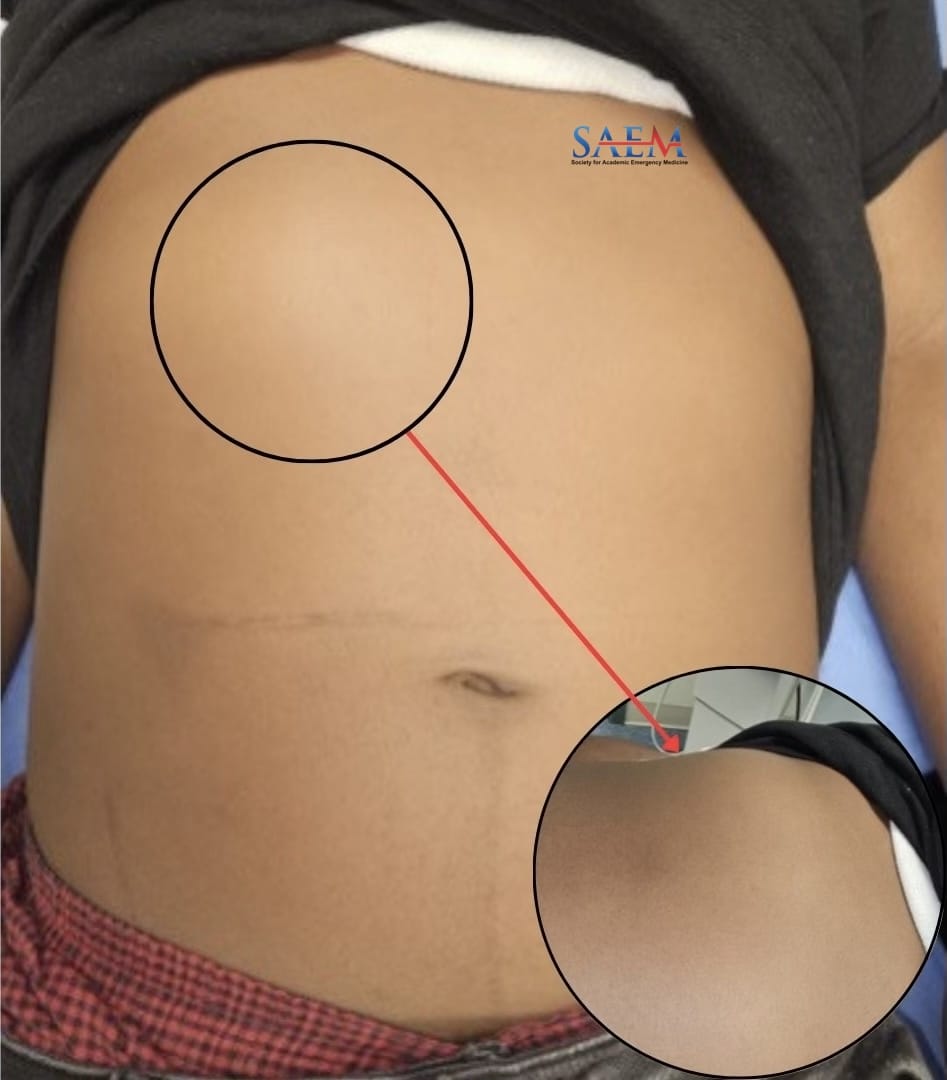
A 12-year-old male with a history of hydrocephalus status post ventriculoperitoneal (VP) shunt placement presented with an abdominal “knot.” The patient’s mother noticed the knot two days ago, on the right anterolateral thorax, which has steadily been increasing in size. The patient had no known trauma to the area or had been bitten or stung by any insect. He has otherwise been complaining of a headache, generalized, without positional changes, improved with home acetaminophen, ice pack, and rest. There were otherwise no associated vision changes, nausea, vomiting, mental status changes, or fever.
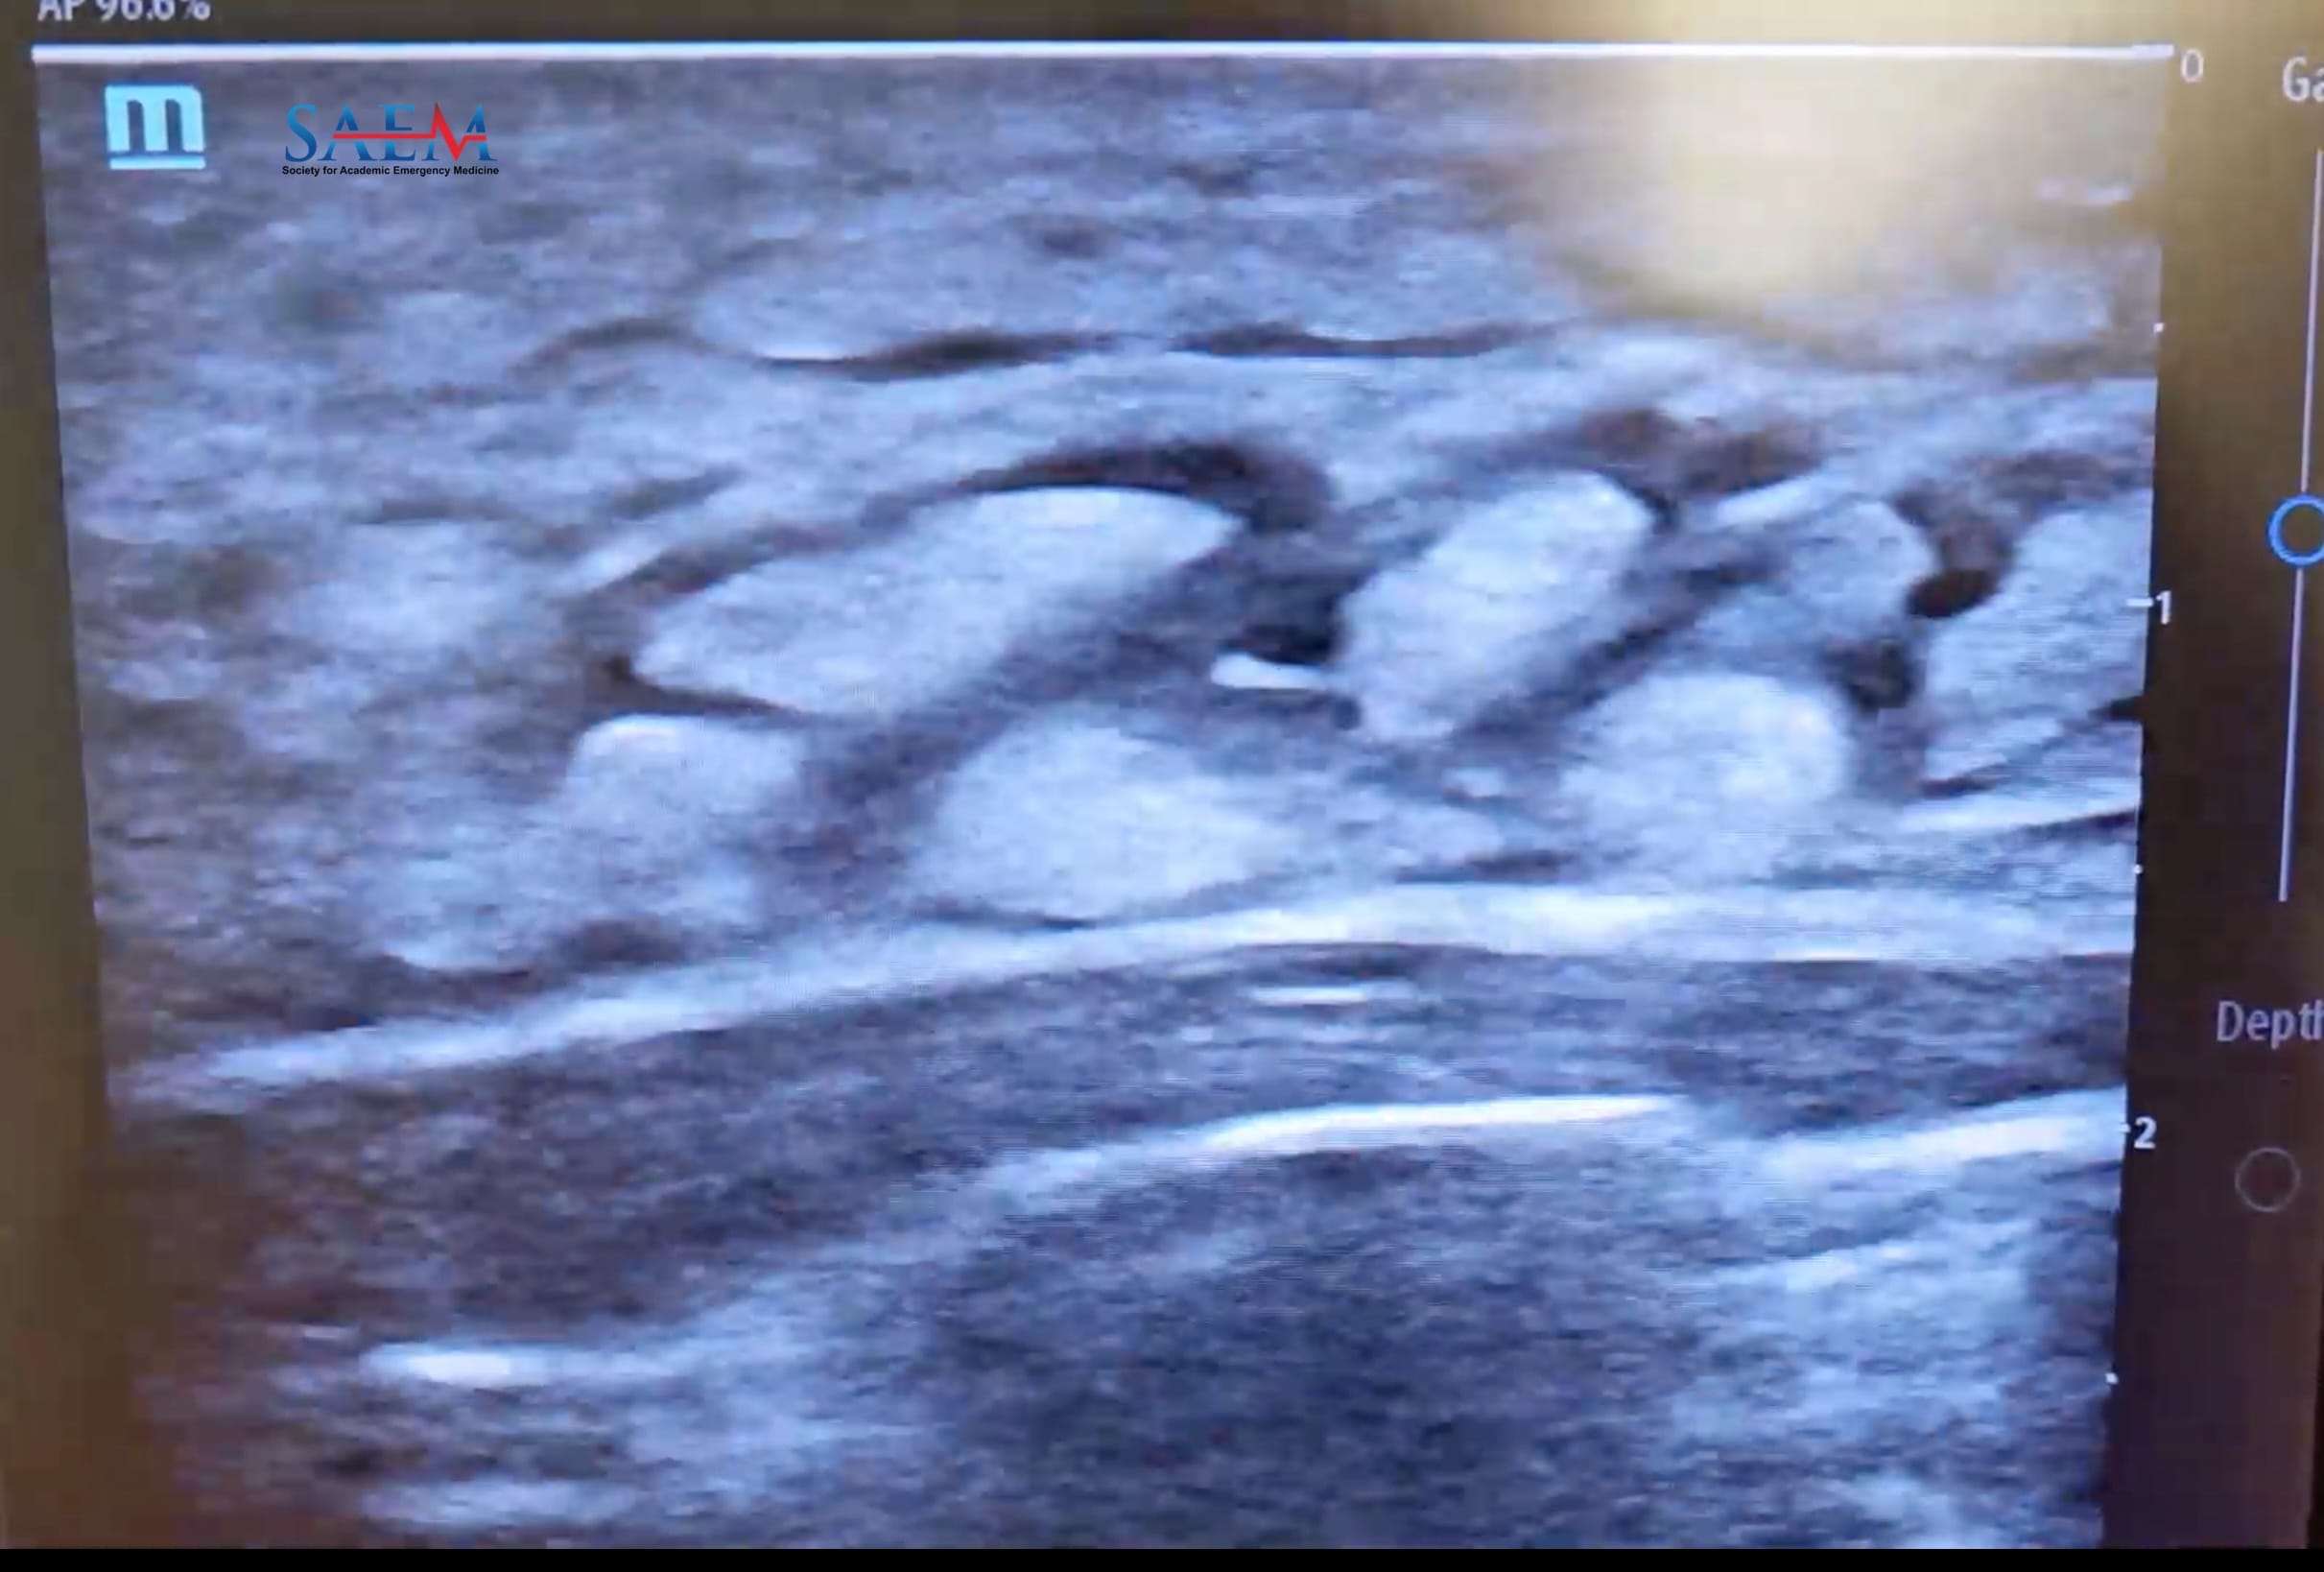
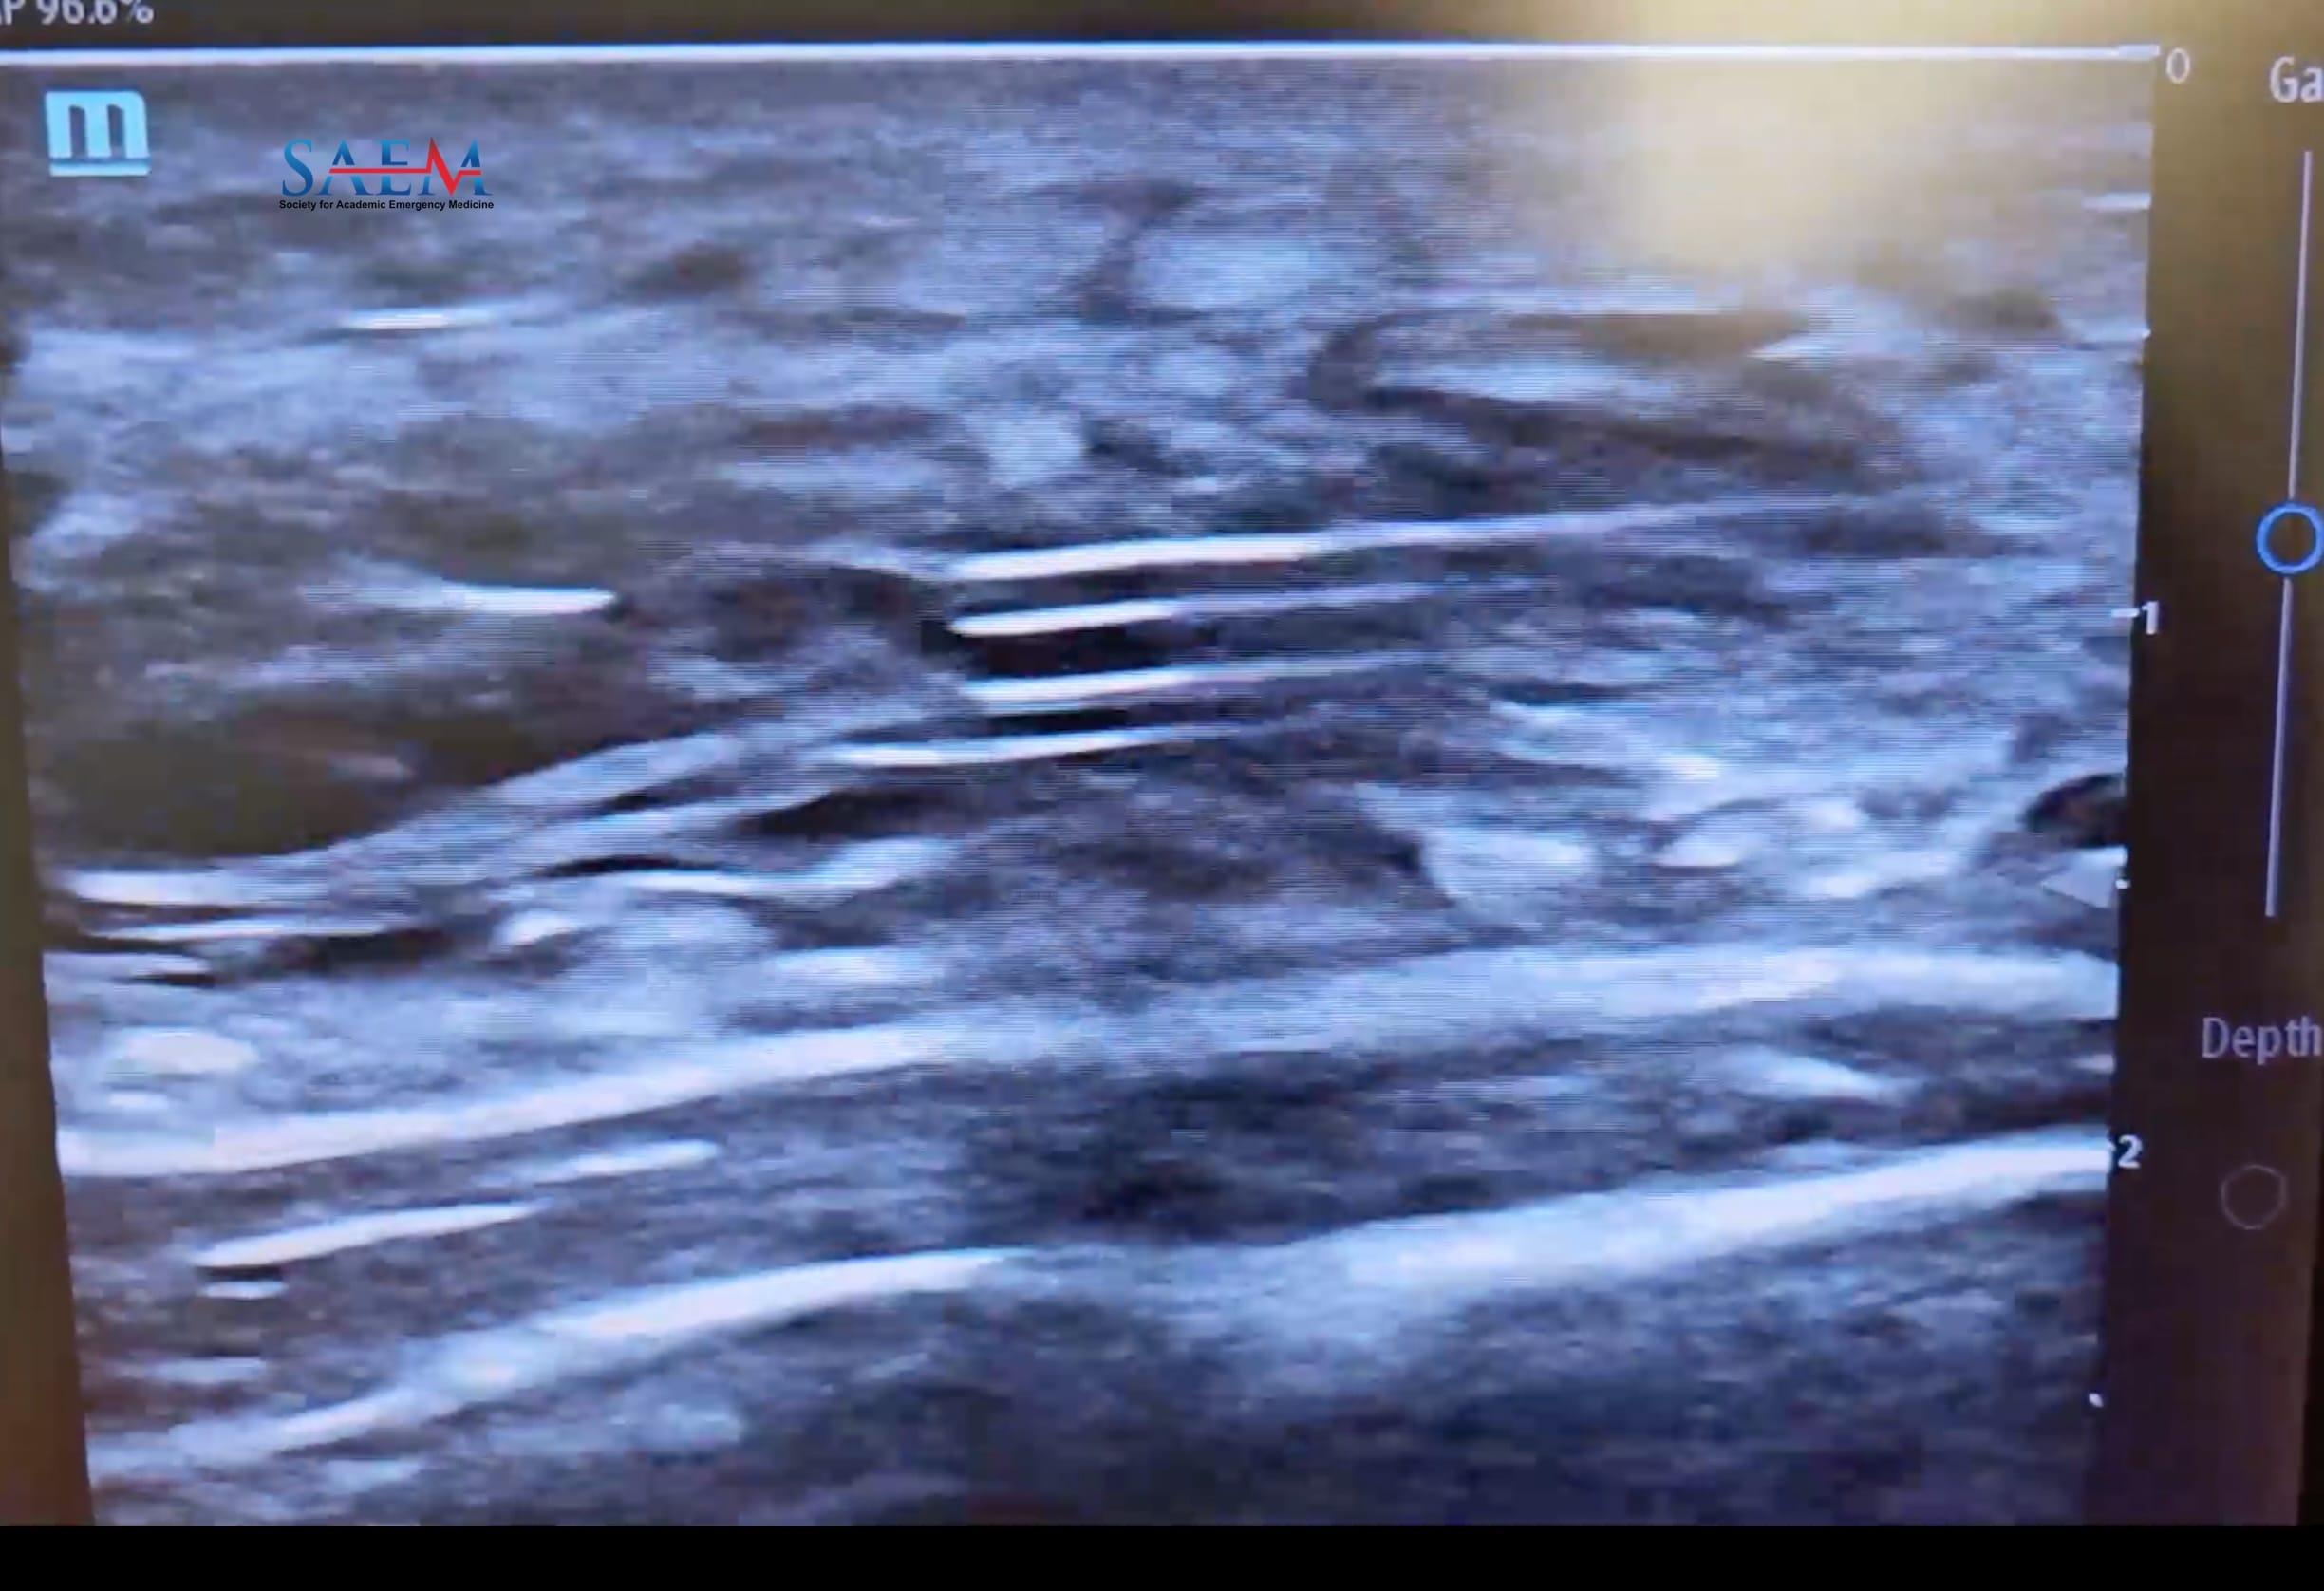
Vitals: T-36.2°C; HR 74 bpm; BP 144/75 mm Hg; RR 20; O2 Sat 96% RA

General: Well-appearing teenager in NAD.

HEENT: NC/AT. PERRL approximately 2-3 mm bilaterally. EOMI.

Neck: Supple, no meningismus.

Chest Wall: Induration to the right anterolateral thorax 5 cm x 4 cm without erythema, fluctuance, or drainage, non-tender to palpation.

Neurological: Alert. No focal neurological deficit observed.

The cause of the knot is subcutaneous cerebrospinal fluid from a shunt malfunction. The ultrasound images show characteristic “cobblestoning,” indicating fluid in the subcutaneous tissue, around a linear hyperechoic object, the catheter of the VP shunt. On the plain film imaging, a disconnect was found between the thoracic and abdominal portions of the VP shunt. Up to 80% of patients with VP shunts will have experienced a shunt malfunction after 12 years, according to one study, with fractured tubing causing shunt failure in around 15% of all cases (1).

Nausea, vomiting, headache, irritability, or decreased mental status are common but nonspecific findings in shunt malfunction. Pediatric patients may present with other signs such as bulging fontanelles, increasing head circumference, or feeding and behavioral changes. An increase in the interval ventricular size can be seen in neuroimaging but can be absent in as many as 20% of patients (2). If there is a high degree of clinical suspicion for shunt malfunction, normal or unchanged neuroimaging should not preclude neurosurgical consultation.

Take-Home Points

  • In the United States, mechanical causes of VP shunt malfunction are the most common presentation, such as catheter obstruction, fracture along the clavicle or ribs, degradation of tubing, and migration of the distal catheter due to changes in height or weight.
  • Rarely, patients can develop an accumulation of CSF at the distal catheter of the VP shunt due to migration into the abdominal wall forming an abdominal pseudocyst.
  • In patients with VP shunts, abdominal complications should be considered as a sign of shunt malfunction.
  • Consider pertinent physical exam findings and POCUS to confirm the diagnosis of shunt malfunction at the distal catheter.

  • Sainte-Rose C, Piatt JH, Renier D, Pierre-Kahn A, Hirsch JF, Hoffman HJ, Humphreys RP, Hendrick EB. Mechanical complications in shunts. Pediatr Neurosurg. 1991-1992;17(1):2-9. doi: 10.1159/000120557. PMID: 1811706.

  • Reynolds RA, Ahluwalia R, Krishnan V, Kelly KA, Lee J, Waldrop RP, Guidry B, Hengartner AC, McCroskey J, Arynchyna A, Staulcup S, Chen H, Hankinson TC, Rocque BG, Shannon CN, Naftel R. Risk factors for unchanged ventricles during pediatric shunt malfunction. J Neurosurg Pediatr. 2021 Sep 24;28(6):703-709. doi: 10.3171/2021.6.PEDS2125. PMID: 34560626.
By |2025-02-19T12:57:12-08:00Feb 21, 2025|Neurology, Pediatrics, SAEM Clinical Images, Ultrasound|

SAEM Clinical Images Series: A Rare Gastrointestinal Complication of an Endocrine Emergency

A 54-year-old woman with a history of hypothyroidism, diabetes mellitus type II, COPD, asthma, anxiety, and depression presented to the emergency department via EMS with three days of fatigue, weakness, chills, and shortness of breath without chest pain or cough. Symptoms had been progressively worsening, and she stated she felt as if she could not move her body on presentation. She also noted diarrhea without abdominal pain, melena, or hematochezia. Just prior to arrival the patient’s daughter thought she looked paler and shorter of breath and called EMS after a near syncopal episode. EMS reported that the family was concerned that the patient’s blood glucose level was low. Blood glucose upon EMS arrival was 90 and rose to 150 following their administration of oral glucose. The patient denied fever, recent sick contacts, urinary changes, hematuria, or leg swelling. She reported two missed doses of levothyroxine which was prescribed at a dose of 25 mcg daily. No recent antibiotic use reported.

Vitals: Temp 36.4°C; BP 106/64 mmHg; HR 62 bpm; Resp 16/min; SpO2 96% on RA

General: Patient drowsy, slow to answer questions, sitting with eyes closed. No obvious distress.

Skin: Warm and dry.

Cardiovascular: Regular rate and rhythm without murmur.

Respiratory: Lungs clear to auscultation bilaterally. No respiratory distress.

Abdomen: Soft, non-distended, normal bowel sounds, diffuse abdominal discomfort to palpation, which she states is chronic.

Neurological: Oriented to person, place, time. CN II-XII intact. No focal neurological deficit observed, strength 4+/5 throughout able to hold all extremities up when placed above the body.

Extremities: No obvious swelling.

CBC: Hb 11.5, WBC 9.5, Plt 186

BMP: Na 141, K 3.8, Cl 105, CO2 24, BUN 17, Cr 1.3

LFTs: AST 20, ALT 11, Bili 0.4

VBG: pH 7.28, PCO2 60, HCO2 28

Mg: 1.7

CK: 333

TSH: 196.80

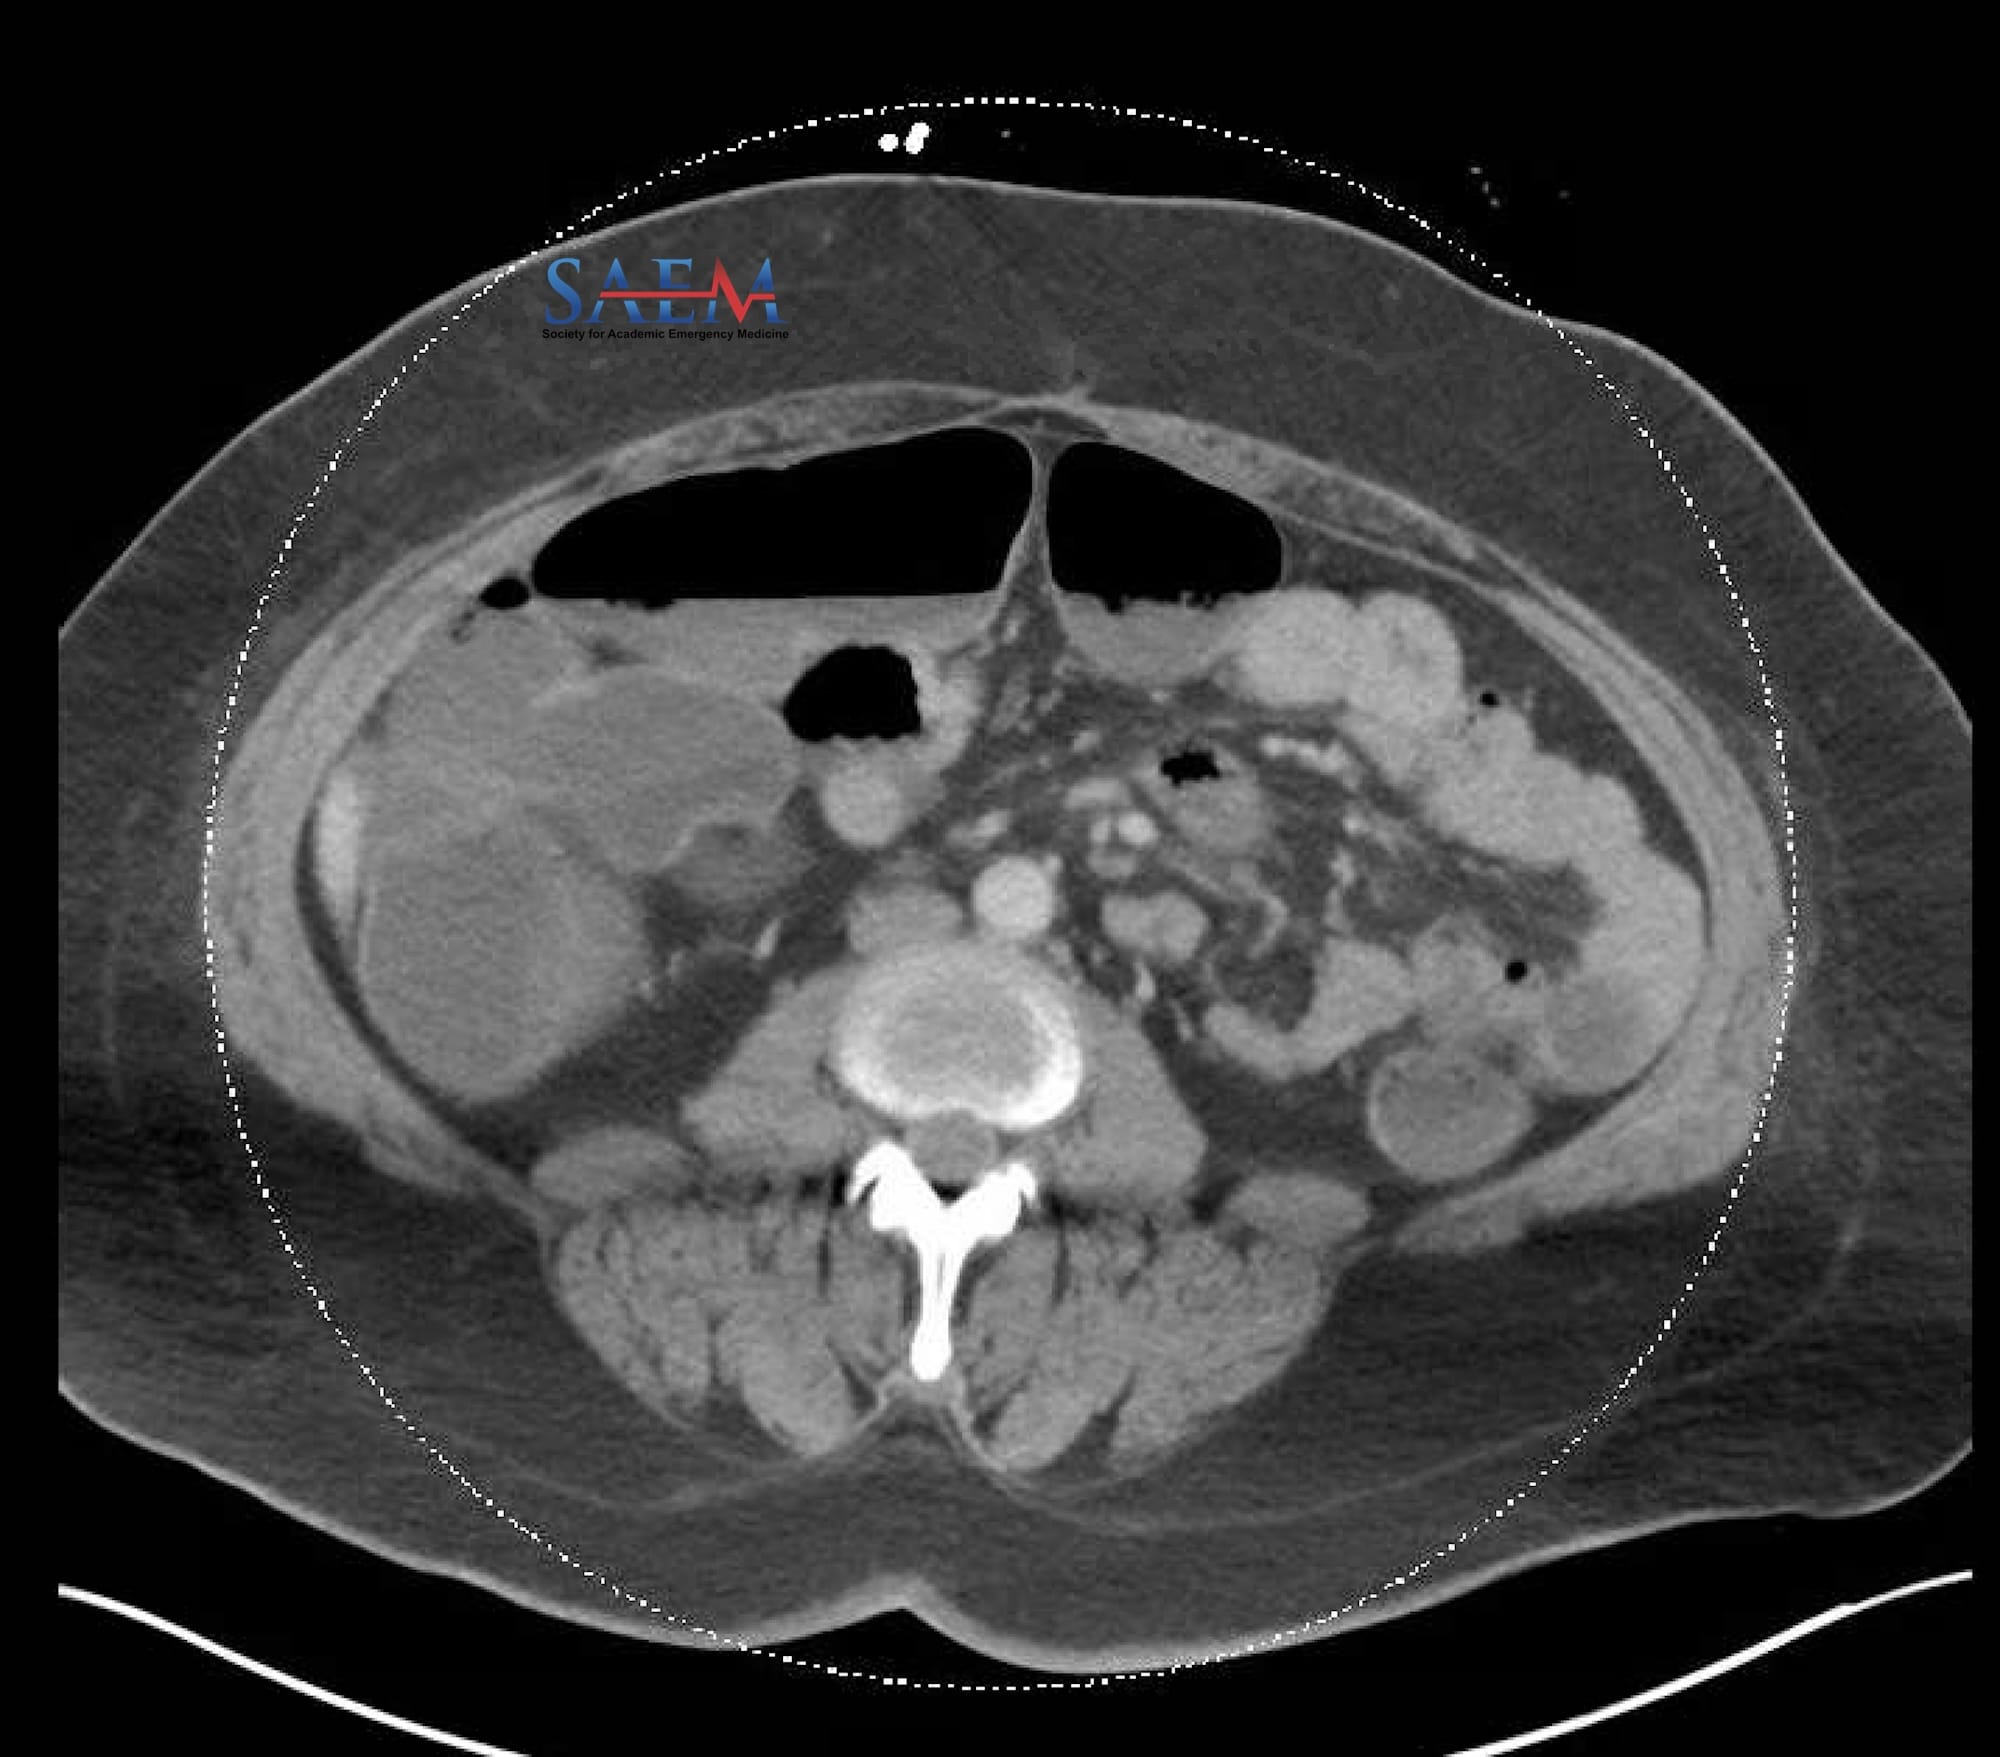
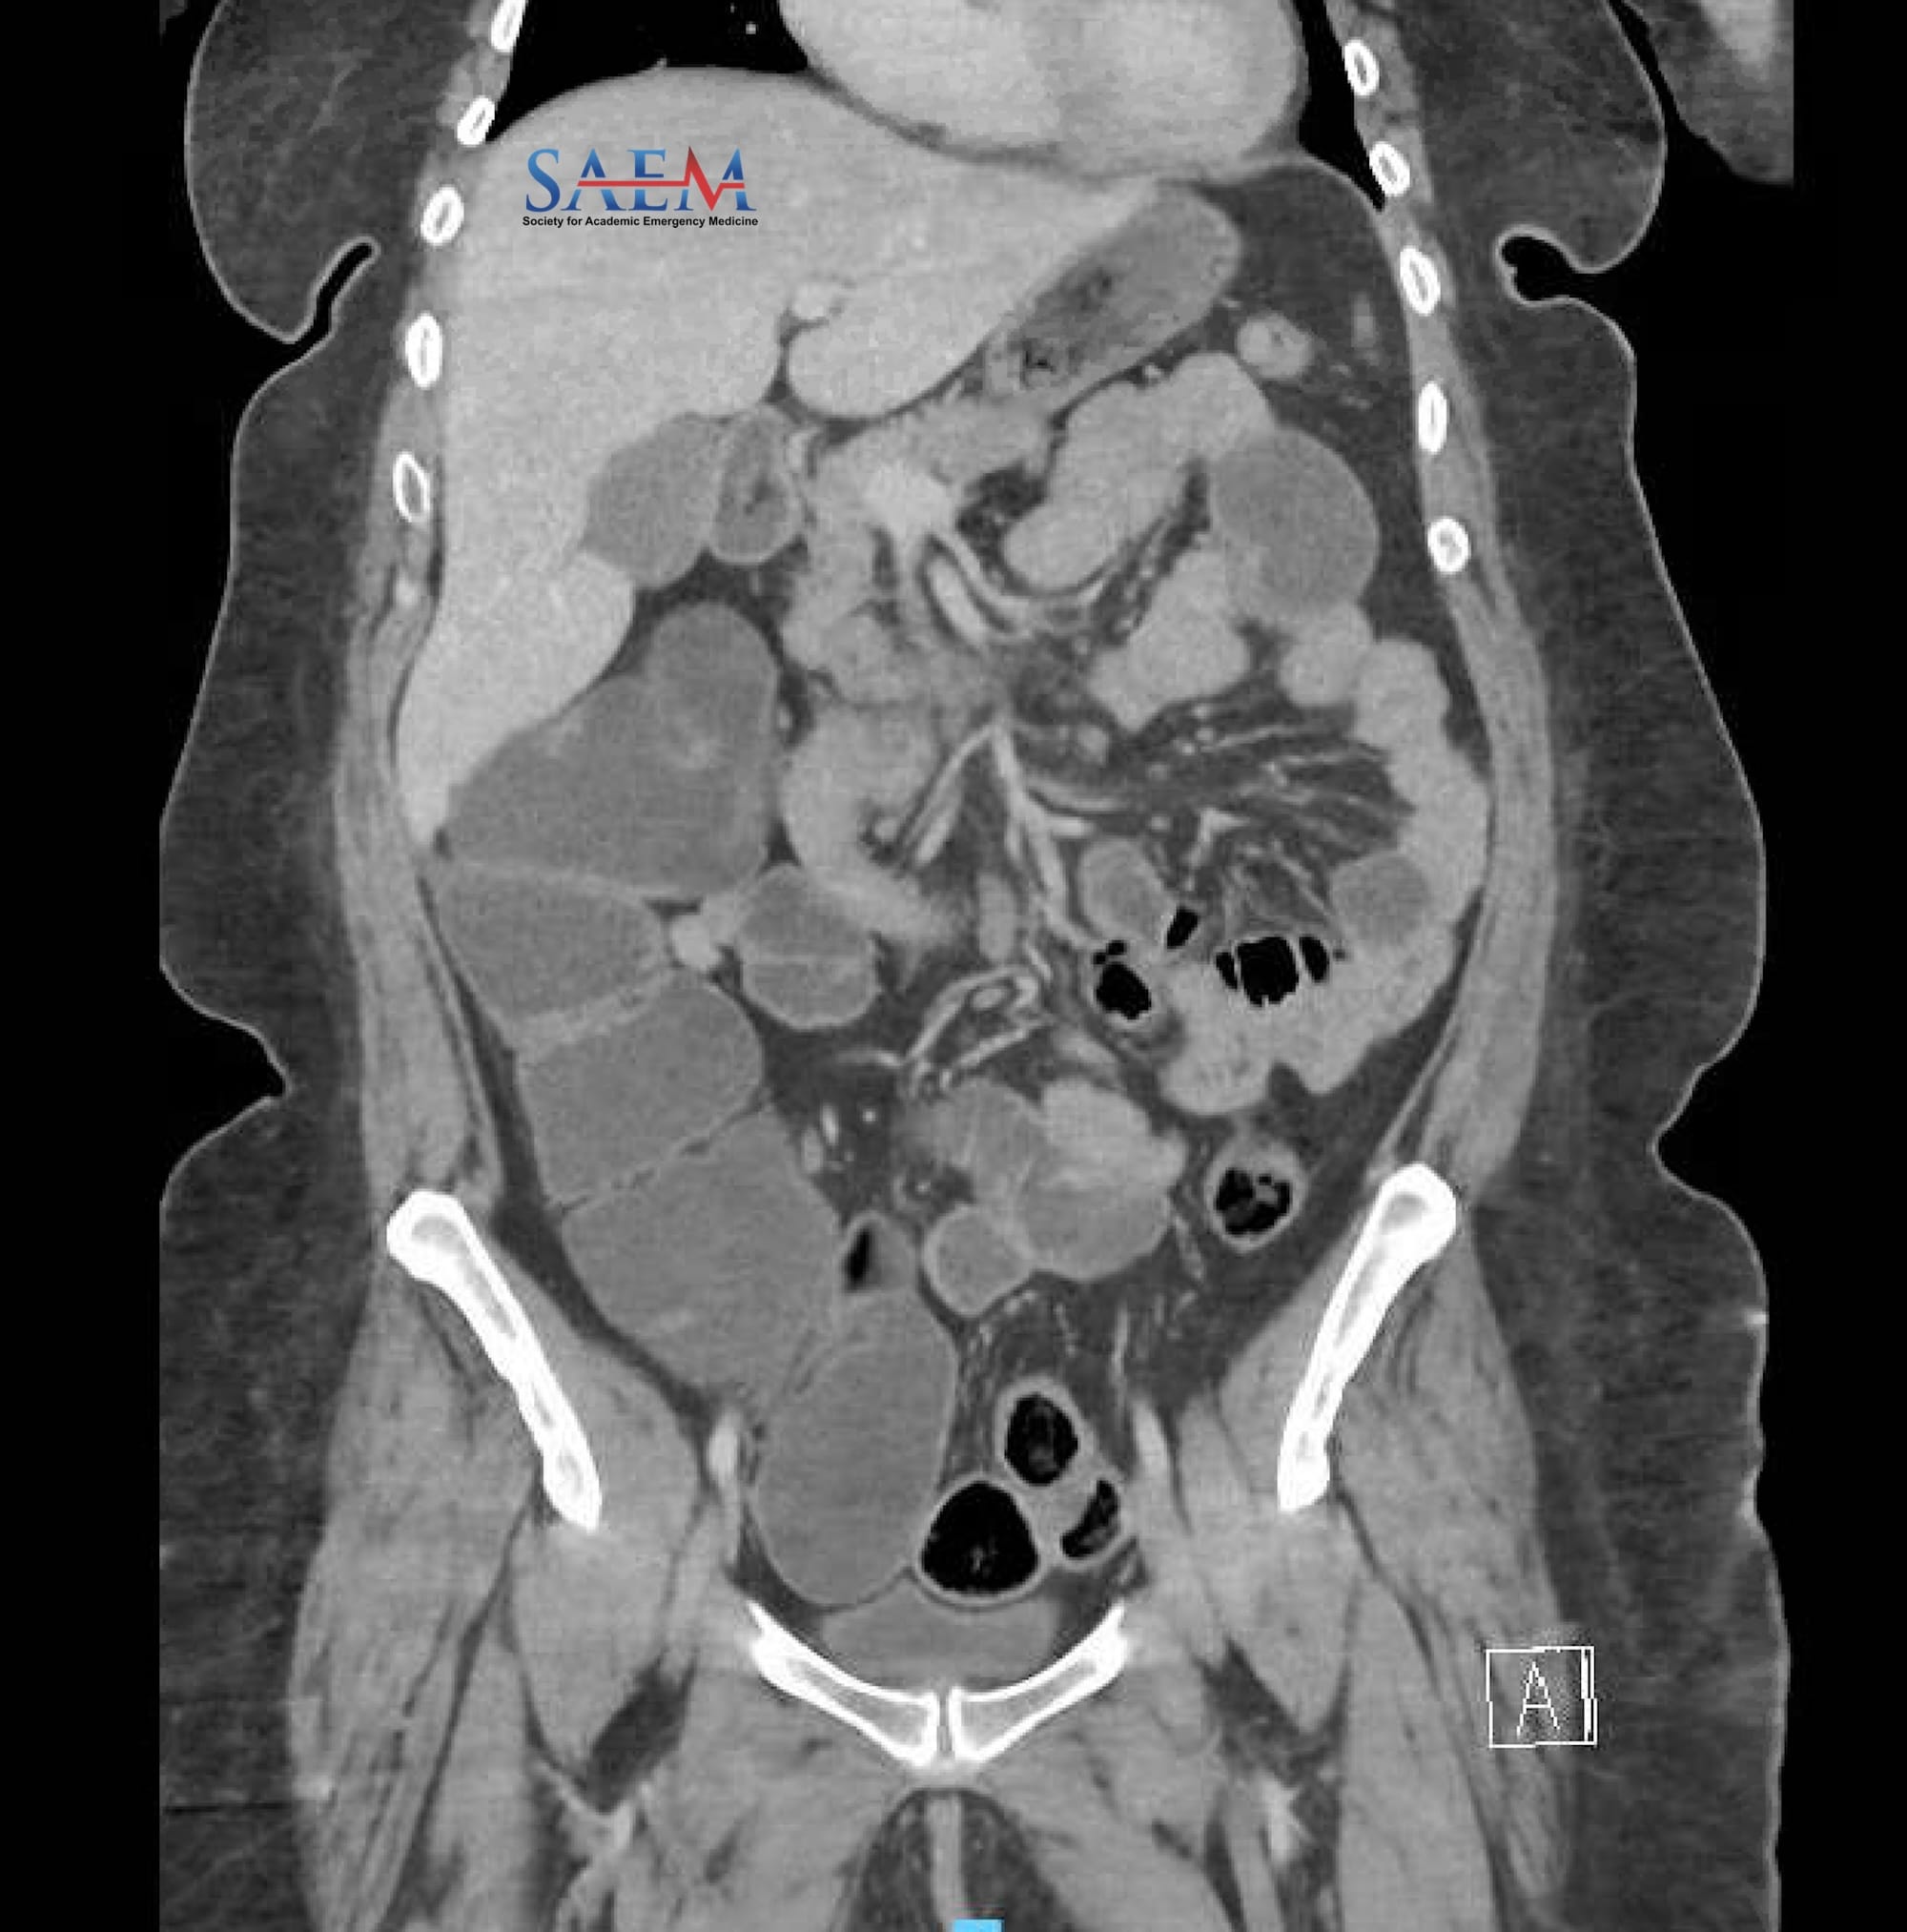
The abdominal CT scan demonstrates multiple fluid-filled mildly dilated loops of large bowel with air-fluid levels, some minimally dilated loops of small bowel, and no clear transition point identified which is concerning for developing colonic pseudo-obstruction (Ogilvie Syndrome). There are many predisposing factors that may cause Ogilvie Syndrome including recent surgery, infection, trauma, respiratory failure, cancer, and other metabolic conditions.

Given our patient’s history of hypothyroidism with missed doses of levothyroxine and an elevated TSH her cause of Ogilvie syndrome is most likely hypothyroidism. This is also known as myxedema ileus, a rare entity. Management of myxedema ileus consists of bowel decompression with a nasogastric tube and treatment of the hypothyroid condition. In our case, the patient received 200 mcg of levothyroxine, and 12.5 mcg of liothyronine while undergoing further endocrinologic workup

Take-Home Points

  • In patients with a history of hypothyroidism presenting with gastrointestinal concerns, myxedema ileus, while not common, should be considered.
  • Colonic pseudo-obstruction (Ogilvie syndrome) has many causes and the radiographic appearance of a bowel obstruction without an obvious transition point.
  • Myxedema ileus should be managed with bowel decompression and treatment of the underlying hypothyroidism. ICU level care is often needed for this severe endocrine emergency

  • Saunders MD. Acute colonic pseudo-obstruction. Best Pract Res Clin Gastroenterol. 2007;21(4):671-87. doi: 10.1016/j.bpg.2007.03.001. PMID: 17643908.

  • Vanek VW, Al-Salti M. Acute pseudo-obstruction of the colon (Ogilvie’s syndrome). An analysis of 400 cases. Dis Colon Rectum. 1986 Mar;29(3):203-10. doi: 10.1007/BF02555027. PMID: 3753674.

ALiEM AIR Series | GI Module (2024)

ALiEM AIR Certified seal and GI 2024 module shield badge

Welcome to the AIR GI Module! After carefully reviewing all relevant posts in the past 12 months from the top 50 sites of the Digital Impact Factor [1], the ALiEM AIR Team is proud to present the highest quality online content related to related to GI emergencies in the Emergency Department. 11 blog posts met our standard of online excellence and were approved for residency training by the AIR Series Board. More specifically, we identified 3 AIR and 8 Honorable Mentions. We recommend programs give 6 hours of III credit for this module.

AIR Stamp of Approval and Honorable Mentions

In an effort to truly emphasize the highest quality posts, we have 2 subsets of recommended resources. The AIR stamp of approval is awarded only to posts scoring above a strict scoring cut-off of ≥30 points (out of 35 total), based on our scoring instrument. The other subset is for "Honorable Mention" posts. These posts have been flagged by and agreed upon by AIR Board members as worthwhile, accurate, unbiased, and appropriately referenced despite an average score.

Take the GI Module at ALiEMU

Interested in taking the AIR quiz for fun or asynchronous (Individualized Interactive Instruction) credit? Please go to the above link. You will need to create a free, 1-time login account.

Highlighted Quality Posts: GI 2024

Site Article Author Date Label
EMCrit Acute liver failure Dr. Josh Farkas March 20, 2023 AIR
EMCrit Spontaneous Bacterial peritonitis Dr. Josh Farkas April 17, 2023 AIR
EMCrit GI Bleeding Dr. Josh Farkas April 14, 2023 AIR
RebelEM SBO Dr. Anand Swaminathan January 25, 2023 HM
EM Ottawa Rethinking Acute Pancreatitis in the ED Dr. Kevin Guo May 11, 2023 HM
EMCrit Hepatic Encephalopathy in chronic liver disease Dr. Josh Farkas April 3, 2023 HM
EMCrit Hepatorenal syndrome causing AKI Dr. Josh Farkas April 3, 2023 HM
EM Docs LBO: ED Presentation, evaluation, management Dr. Christopher Whiting July 17, 2023 HM
EM Docs Guideline Update: Acute Lower GI Bleeding Dr. Brit Long November 20, 2023 HM
EM Docs ED evaluation of Cholestatic labs Dr. Amelia Campbell March 4, 2024 HM
PEM Morsels Acute esophageal variceal bleeding in children Dr. Sean Fox June 9, 2023 HM

(AIR = Approved Instructional Resource; HM = Honorable Mention)

If you have any questions or comments on the AIR series, or this AIR module, please contact us!

Reference

    1. Lin M, Phipps M, Chan TM, et al. Digital Impact Factor: A Quality Index for Educational Blogs and Podcasts in Emergency Medicine and Critical Care. Ann Emerg Med. 2023;82(1):55-65. doi:10.1016/j.annemergmed.2023.02.011, PMID 36967275


SAEM Clinical Images Series: Male Weightlifter with Chest Pain

hyperacute

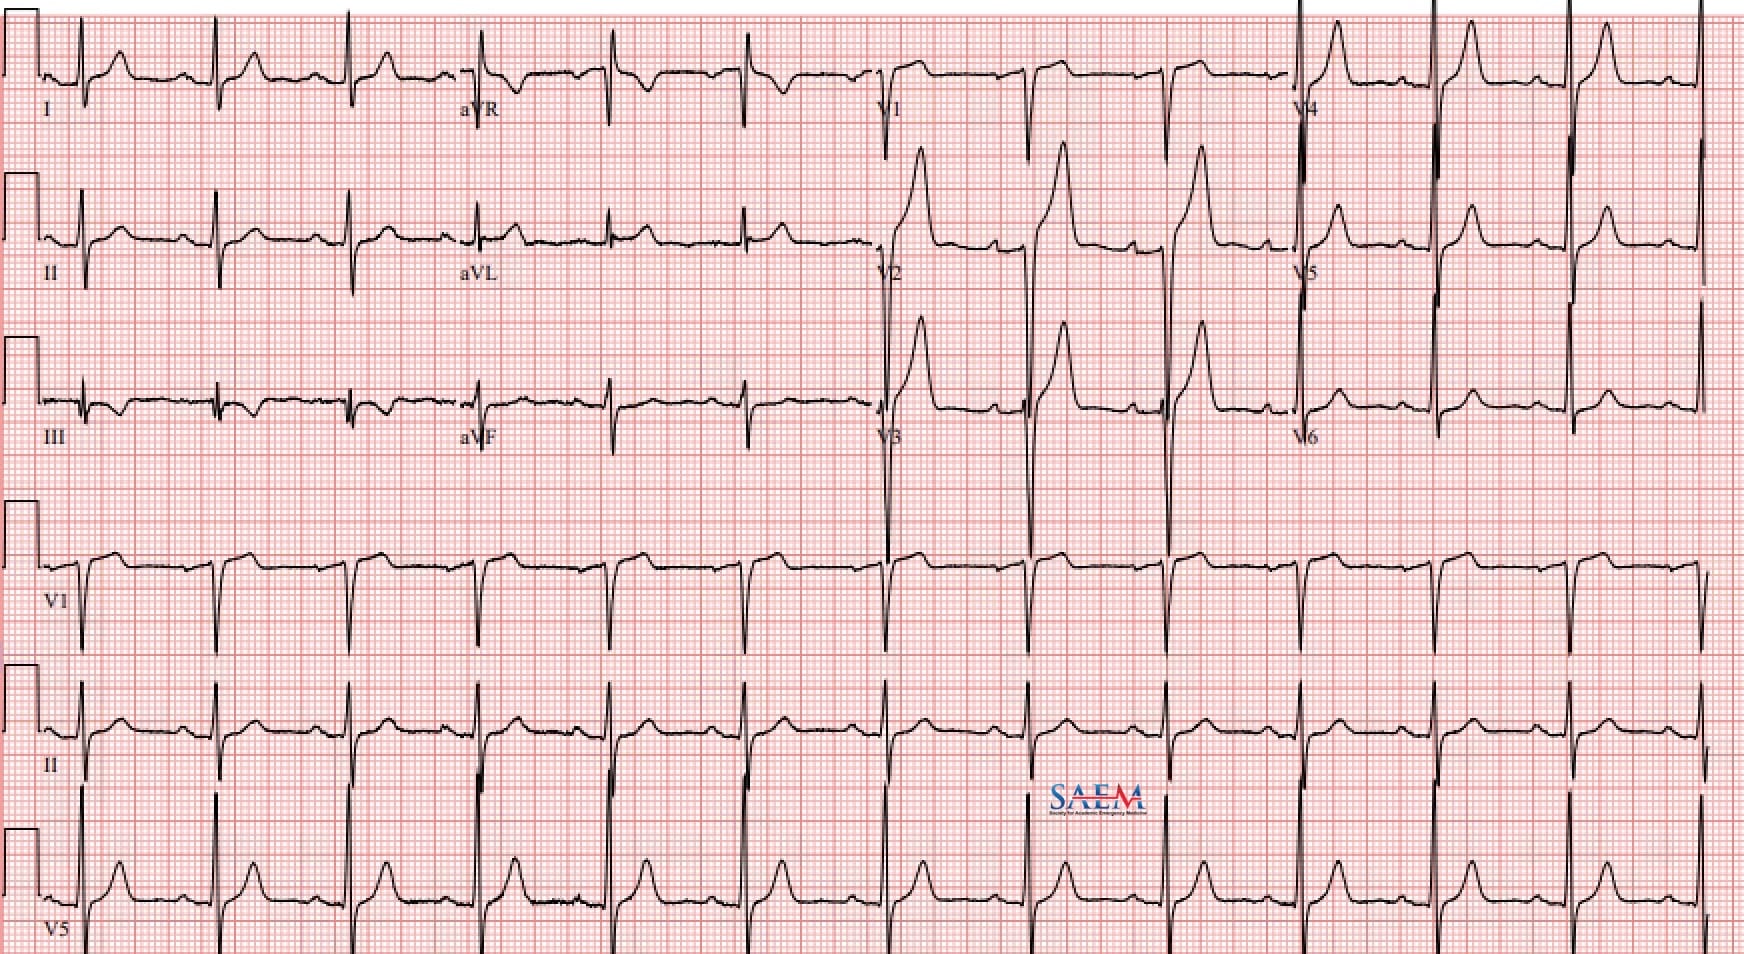
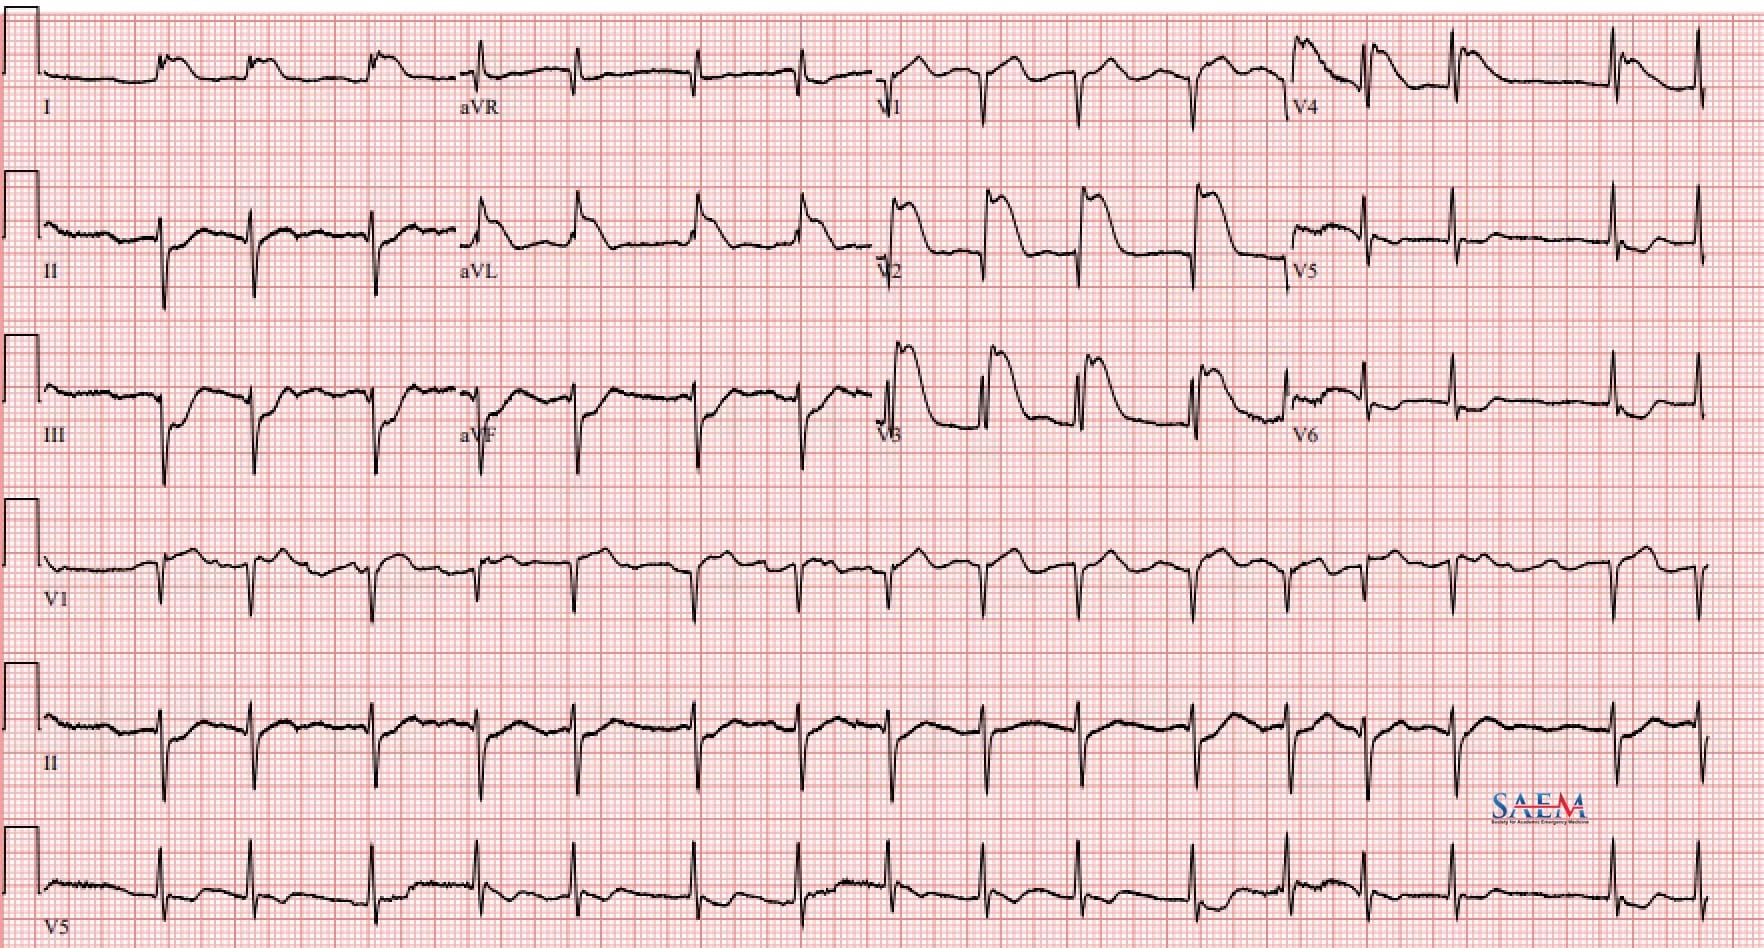
An otherwise healthy 45-year-old male presented to the emergency department (ED) with substernal chest pain radiating down his left arm over the previous two days. On the first day of symptoms, his pain began several hours after using a new pre-workout supplement and weightlifting. The symptoms lasted for a few hours and self-resolved. The pain returned the following day under the same conditions, although this time persistent, which brought him in for evaluation. Associated symptoms included shortness of breath, nausea, and one episode of emesis. He denied pleuritic pain, lower extremity edema, hemoptysis, syncope, cough, or chest wall trauma. On further history, he reported prior use of anabolic steroids, with the last being six weeks prior to presentation. It was unclear what were the contents of the pre-workout supplement, but he denied any tobacco or illicit drug use. Notably, he had a significant family history of heart disease with his father having undergone coronary bypass at age 47. His initial ECG (Image 1) and interval ECG (Image 2) are shown.

Vitals: T 36.5°C; HR 74; RR 16; BP 161/107; SpO2 98% on RA

General: Uncomfortable and diaphoretic in moderate distress.

Cardiovascular: Normal rate and rhythm, no murmurs. Equal radial and PT pulses bilaterally.

Pulmonary: Non-labored breathing, lungs CTA bilaterally with equal breath sounds.

Extremities: Lower extremities without significant edema, symmetric in size.

Neuro: Alert and oriented, neurologically intact.

Complete blood count (CBC): mild polycythemia (Hgb 19.0 g/dL) and leukocytosis (WBC 10.1 x 10(9)/L)

Basic metabolic panel (BMP): Cr 1.22 mg/dL, GFR 75 mL/min/BSA, K 4.5 mmol/L

Troponin T, 5th generation: 97 ng/L (ref. range: <=15 mg/L)

Acute coronary syndrome (ACS) with myocardial infarction. Hyperacute T waves are seen on the initial ECG.

This patient’s initial ECG (Image 1) raised concern for hyperacute T waves, which are often described as broad-based with a large amplitude. This subtle finding is difficult to differentiate from normal variants, hypertrophy, or hyperkalemia (1,2). Hyperacute T waves have been considered an early sign of acute coronary occlusion, however, current literature is mixed regarding their clinical utility, particularly given the lack of a formal ECG definition (3,4,5). The American College of Cardiology (ACC) recommends obtaining serial ECGs in patients with hyperacute T waves to assess for progression to STEMI (3). In this patient’s case, interventional cardiology was consulted, and the patient was given aspirin and sublingual nitroglycerin. He developed worsened chest pain, and a repeat ECG showed no significant changes. Shortly after, he went into ventricular fibrillation and cardiac arrest. A post-ROSC ECG (Image 2) showed concave ST elevations in the anterolateral leads with reciprocal ST depressions in the inferior leads, meeting STEMI criteria. Coronary angiography showed severe multivessel disease and 100% occlusion of the left anterior descending (LAD) artery. A drug-eluting stent was placed, and the patient was discharged home one week later with an intact neurologic status.

History of anabolic steroid use, pre-workout supplementation, and significant family history of CAD. In more recent years, the number of younger patients (35-54 years) hospitalized for ACS has increased (6). This trend is believed to be related to the increased use of illicit drugs, including marijuana and androgenic-anabolic steroids (AAS) (6). AAS is known to increase the risk of cardiac hypertrophy, ACS, and sudden cardiac death by increasing lipoprotein production, causing intimal hyperplasia of coronary arteries, and increasing clotting factors leading to a procoagulant state (7,8). Consensus on the adverse effects and overall safety of pre-workout supplements remains under debate and they remain unregulated by the FDA. Studies suggest that synephrine, a common product found in pre-workout supplements, may raise safety concerns due to its androgenic properties (9). A 2023 systematic review of adverse outcomes related to synephrine found associations with cardiomyopathy, ACS, arrhythmias, and cerebrovascular disease (9,10).

Take-Home Points

  • Hyperacute T waves, although not diagnostic in isolation, may be an early marker for occlusion myocardial infarction and if seen, serial ECGs should be performed.

  • A high degree of clinical suspicion for ACS should be maintained among patients with a history of androgenic-anabolic steroid use, even in young and otherwise healthy individuals.

  • Pre-workout supplements, especially those that contain the compound synephrine have been associated with ACS and other cardiovascular pathology.

  • Somers MP, Brady WJ, Perron AD, et al. The prominent T wave: electrocardiographic differential diagnosis. Am J Emerg Med 2002 May;20(3):243-51

  • Levis JT. ECG Diagnosis: Hyperacute T Waves. Perm J. 2015 Summer;19(3):79. doi: 10.7812/TPP/14-243. PMID:26176573; PMCID: PMC4500486.

  • Writing Committee; Kontos MC, de Lemos JA, Deitelzweig SB, Diercks DB, Gore MO, Hess EP, McCarthy CP, McCord JK, Musey PI Jr, Villines TC, Wright LJ. 2022 ACC Expert Consensus Decision Pathway on the Evaluation and Disposition of Acute Chest Pain in the Emergency Department: A Report of the American College of Cardiology Solution Set Oversight Committee. J Am Coll Cardiol. 2022 Nov 15;80(20):1925-1960. doi: 10.1016/j.jacc.2022.08.750. Epub 2022 Oct 11. PMID: 36241466; PMCID: PMC10691881.

  • Koechlin L, Strebel I, Zimmermann T, Nestelberger T, Walter J, Lopez-Ayala P, Boeddinghaus J, Shrestha S, Arslani K, Stefanelli S, Reuthebuch B, Wussler D, Ratmann PD, Christ M, Badertscher P, Wildi K, Giménez MR, Gualandro DM, Miró Ò, Fuenzalida C, Martin-Sanchez FJ, Kawecki D, Bürgler F, Keller DI, Abächerli R, Reuthebuch O, Eckstein FS, Twerenbold R, Reichlin T, Mueller C; APACE investigators. Hyperacute T Wave in the Early Diagnosis of Acute Myocardial Infarction. Ann Emerg Med. 2023 Aug;82(2):194-202. doi: 10.1016/j.annemergmed.2022.12.003. Epub 2023 Feb 10. PMID: 36774205.

  • Smith SW, Meyers HP. Hyperacute T-waves Can Be a Useful Sign of Occlusion Myocardial Infarction if Appropriately Defined. Ann Emerg Med. 2023 Aug;82(2):203-206. doi: 10.1016/j.annemergmed.2023.01.011. Epub 2023 Mar 3. PMID: 36872197.

  • Bhatt DL, Lopes RD, Harrington RA. Diagnosis and Treatment of Acute Coronary Syndromes: A Review. JAMA. 2022;327(7):662-675.

  • Melchert RB, Welder AA. Cardiovascular effects of androgenic-anabolic steroids. Med Sci Sports Exerc. 1995;27(9):1252-1262.

  • Pope HG, Jr., Kanayama G, Athey A, Ryan E, Hudson JI, Baggish A. The lifetime prevalence of anabolic-androgenic steroid use and dependence in Americans: current best estimates. Am J Addict. 2014;23(4):371-377.

  • de Jonge MLL, Kieviet LC, Sierts M, Egberink LB, van der Heyden MAG. Review of Case Reports on Adverse Events Related to Pre-workout Supplements Containing Synephrine. Cardiovasc Toxicol. 2023 Jan;23(1):1-9. doi: 10.1007/s12012-022-09777-z. Epub 2023 Jan 13. PMID: 36639595; PMCID: PMC9859859.

  • Flo FJ, Kanu O, Teleb M, Chen Y, Siddiqui T. Anabolic androgenic steroid-induced acute myocardial infarction with multiorgan failure. Proc (Bayl Univ Med Cent). 2018;31(3):334-336

ACMT Toxicology Visual Pearl: Hiss-teria Averted

snake

What is the predominant clinical effect of envenomation by this snake?

  1. Acute hepatic failure leading to coagulopathy
  2. Direct cardiotoxicity leading to arrhythmias
  3. Profound neuromuscular paralysis
  4. Rapid onset of shock and multisystem organ failure

[Image courtesy of iStock. ID: 1311554579]

(more…)

Go to Top