52 Articles in 52 Weeks, 3rd edition (2022)

How can I keep up with so many landmark articles in Emergency Medicine (EM)? This is an often asked question we hear from interns and residents. Published in 2013 (1st edition) and 2016 (2nd edition), the “52 Articles in 52 Weeks” compendium is a compilation of 52 journal articles provided interns a list to read over a 52-week period, at an average pace of 1 journal article per week. We present the updated 2022 compilation.

Methodology for Article Selection

We primarily build off of the original list from 2016. These 52 articles were refreshed such that newer landmark articles replaced those on the same topic.  Additional publications were considered if they were cited on MDCalc’s site or reviewed on clinical EM websites like REBEL EM, Wiki Journal Club, and The Bottom Line during 2016-2022. A panel of 7 EM faculty with a niche in graduate medical education could also add publications for consideration. A total of 71 articles were scored by these 7 faculty using the Best Evidence in Emergency Medicine (BEEM) score with an EM intern audience in mind.

Best Evidence in Emergency Medicine (BEEM) Scoring [1]

Question for reviewer: Assuming that the results of this article are valid, how much does this article impact on EM clinical practice?

BEEM Score Description (revised for EM intern audience)
1 Useless information
2 Not really interest, not really new, changes nothing
3 Interesting and new, but doesn’t change practice
4 Interesting and new, has the potential to change practice
5 New and important: this would probably change practice for some EM interns
6 New and important: this would change practice for most EM interns
7 This is a “must know for EM interns

Results

The final list of the top 52 articles, based on the mean BEEM scores, are presented below in descending rank order. A bonus 53rd article is also listed because there was a 4-way tie for articles #50-53. Feel free to copy-paste this list into your own Google Sheets or Excel spreadsheet for list sortability.

Project Lead

  • Nicholas Dulin, MD (EM Resident, Department of Emergency Medicine, Einstein Medical Center; Captain, Medical Corps, United States Air Force)

Faculty Raters

  1. Claire Abramoff, MD (Assistant Residency Program Director, Department of Emergency Medicine, Einstein Medical Center)
  2. Layla Abubshait, MD (Associate Residency Program Director, Department of Emergency Medicine, Einstein Medical Center Montgomery)
  3. Jacqueline Dash, MS, DO (Core Faculty, Department of Emergency Medicine, Einstein Medical Center)
  4. Joseph Herres, DO (Research Director, Department of Emergency Medicine, Einstein Medical Center)
  5. Jessica Parsons, MD (Associate Program Director, Department of Emergency Medicine, Einstein Medical Center)
  6. Anthony Sielicki, MD (Assistant Program Director, Department of Emergency Medicine, Einstein Medical Center)
  7. Steven J. Walsh, MD (Medical Toxicology Faculty, Einstein Medical Center)

Reference

  1. Worster A, Kulasegaram K, Carpenter C, et al. Consensus conference follow-up: inter-rater reliability assessment of the Best Evidence in Emergency Medicine (BEEM) rater scale, a medical literature rating tool for emergency physicians. Acad Emerg Med. 2011;18(11):1193-1200. [PubMed]

ALiEM AIR Series | Neurology 2022 Module

air series

Welcome to the AIR Neurology 2022 Module! After carefully reviewing all relevant posts in the past 12 months from the top 50 sites of the Social Media Index, the ALiEM AIR Team is proud to present the highest quality online content related to related to neurologic emergencies in the Emergency Department. 5 blog posts met our standard of online excellence and were approved for residency training by the AIR Series Board. More specifically, we identified 2 AIR and 3 Honorable Mentions. We recommend programs give 3 hours of III credit for this module.

AIR Stamp of Approval and Honorable Mentions

In an effort to truly emphasize the highest quality posts, we have 2 subsets of recommended resources. The AIR stamp of approval is awarded only to posts scoring above a strict scoring cut-off of ≥30 points (out of 35 total), based on our scoring instrument. The other subset is for "Honorable Mention" posts. These posts have been flagged by and agreed upon by AIR Board members as worthwhile, accurate, unbiased, and appropriately referenced despite an average score.

Take the AIR Neurology 2022 Module at ALiEMU

Interested in taking the AIR quiz for fun or asynchronous (Individualized Interactive Instruction) credit? Please go to the above link. You will need to create a free, 1-time login account.

Highlighted Quality Posts: Neurologic Emergencies

Site Article Author(s) Date Label
EMDocs Cauda Equina Syndrome: Why do we miss it? How to improve? John H. Priester, MD; Mark Bisanzo, MD 13 Jun 2021 AIR
EMCrit Spinal Epidural Abscess Josh Farkas, MD 25 Feb 2022 AIR
Clinical Monster Must Be Blood on the Brain Molly Piccione, DO 3 June 2021 HM
EMCrit Neuro emergencies in pregnancy Josh Farkas, MD 23 Feb 2022 HM
EMCrit Neuro-onc emergencies Josh Farkas, MD 2 June 2022 HM

(AIR = Approved Instructional Resource; HM = Honorable Mention)


If you have any questions or comments on the AIR series, or this AIR module, please contact us! More in-depth information regarding the Social Media Index.

Thank you to the Society of Academic Emergency Medicine (SAEM) and the Council of EM Residency Directors (CORD) for jointly sponsoring the AIR Series! We are thrilled to partner with both on shaping the future of medical education.

ALiEM AIR Series | Ortho Upper Extremity 2022 Module

air series


Welcome to the AIR Orthopedic Upper Extremity Module! After carefully reviewing all relevant posts from the top 50 sites of the Social Media Index, the ALiEM AIR Team is proud to present the highest quality online content related to related to Orthopedic Upper Extremity emergencies in the Emergency Department. 3 blog posts met our standard of online excellence and were curated and approved for residency training by the AIR Series Board. We identified 1 AIR and 2 Honorable Mentions. We recommend programs give 2 hours (about 40 minutes per article) of III credit for this module.

AIR Stamp of Approval and Honorable Mentions

In an effort to truly emphasize the highest quality posts, we have 2 subsets of recommended resources. The AIR stamp of approval is awarded only to posts scoring above a strict scoring cut-off of ≥30 points (out of 35 total), based on our scoring instrument. The other subset is for "Honorable Mention" posts. These posts have been flagged by and agreed upon by AIR Board members as worthwhile, accurate, unbiased, and appropriately referenced despite an average score.

Take the AIR Ortho Upper Extremity Quiz at ALiEMU

Interested in taking the AIR quiz for fun or asynchronous (Individualized Interactive Instruction) credit? Please go to the above link. You will need to create a free, 1-time login account.

Highlighted Quality Posts: Ortho Upper Extremity Emergencies

Site Article Author Date Label
EMDocs Finger Amputation Christopher J. Nelson, MD 21 May 2022 AIR
ALiEM Point Tender Justine Ko, MD; M. Terese Whipple, MD; Alexander J. Tomesch, MD 23 May 2022 HM
Peds EM Morsels Nail Bed Lacerations Christyn Magill, MD 3 Sep 2021 HM

(AIR = Approved Instructional Resource; HM = Honorable Mention)

If you have any questions or comments on the AIR series, or this AIR module, please contact us! More in-depth information regarding the Social Media Index.


Thank you to the Society of Academic Emergency Medicine (SAEM) and the Council of EM Residency Directors (CORD) for jointly sponsoring the AIR Series! We are thrilled to partner with both on shaping the future of medical education.

ALiEM AIR Series | Cutaneous 2022 Module


Welcome to the AIR Cutaneous Module! After carefully reviewing all relevant posts from the top 50 sites of the Social Media Index, the ALiEM AIR Team is proud to present the highest quality online content related to related to cutaneous emergencies in the Emergency Department. 6 blog posts met our standard of online excellence and were curated and approved for residency training by the AIR Series Board. We identified 0 AIR and 6 Honorable Mentions. We recommend programs give 3 hours (about 30 minutes per article) of III credit for this module.

AIR Stamp of Approval and Honorable Mentions

In an effort to truly emphasize the highest quality posts, we have 2 subsets of recommended resources. The AIR stamp of approval is awarded only to posts scoring above a strict scoring cut-off of ≥30 points (out of 35 total), based on our scoring instrument. The other subset is for "Honorable Mention" posts. These posts have been flagged by and agreed upon by AIR Board members as worthwhile, accurate, unbiased, and appropriately referenced despite an average score.

Take the AIR Cutaneous Quiz at ALiEMU

Interested in taking the AIR quiz for fun or asynchronous (Individualized Interactive Instruction) credit? Please go to the above link. You will need to create a free, 1-time login account.

Highlighted Quality Posts: Cutaneous Emergencies

Site Article Author Date Label
EMDocs Tattoo related complications in the ED Nathan LaDeaux, MD and Benjamin Schnapp, MD 5/9/22 HM
EMDocs EM@3AM: Herpes Zoster Elizabeth Adams, MD and Samuel Parnell, MD 3/26/22 HM
RCEM Learning Burns Jonathan Matthews, Rajan Atwal 11/02/21 HM
RCEM Learning Common Childhood Exanthems Maya Naravi 7/6/21 HM
EMCrit Anaphylaxis  Josh Farkas, MD 8/5/21 HM
Peds EM Morsels Pediatric Ramsay Hunt Syndrome Sean Fox, MD 6/17/22 HM

(AIR = Approved Instructional Resource; HM = Honorable Mention)


If you have any questions or comments on the AIR series, or this AIR module, please contact us! More in-depth information regarding the Social Media Index.


Thank you to the Society of Academic Emergency Medicine (SAEM) and the Council of EM Residency Directors (CORD) for jointly sponsoring the AIR Series! We are thrilled to partner with both on shaping the future of medical education.

SAEM Clinical Images Series: An Ominous Umbilical Lesion

umbilical

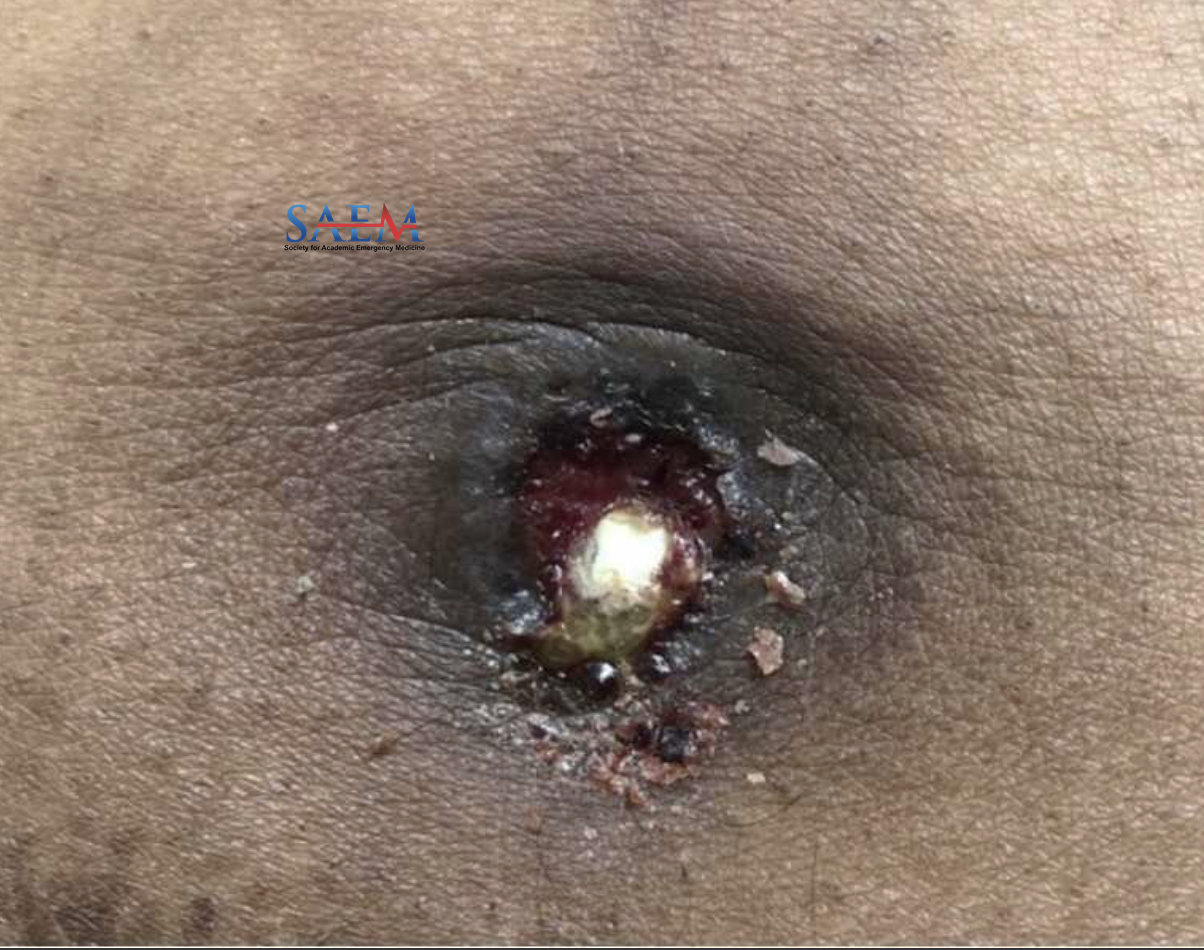
A 54-year-old male with a past medical history of atrial flutter and alcohol use disorder presents with an umbilical wound that has been bothering him for approximately six months. There is no history of trauma, prior infection, or umbilical surgery. There is intermittent mild pain and irritation that occurs randomly. No drainage or bleeding. He admits to picking at the wound regularly. He denies fever, chills, nausea, generalized abdominal pain, diarrhea, constipation, dysuria, and hematuria. The patient drinks four or more alcoholic beverages daily and has a long-standing history of tobacco use.


Vitals: BP 105/73; HR 70; RR 16; SpO2 97% on room air; Temp 36.1°C

Constitutional: Appears stated age, resting comfortably, well-appearing.

Abdominal: Soft, flat, non-tender.

Skin: Umbilical wound characterized by a peripheral eschar and a central area of hyperpigmented and crusted tissue overlying an area of whiteish moist tissue that was uncovered by gentle cleansing. No surrounding erythema and no areas of fluctuance. No active drainage or malodor.

None available.

Sister Mary Joseph (SMJ) nodule is a rare cutaneous metastasis of gastrointestinal or genitourinary primary malignancies to the umbilicus [1,3]. They are typically firm, painful, indurated, and irregularly shaped, with sizes typically less than 2 cm [1]. They can be ulcerated or necrotic with variable presence of discharge ranging from purulent to serous or serosanguinous [1]. Sister Mary Joseph nodules typically arise late in disease and portend a poor prognosis [1]. Most primary malignancies are adenocarcinomas (75%), and pancreatic cancers represent approximately 9% of umbilical metastases [1]. Mean survival of patients with SMJ nodules is less than 12 months, and less than three in those with pancreatic primaries [1]. Prognosis is slightly less bleak if the SMJ nodule is the only metastatic site [1]. Sister May Joseph Dempsey was a nun and surgical assistant to Dr. William Mayo, the surgeon who developed the approach to umbilical hernia repair and the first to identify the connection between abdominopelvic cancers and umbilical nodules [2,3].

Abdominal CT imaging.

Our patient was discharged on the initial visit with wound care instructions. He returned to the Emergency Department two months later and was admitted for atrial flutter with rapid ventricular response and acute on chronic congestive heart failure. During that visit, the patient had a CT chest/abdomen/pelvis that demonstrated likely a pancreatic tail adenocarcinoma with metastasis to the peritoneal and abdominal walls. The patient declined any further intervention.

Take-Home Points

  • Sister Mary Joseph nodules are umbilical metastases from abdominopelvic primary malignancies.
  • Recognition of their features on clinical exam can lead to a more rapid diagnosis.
  • Prognosis is grim with an average survival of less than one year.

  1. Vekariya P, Daneti DB, Senthamizh Selvan K, Verma SK, Hamide A, Mohan P. Sister Mary Joseph Nodule as an Initial Presentation of Pancreatic Adenocarcinoma. ACG Case Rep J. 2020 Aug 25;7(8):e00453. doi: 10.14309/crj.0000000000000453. PMID: 32903972; PMCID: PMC7447472.
  2. Palazzi DL, Brandt ML. Care of the umbilicus and management of umbilical disorders. UpToDate. Updated August 27, 2021. Accessed January 2, 2022. https://www.uptodate.com/contents/care-of-the-umbilicus-and-management-of-umbilical-disorders?search=sister%20mary%20joseph%20nodule&source=search_result&selectedTitle=2~6&usage_type=default&display_rank=2#H25.
  3. Tso S, Brockley J, Recica H, Ilchyshyn A. Sister Mary Joseph’s nodule: an unusual but important physical finding characteristic of widespread internal malignancy. Br J Gen Pract. 2013 Oct;63(615):551-2. doi: 10.3399/bjgp13X673900. PMID: 24152477; PMCID: PMC3782795.

SAEM Clinical Images Series: Dermatology Deserving a Deeper Dive

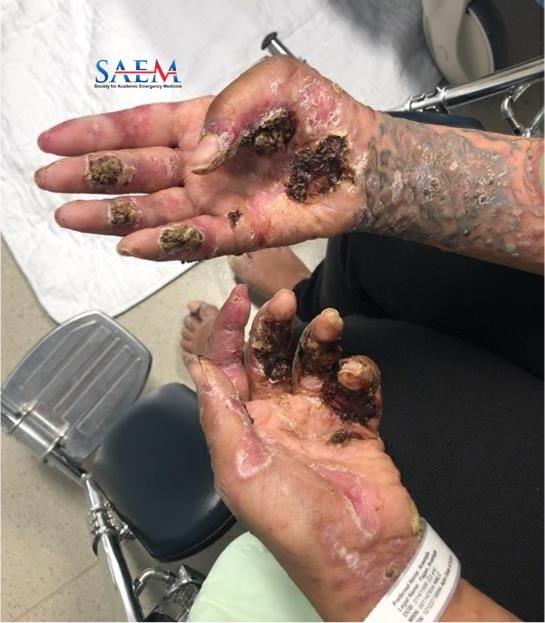
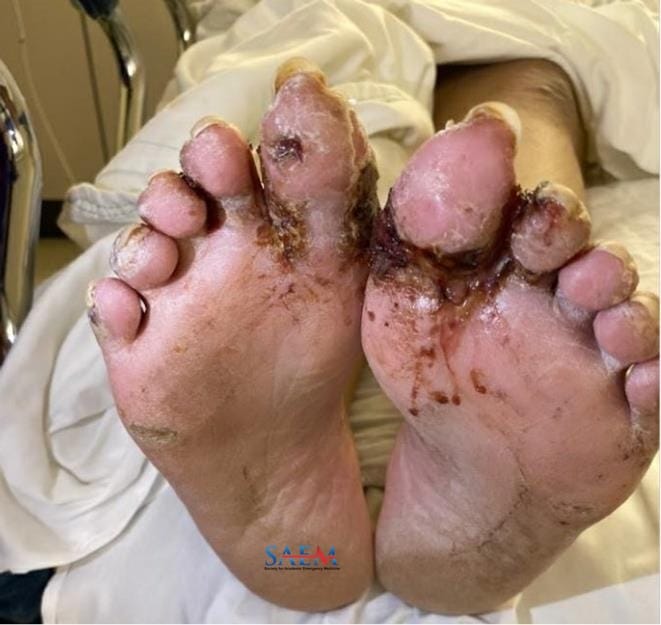
A 22-year-old female without significant past medical history presented to the Emergency Department (ED) for a progressive rash for the past six months. She had initially complained of dry and peeling skin on bilateral hands and feet and had multiple ED and dermatology encounters where topical steroids, acyclovir, and methotrexate were prescribed with no improvement. The rash continued to progress with worsening pain and inability to flex fingers secondary to lesions and scabbing at the joints. The patient also developed painful sores in her mouth primarily involving the tongue. More concerningly, she had lost 60 pounds since the onset of the rash and mouth lesions which she attributed to the inability to eat due to significant pain. Otherwise, she denied systemic symptoms, exposures, new medications, or previous illnesses.

Vitals: Within normal limits

HEENT: Swelling, erythema, and mild desquamation of the tongue mucosa with adherent white discharge present. Lesions are limited to the surface of the tongue with no buccal involvement.

Cardiovascular/Respiratory: Heart sounds within normal limits. Bilateral breath sounds without wheezes, rales, or rhonchi.

Abdomen: Soft, non-tender and non-distended.

Skin: The patient was noted to have desquamated, scabbing and oozing lesions on bilateral palms and fingers, soles of the feet, and web spaces between toes. The patient had no observable vesicles/bullae, or target lesions. Negative Nikolsky sign.

Complete Blood Count (CBC): Mild anemia, stable from baseline.

Basic Metabolic Panel (BMP): Within normal limits.

CT Abdomen/Pelvis with contrast (relevant findings only): Large solid right retroperitoneal mass lobulated in contour with heavy coarse calcifications measuring 21.2 x 8.5 x 10.4 cm, traversing the right hemidiaphragm and extending to the right lower mediastinum. The diaphragm itself is asymmetrically thickened as compared with the contralateral left side with a small volume of adjacent retroperitoneal fluid and there is extension into the right neural foramina.

The diagnosis of paraneoplastic pemphigus (PNP) was made after skin biopsy along with the constellation of findings including desquamating cutaneous lesions, painful mucosal erosions, and large retroperitoneal mass concerning for malignancy. Skin biopsy findings in this case include a distinct suprabasilar cleft, apoptotic keratinocytes, eosinophilic spongiosis, and superficial perivascular lymphocytic infiltrate with scattered eosinophils. Focally, there was full-thickness necrosis of the epidermis and dermis.

Patients with concern for PNP without known malignancy require a full neoplastic workup. In this case, a biopsy of the retroperitoneal mass and subsequently full resection was notable for Castleman’s disease, a rare lymphoproliferative disorder. PNP is an often fatal paraneoplastic mucocutaneous blistering disease that is most commonly caused by various lymphoproliferative disorders including non-Hodgkin’s lymphoma, chronic lymphocytic leukemia (CLL), and Castleman’s disease. It is an extremely rare condition with an unknown incidence rate. The mucosal erosions present are a requirement for the diagnosis. It typically presents as an erosive stomatitis involving the tongue and is characteristically chronic, progressive, and painful. These lesions are the initial disease manifestation in almost one-half of patients with PNP and often lead to malnutrition secondary to pain with attempts at oral intake. The cutaneous lesions in the disease are widely variable in morphology and can present with tense or flaccid bullae, as well as inflammatory papules or plaques.

Take-Home Points

  • In patients with a progressive rash involving the oral mucosa that have failed multiple outpatient regimens and have findings concerning for possible systemic involvement, dermatology consultation, tissue biopsy, and body imaging are often needed to confirm a diagnosis of complicated disease processes such as paraneoplastic pemphigus (PNP).
  • Significant unintentional weight loss may be due to a variety of reasons stemming from one unifying etiology. In this case, our patient had both mouth pain limiting oral intake as well as a lymphoproliferative disorder.
  • Anhalt GJ, Kim SC, Stanley JR, Korman NJ, Jabs DA, Kory M, Izumi H, Ratrie H 3rd, Mutasim D, Ariss-Abdo L, et al. Paraneoplastic pemphigus. An autoimmune mucocutaneous disease associated with neoplasia. N Engl J Med. 1990 Dec 20;323(25):1729-35. doi: 10.1056/NEJM199012203232503. PMID: 2247105.
  • Kaplan I, Hodak E, Ackerman L, Mimouni D, Anhalt GJ, Calderon S. Neoplasms associated with paraneoplastic pemphigus: a review with emphasis on non-hematologic malignancy and oral mucosal manifestations. Oral Oncol. 2004 Jul;40(6):553-62. doi: 10.1016/j.oraloncology.2003.09.020. PMID: 15063382.

By |2023-01-02T04:44:30-08:00Jan 2, 2023|Dermatology, Heme-Oncology, SAEM Clinical Images|
Go to Top