


Fentanyl: Adding Fuel to the Fire in the North American Opioid Epidemic
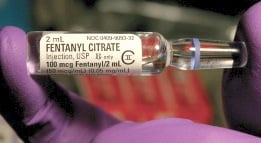 Drug poisoning is now the leading cause of injury death in the United States,1 with opioids accounting for up to 40% of these deaths. In the U.S., prescription opioid death rates have more than quadrupled since 1999, and death rates exceed those due to motor vehicle crashes.2 Similar trends in opioid exposure and death rates in Canada suggest that it is not far behind. Prescriptions for opioid analgesics paralleled a rise in opioid abuse and fatalities between 2002 and 2010, leveling off between 2011 and 2013,3 only to rise again in 2014.4 Among the more frequently misused opioids nationwide are oxycodone and hydrocodone (the most widely prescribed drug in the U.S.) in their various formulations, and methadone, but a “rising star” in the epidemic in many regions is fentanyl.
 We are proud to present CAPSULES module 5:
 Older adults are at high risk of poor outcomes from even minor head injuries. We see many older patients in the ED who present after a fall or head injury, and we have good decision rules for which patients need brain imaging.
 From 2002-2006, there were about 142,000 ED visits by older adults (age 65 and over) for TBIs, 81,500 hospitalizations, and over 14,300 deaths.

 What is the most commonly fractured carpal bone in adults? It’s the scaphoid bone. As a bonus it has the dreaded complication of avascular necrosis. So how good are the physical exam and imaging modalities in diagnosing a fracture? What is the likelihood ratio (LR) that snuffbox tenderness predicts a fracture? Bottom lines: The exam is highly sensitive but poorly specific, such that one can only confidently state that a NON-tender snuffbox and scaphoid tubercle essentially rule out an acute scaphoid fracture. Also negative x-rays for patients with scaphoid tenderness still yield a fracture post-test probability of 25%. This PV card breaks down all the LRs.