Video: Dr. Eric Mazur on peer teaching
“My lecturing was ineffective, despite the high evaluations.”
“The traditional approach to teaching reduces education to a transfer of information.”
– Dr. Eric Mazur
Dr. Eric Mazur is a Harvard Professor of Physics and Applied Physics who talks about his “confessions of a converted lecturer”. He focuses on the power of peer teaching and the ineffectiveness of the traditional lecture format in a classroom.
This talk is 72 minutes long. Take some time to listen and learn. Dr. Mazur is such an engaging talk that I couldn’t stop watching. Maybe it’s because he looks a little like the comedian Steve Carell.
Paucis Verbis: Methotrexate for ectopic pregnancy

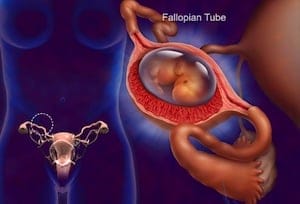
Ectopic pregnancies account for as many as 18% of patients who present with first-trimester bleeding or abdominal pain in the Emergency Department. This Paucis Verbis card summarizes the 2008 American College of Obstetricians and Gynecologists (ACOG) guidelines on the use of methotrexate (MTX) for ectopic pregnancies. Not all ectopic pregnancies require operative management.
What are the indications and contraindications to MTX? When should they follow up with their obstetrician?
Answer: In 4 days for a repeat b-HCG and possible second dose of MTX
Note that one of the eligibility criteria is that the patient must have an “unruptured ectopic pregnancy”. Many would consider that any ultrasonographic evidence of free fluid may be a sign of an early rupture. It is left up to clinician judgment in how “unruptured” is interpreted.
PV Card: Methotrexate for Ectopic Pregnancy
Adapted from [1]
Go to ALiEM (PV) Cards for more resources.
Reference
- ACOG Practice Bulletin No. 94: Medical Management of Ectopic Pregnancy. Obstetrics & Gynecology. 2008;111(6):1479-1485. doi: 10.1097/aog.0b013e31817d201e
Trick of the Trade: Ultrasound-guided injection for shoulder dislocation

Who loves relocating shoulder dislocations as much as I do? I know you do.
Often patients undergo procedural sedation in order to achieve adequate pain control and muscle relaxation. Alternatively or adjunctively, you can inject the shoulder joint with an anesthetic. Personally, I have had variable effectiveness with this technique. In cases of inadequate pain control, I always wonder if I was actually in the joint.
How can you improve your success rate in injecting into glenohumeral joint injection?
Paucis Verbis: Acetaminophen toxicity
Did you know that the American Association of Poison Control Centers reports that 10% of poison center calls are related to acetaminophen ingestions? That’s a lot. This Paucis Verbis card reviews the basics of acetaminophen toxicity. I included the Rumack Matthew nomogram to help you plot out the patient’s risk for hepatotoxicity.
In the Emergency Department, we often screen for acetaminophen toxicity for patients who may have ingested substances as a suicide attempt. We check the serum acetaminophen level 4 hours post-ingestion. Occasionally, we are surprised by a toxic level because in the first 24 hours, because symptoms are can be mild and nonspecific (abdominal pain, nausea, lethargy).
Rule of 150
- The toxic ingestion dose of acetaminophen is 150 mg/kg.
- The serum acetaminophen level when N-acetylcysteine treatment should be started is 150 mcg/mL (see Rumack Matthew nomogram)
- The starting IV dose of N-acetylcysteine is 150 mg/kg over 15 minutes.
PV Card: Acetaminophen Toxicity
Adapted from [1]
Go to ALiEM (PV) Cards for more resources.
Reference
- Larson A. Acetaminophen hepatotoxicity. Clin Liver Dis. 2007;11(3):525-48, vi. [PubMed]
Trick of the trade: Nebulized naloxone
Overdoses of long-acting opiates, such as oxycodone and methadone, are challenging to manage, especially if these patients are chronically on opiates.
On the one hand, you want to reverse some of the sedative effectives with naloxone so that they aren’t near-apneic and hypoxic. You also want to be able to take a history from them. On the other hand, you don’t want to abruptly withdraw them with naloxone such that they become violent and agitated. It is a fine balancing act.
Long-acting opiates present a separate challenging because naloxone wears off fairly quickly in 30-45 minutes. These patients may require repeat dosings and/or a naloxone IV drip.
(more…)
Paucis Verbis: Influenza – To treat or not to treat?

Influenza season typically peaks in the United States during the Jan-Feb months and can start as early as October. You can read about the 2011-12 seasonal flu data on the CDC website.
Should you give a patient with influenza an antiviral agent or just provide supportive therapy?
This Paucis Verbis card summaries the CDC’s Advisory Committee on Immunization Practices (ACIP) recommendations for this upcoming 2011-12 flu season. I also let patients with uncomplicated influenza who are going to be managed as outpatients know that a 5-day course of osteltamivir or zanamivir will cost them about $50-80. Often that sways them towards declining a prescription and “toughing out” an extra day of the flu.
PV Card: Influenza
Adapted from [1]
Go to ALiEM (PV) Cards for more resources.
Reference
- Centers for. Infectious disease. Antiviral agents for the treatment and chemoprophylaxis of influenza. Ann Emerg Med. 2011;58(3):299-303; discussion 303-4. [PubMed]