ACMT Toxicology Visual Pearl: The Bark with Some Bite

Which medication can be derived from the bark of the pictured tree?
- Aspirin
- Atropine
- Colchicine
- Quinine



Which medication can be derived from the bark of the pictured tree?

A 24-year-old female with no pertinent PMHx presents to the ED with a chief complaint of eye pain. She reported a 10-day history of worsening right eye pain following being punched in that eye. She had been managing her pain with ice and had not taken any OTC medications. Her mom convinced her to go to the ED and she first went to an outside hospital, but was referred to come to our institution. She endorsed photophobia and blurry vision but denied double vision. She further noted occasional left-sided headaches.
Vitals: Within normal limits
General: The patient is alert and conversant. No apparent distress.
HEENT: NC, AT. Mucous membranes moist. Neck supple. Minimal pain with EOM. No double vision in right eye. Right eye discoloration at superior portion. Divided abnormal pupil. Mild superior periorbital swelling. Visual acuity: Right – 20/400, Left – 20/25
CV: Regular rate and rhythm.
Resp: Clear to auscultation bilaterally.
Abd: Soft, non-tender, non-distended.
Neuro: Alert. Motor and sensation grossly intact.
MSK: Moves all extremities, no joint pain or tenderness.
Skin: No obvious rashes or skin lesions.
Non-contributory
This is traumatic iridodialysis. It is typically related to significant blunt trauma to the eye that pulls the iris away from the ciliary body at the scleral spur [1]. That is what causes the split appearance or “two pupil” phenomenon.

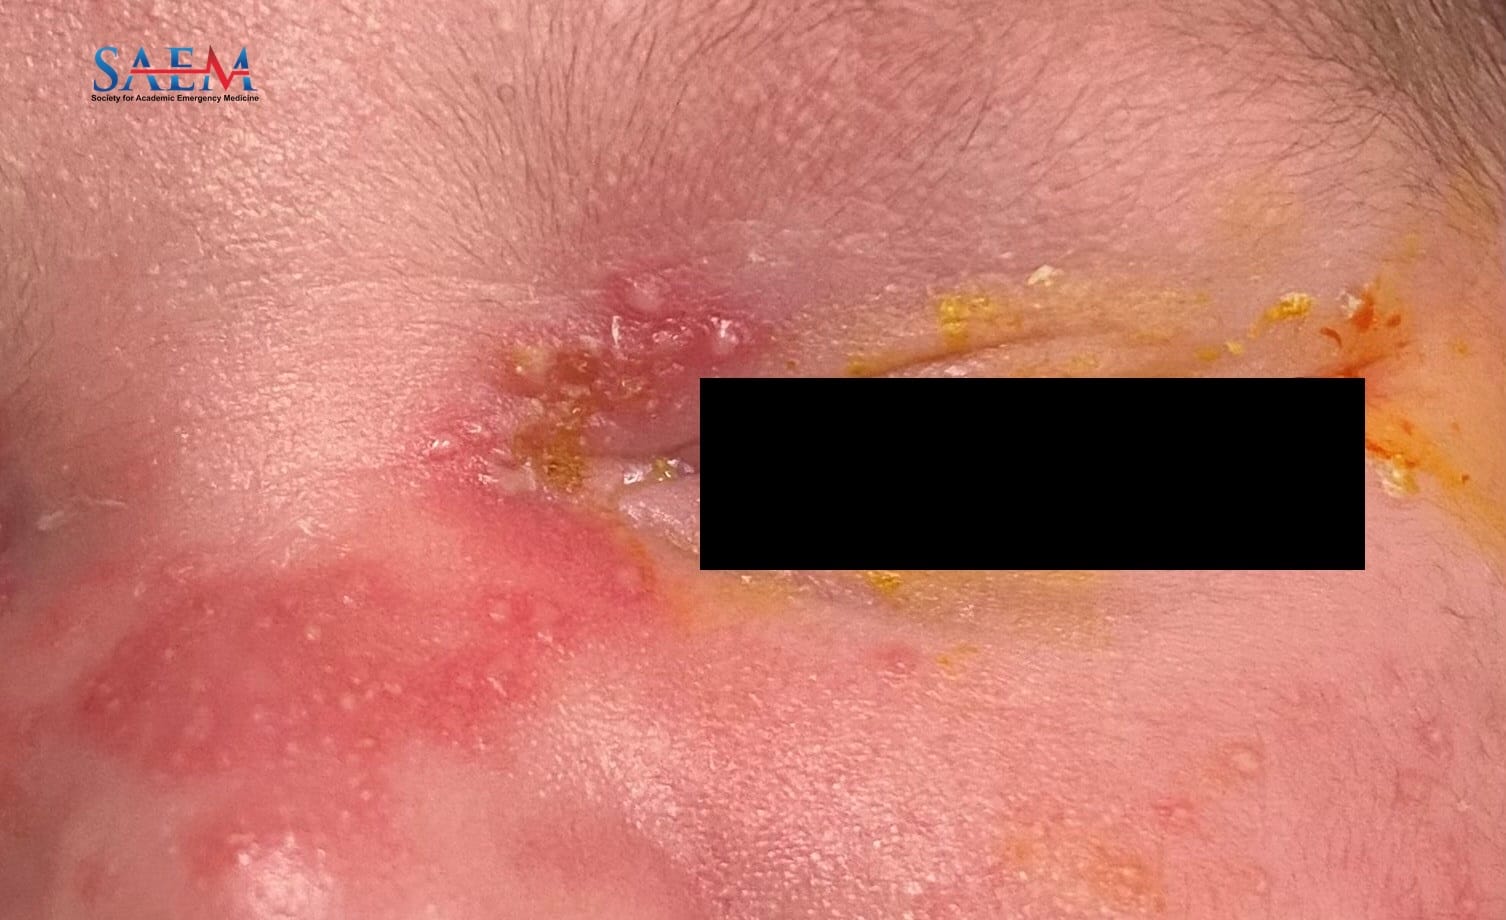
An 18-day-old male presented for a rash on his face for two days. The patient was born via spontaneous vaginal delivery full term without complications to a mom who has a history of genital HSV but without active lesions at delivery and on acyclovir. The patient presented with a vesicular rash on his face including around his eyes. He had conjunctival discharge noted by mom. Otherwise, he was well-appearing, acting normally, and eating/voiding/stooling normally.
General: Well appearing, acting appropriately for age
HEENT: Scalp normal. Anterior fontanelle soft and flat. Vesicular appearing rash with erythematous base in clusters noted around eyes, cheek, and chin. Fluorescein staining with corneal abrasion noted at 4 o’clock region on right eye, no dendritic pattern. Scant yellow discharge noted from left eye. TM normal bilaterally. Oropharynx clear.
Neuro: Normal tone, moving all extremities
Skin: Flaky skin, no rash noted elsewhere except as listed above (Photos taken after fluorescein)
CBC: Normal
LFTs: Normal
BMP: Unremarkable
CRP: Negative
Lab results for HSV were negative:
HSV 1 and 2 (chin): negative
HSV 1 and 2 (near eye): negative
HSV 1 and 2 (nose, mouth, rectum): negative
HSV 1 blood Igg: negative
HSV 2 blood Igg: positive (reflective of maternal antibody status)
What was once called “neonatal acne” now known as neonatal cephalic pustulosis is usually seen in the first three weeks of life. Usually, it appears as pustulo-papules on the face, around the eyes, on the cheeks, and chin. Some studies have suggested that neonatal cephalic pustulosis is caused by Malassezia species. As the rash is self-limiting, treatment is not necessary.
When a vesicular rash is in a neonate < 1 month and all over the face, consider benign neonatal pustular lesions such as neonatal cephalic pustulosis.
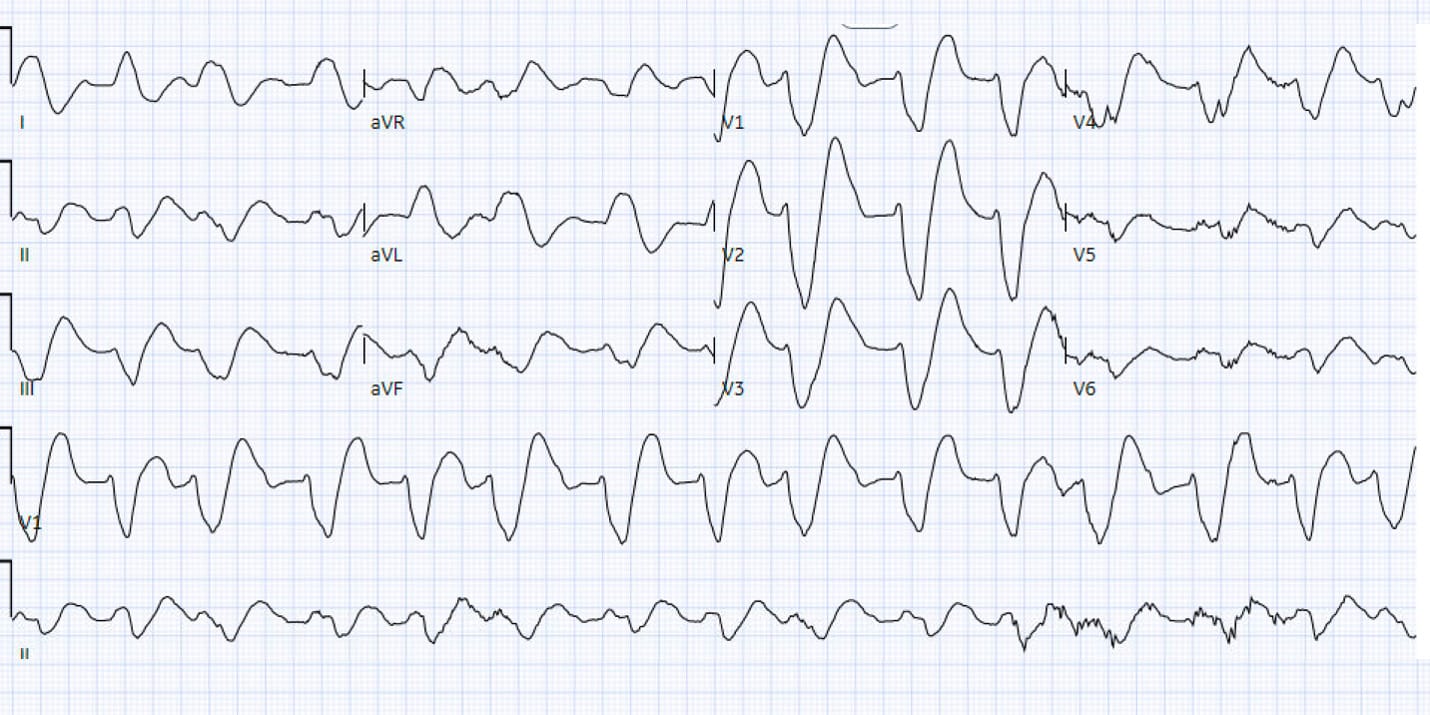
What agent would most likely be responsible for these ECG findings?
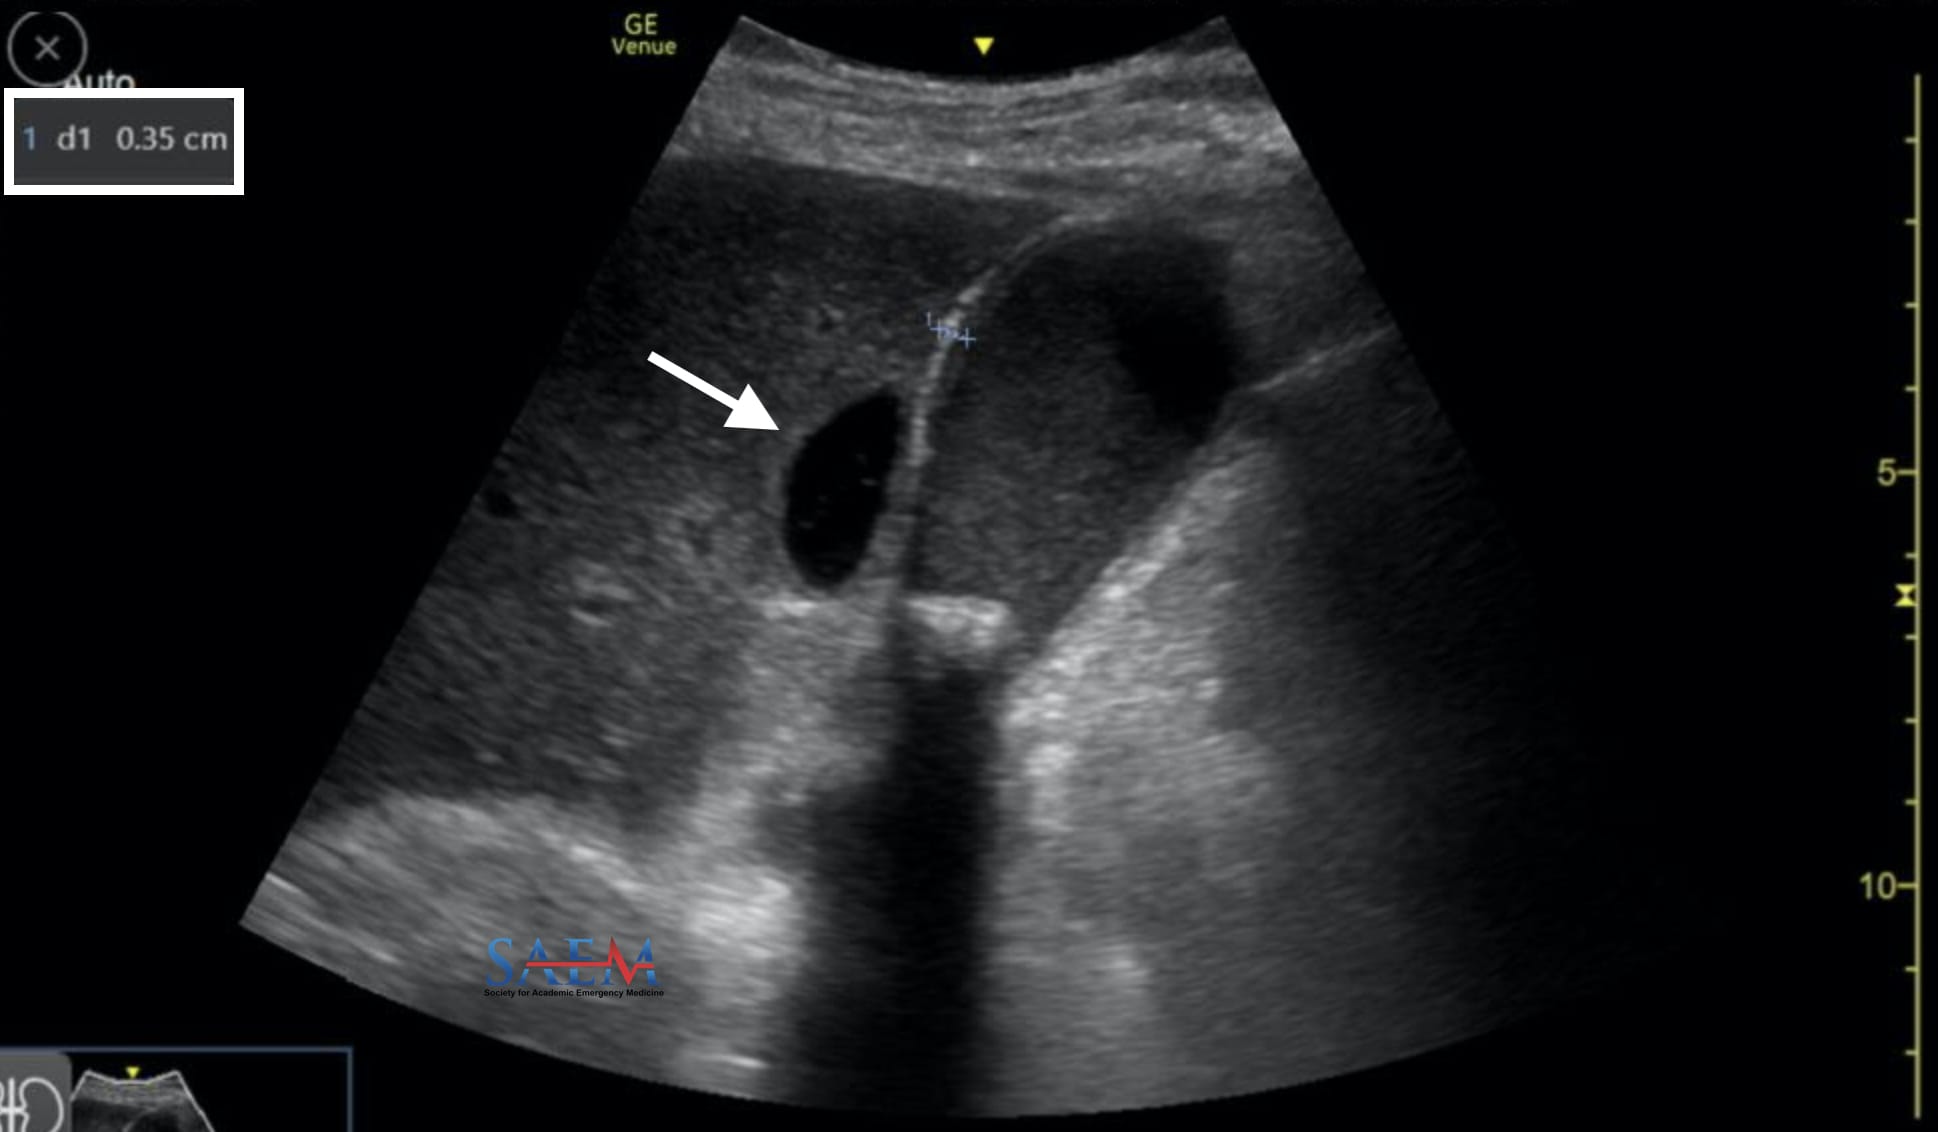
An 86-year-old man with a past medical history of coronary artery disease, hypertension, hyperlipidemia, chronic kidney disease, COPD, choledocholithiasis requiring ERCP and sphincterotomy 2 years ago presented with five days of feeling unwell. History was limited due to cognitive impairment. His daughter had reported to staff he had been feeling unwell for five days, intermittently having nausea and generalized abdominal pain, subjective fevers, chest pain, and shortness of breath. His daughter also reported a history of intermittent lower abdominal cramping which was chronic for him. He denied changes to urination or bowel movements.
Vitals: BP 106/67, Temp 36.2°C, Pulse 115, Resp 20, SpO2 95%
General: Nontoxic appearing, no distress
Heart: Regular, no murmurs
Lungs: Clear bilaterally, normal work of breathing
Abdomen: Diffusely tender, greatest in left upper quadrant
CBC with differential: WBC 14.1, Neutrophil 12% (high)
Comprehensive metabolic panel (CMP): Total bilirubin 2.7 (high), AlkP 328 (high), AST/ALT normal
Lipase: Normal
Troponin x2: Negative
Chest x-ray: No acute abnormality
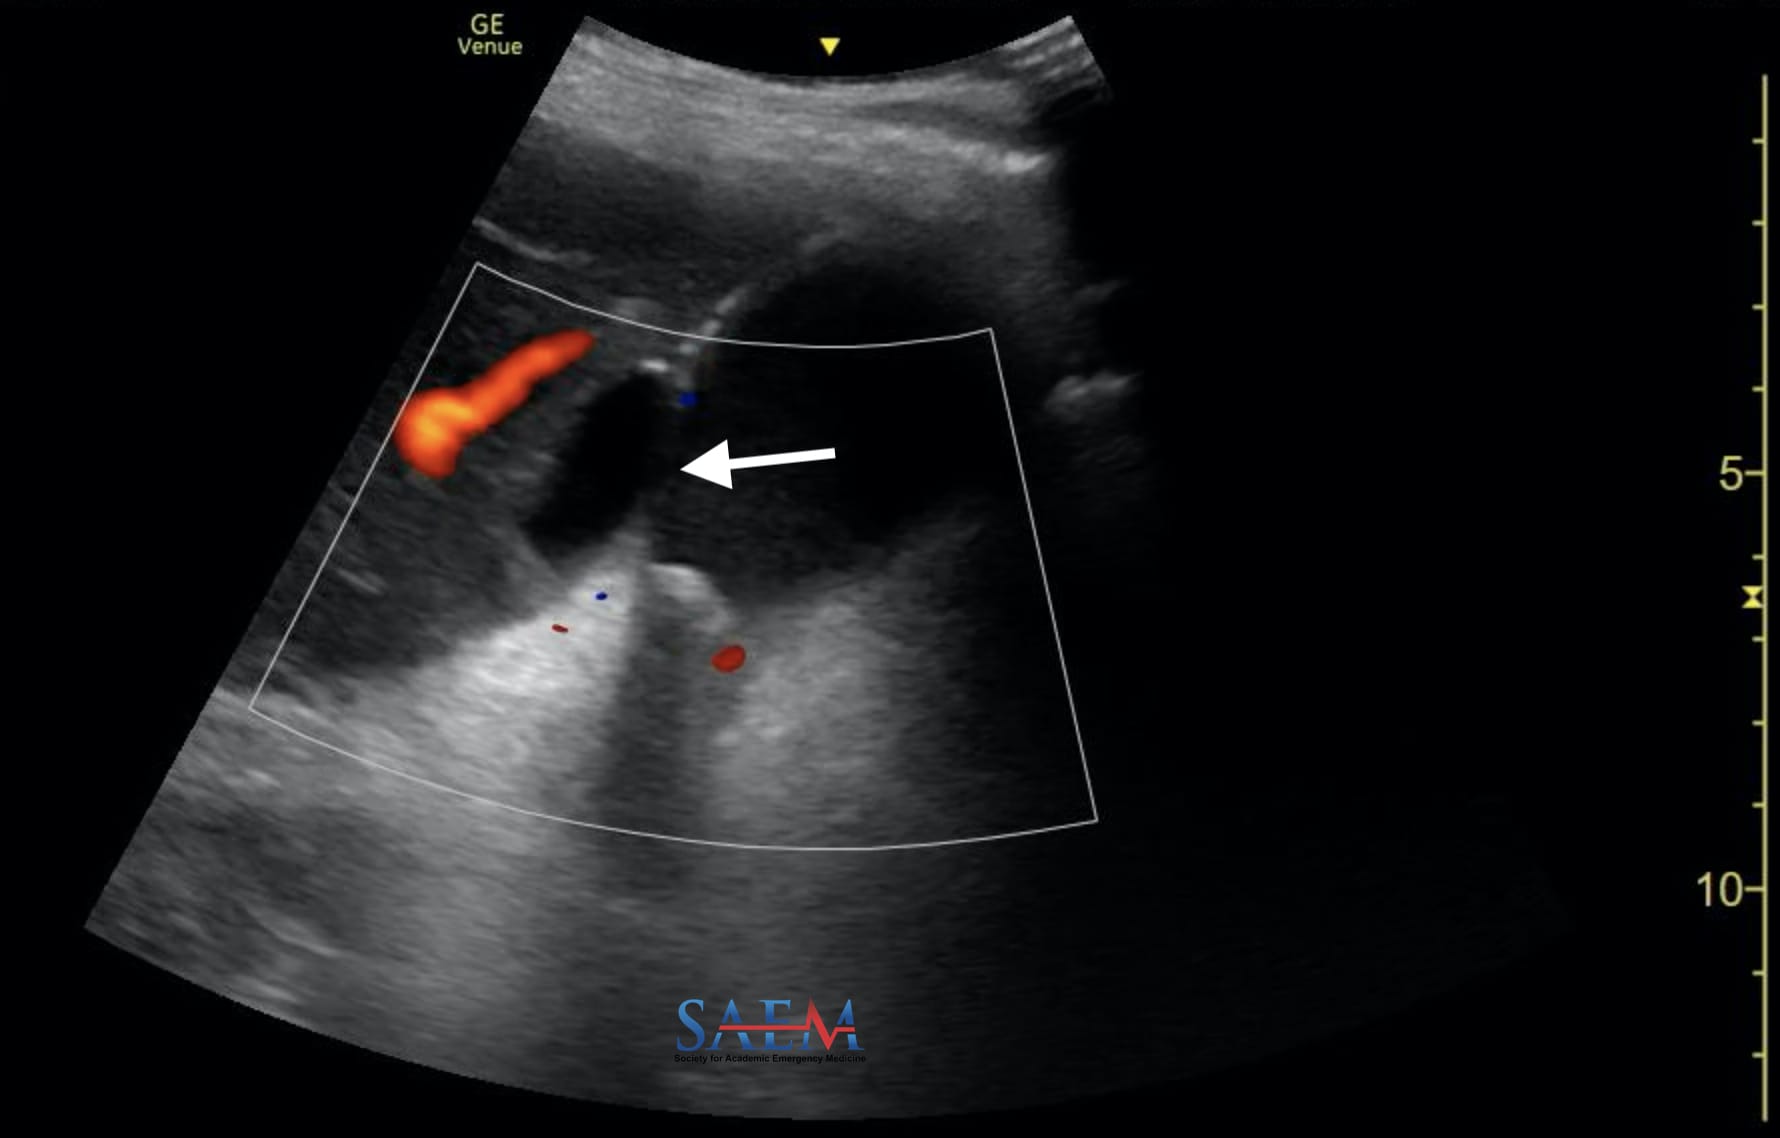
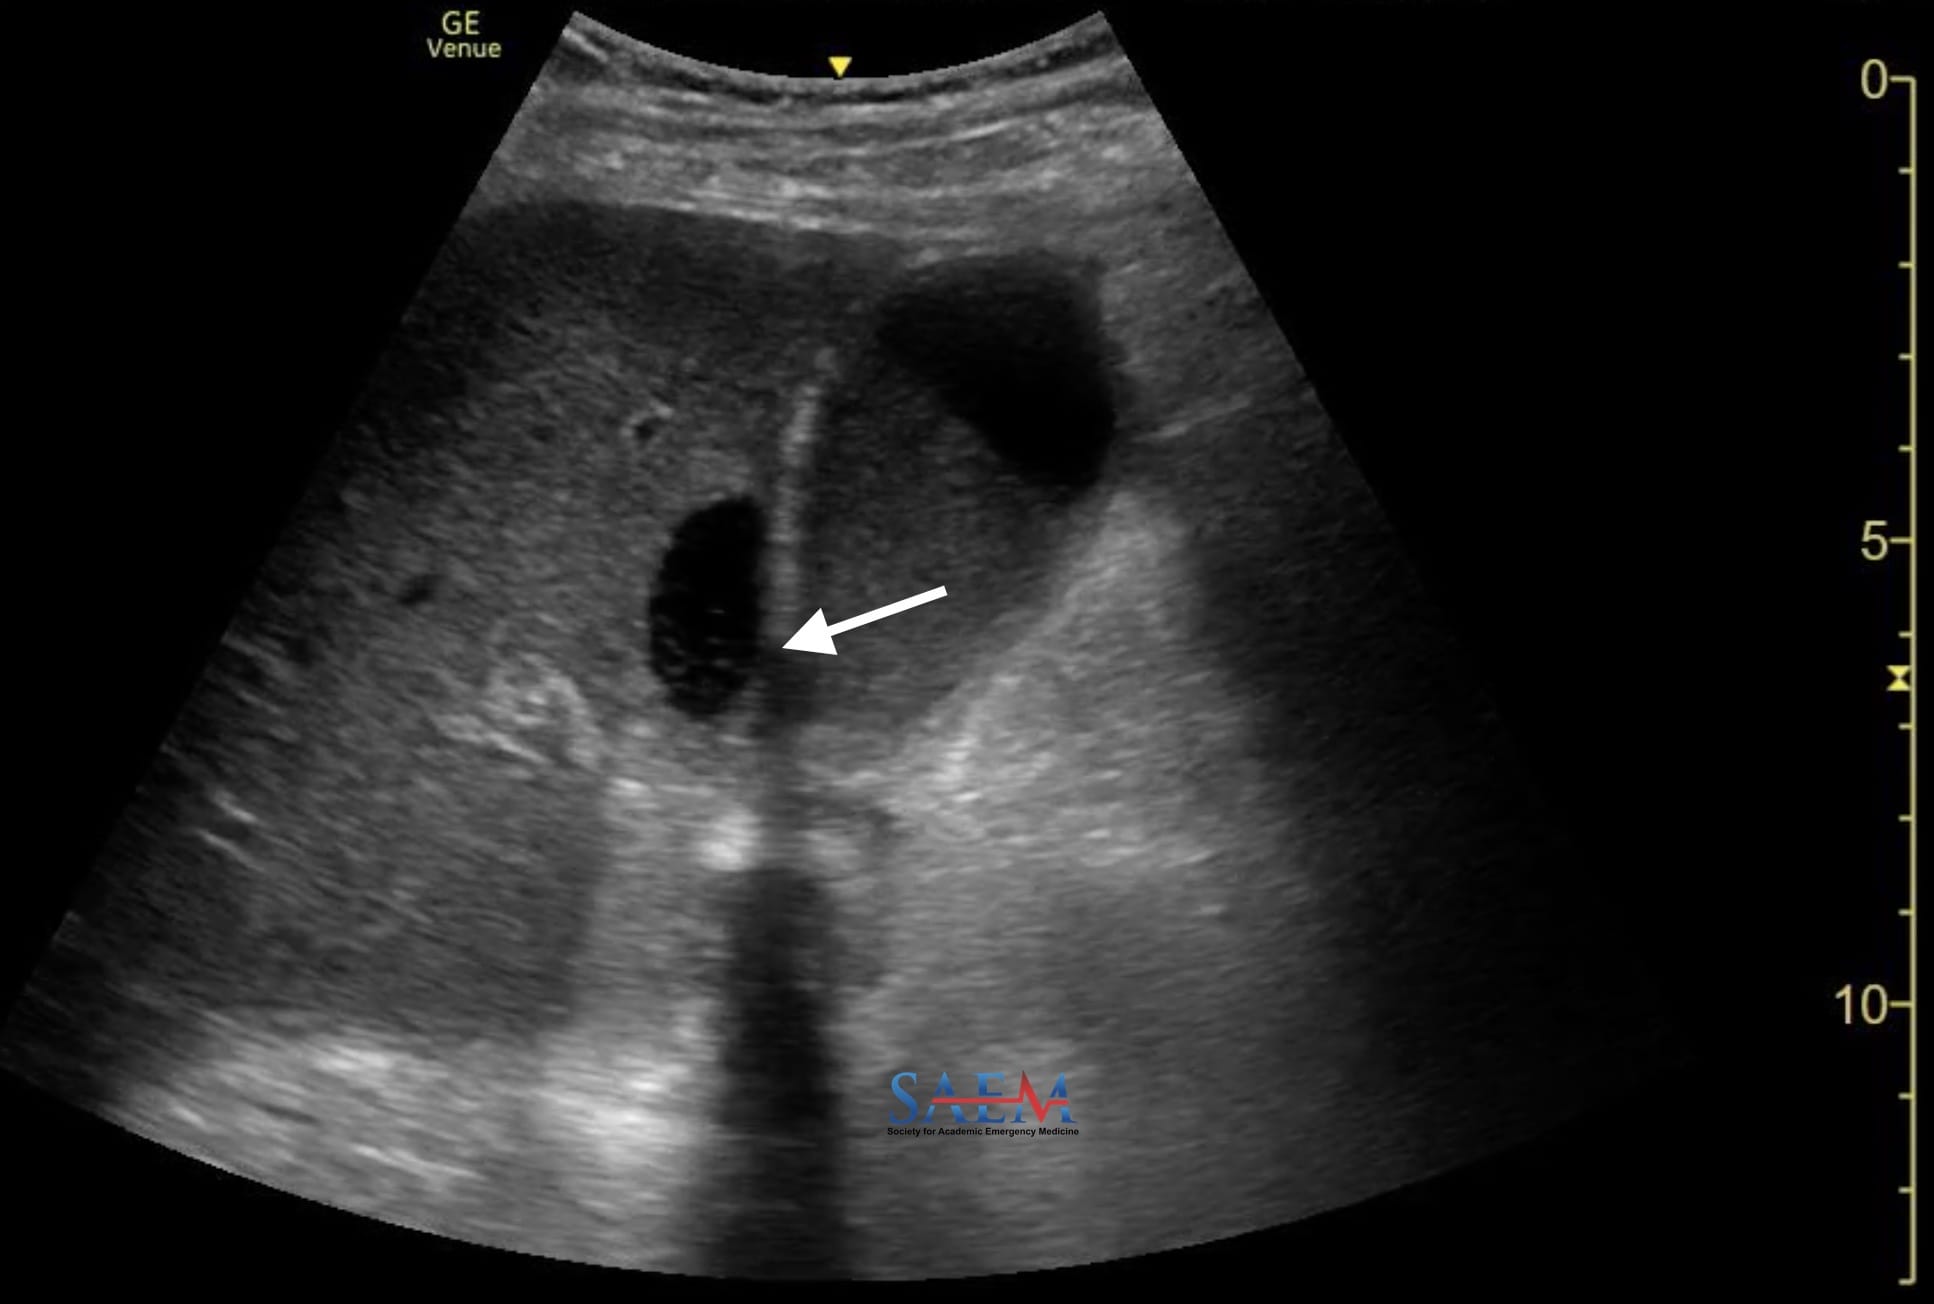
This patient has sonographic evidence of perforated gangrenous cholecystitis which was confirmed on subsequent CT scan. Gallbladder perforation is a complication of cholecystitis and has a reported incidence of 5-10%. It has been reported as early as two days after the onset of symptoms to as late as several weeks afterward. The most common site of perforation is the fundus due to relatively poor blood supply. In this case, the culprit perforation was in the proximal body adjacent to the stone which is suspected to have eroded through the wall.
Figure 1 depicts a minimally thickened gallbladder wall measured at 3.5 mm with a large shadowing stone-in-neck and associated perihepatic fluid collection (arrow) with a subtle intraluminal membrane and wall irregularity consistent with gangrenous cholecystitis. Figure 2 doppler images show no flow within the fluid collection and a suspiciously thin gallbladder wall (arrow). Figure 3 again highlights an irregular wall with small “hole sign” (arrow) signifying perforation of the gallbladder into the adjacent fluid collection. This patient was admitted to the hospital’s general surgical service and treated with IV broad-spectrum antibiotics and a percutaneous cholecystostomy tube placed by interventional radiology.
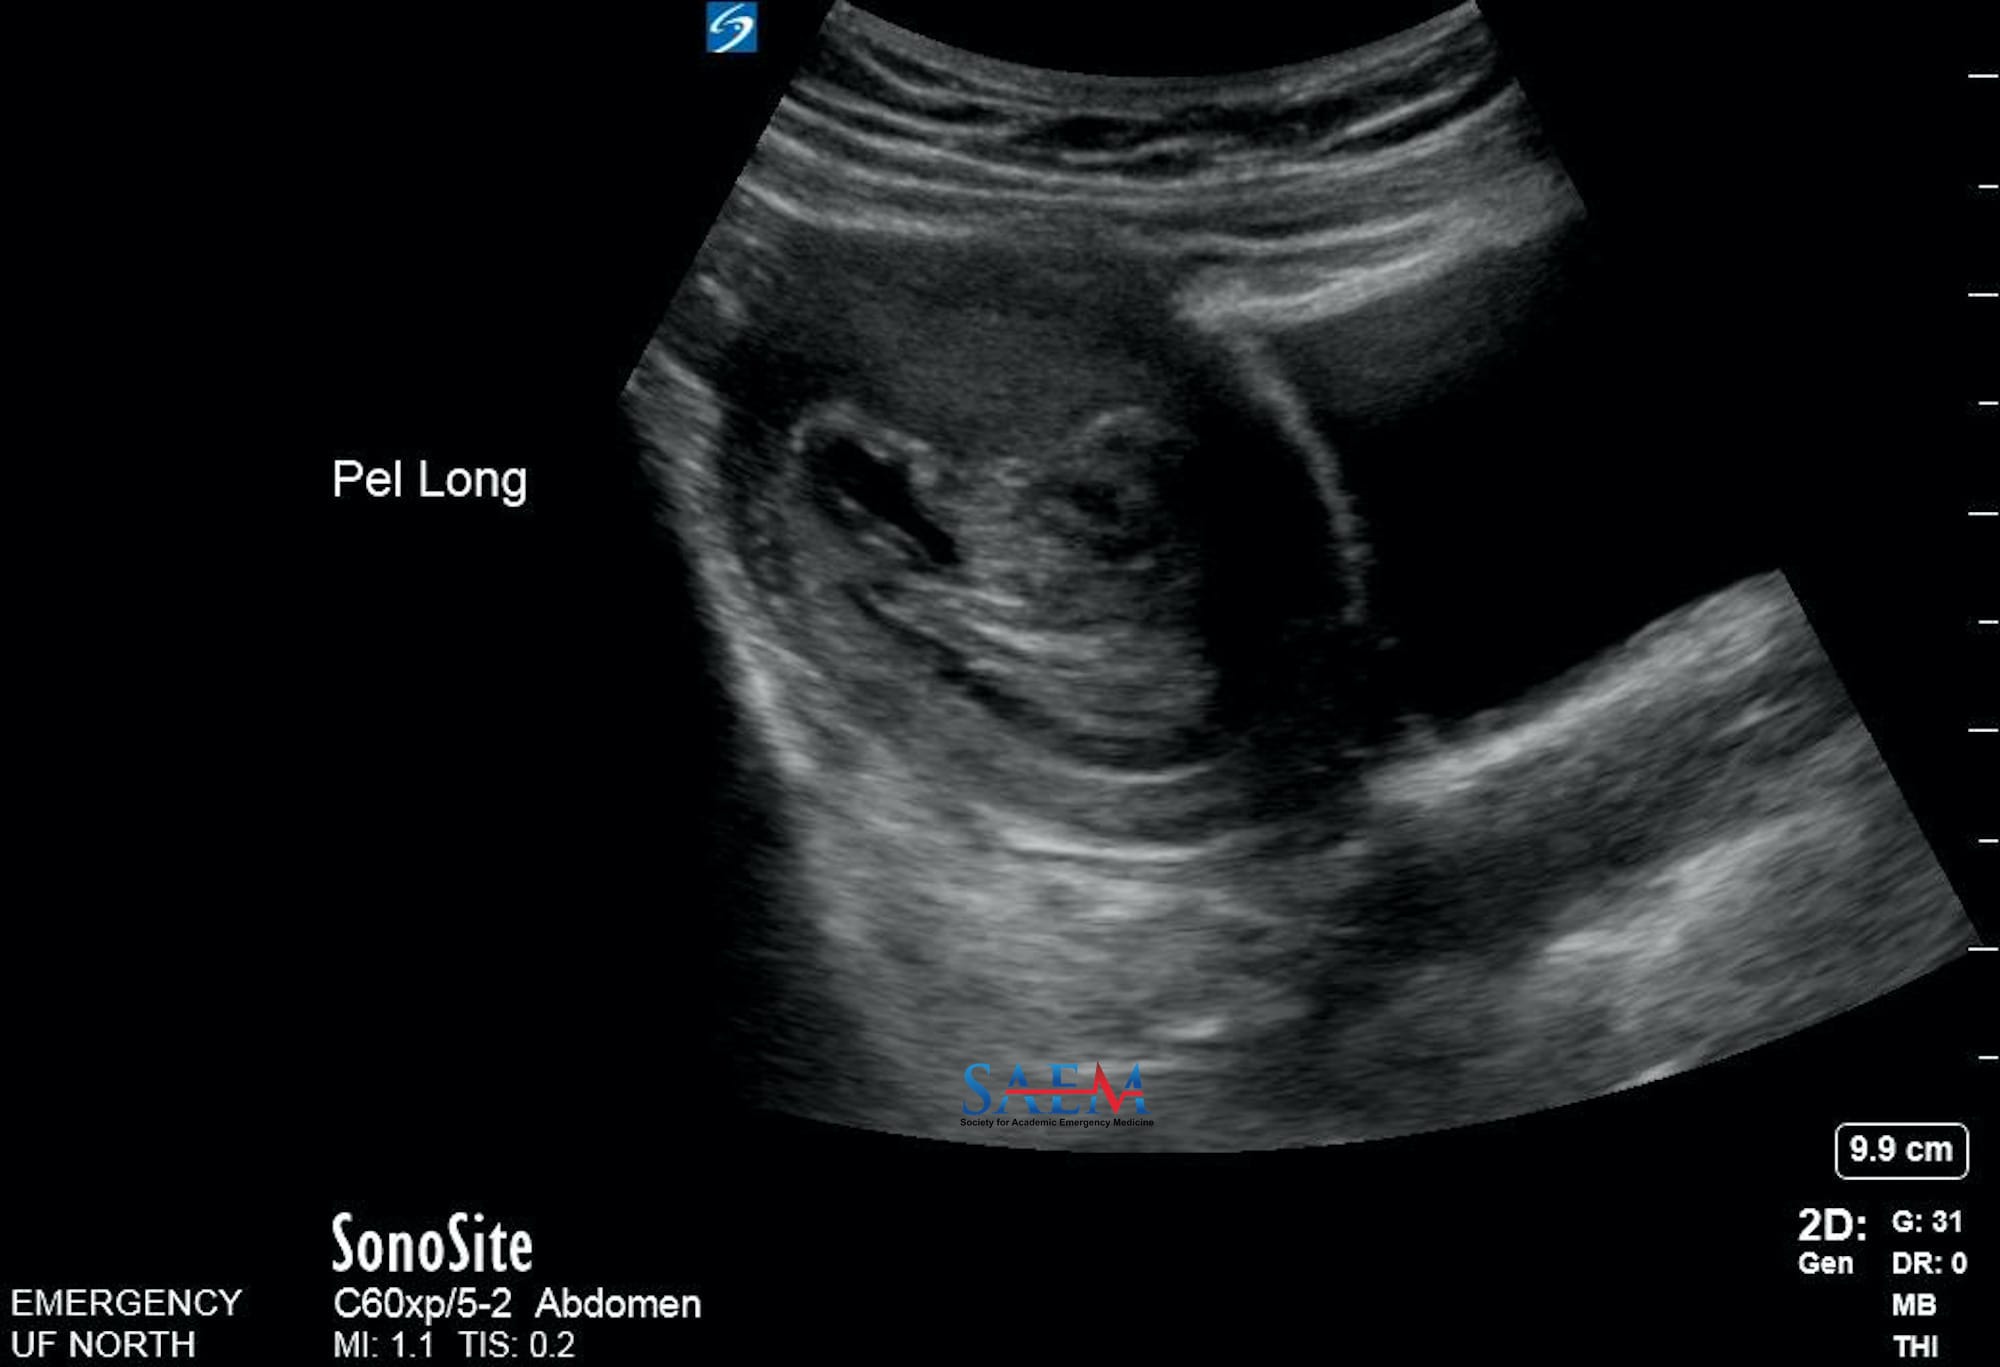
A 28-year-old female G3P2002 presented to the emergency department for one month of vaginal bleeding. The patient was seen in the emergency department one month earlier for vaginal bleeding in the first trimester of pregnancy. Her estimated gestational age was six weeks by last menstrual period. At the time her beta-hCG was 7225 mlU/mL with no intrauterine pregnancy demonstrated on transvaginal ultrasound. Three days later, the patient had declining b-hCG and transvaginal ultrasound again with no intrauterine pregnancy. The patient was discharged home with a diagnosis of miscarriage. Since discharge, she endorsed an initial slowing of vaginal bleeding but over the last two weeks bleeding had become heavier and continuous; soaking up to eight pads a day. She endorsed worsening nausea and vomiting over the past two weeks. She has been sexually active since her last encounter. She denied abdominal pain, pelvic pain, cramping, dizziness, shortness of breath, or fevers.
Vitals: BP 136/70; Pulse 96; Temp 97.8°F; Resp 16; SpO2 100%
Constitutional: No distress
Cardiovascular: Normal rate, regular rhythm, normal heart sounds
Abdomen: Soft and non-tender; Gravid uterus approximately 10 weeks
Pelvic exam: Active vaginal bleeding of dark red blood originating from the cervical os. Cervical os is closed and otherwise normal in appearance. Multiple clots are seen in the vaginal canal and posterior fornix. Vaginal canal and external genitals are normal in appearance.
Beta-HCG: 91,401 mlU/mL
Hemoglobin: 12.8 g/dL
Our patient’s case is convoluted by reporting a miscarriage the month prior, with declining beta-HCG and transvaginal ultrasounds with no intrauterine pregnancy. While her symptoms never fully resolved she endorsed that her vaginal bleeding slowed and only started getting worse after resuming intercourse.
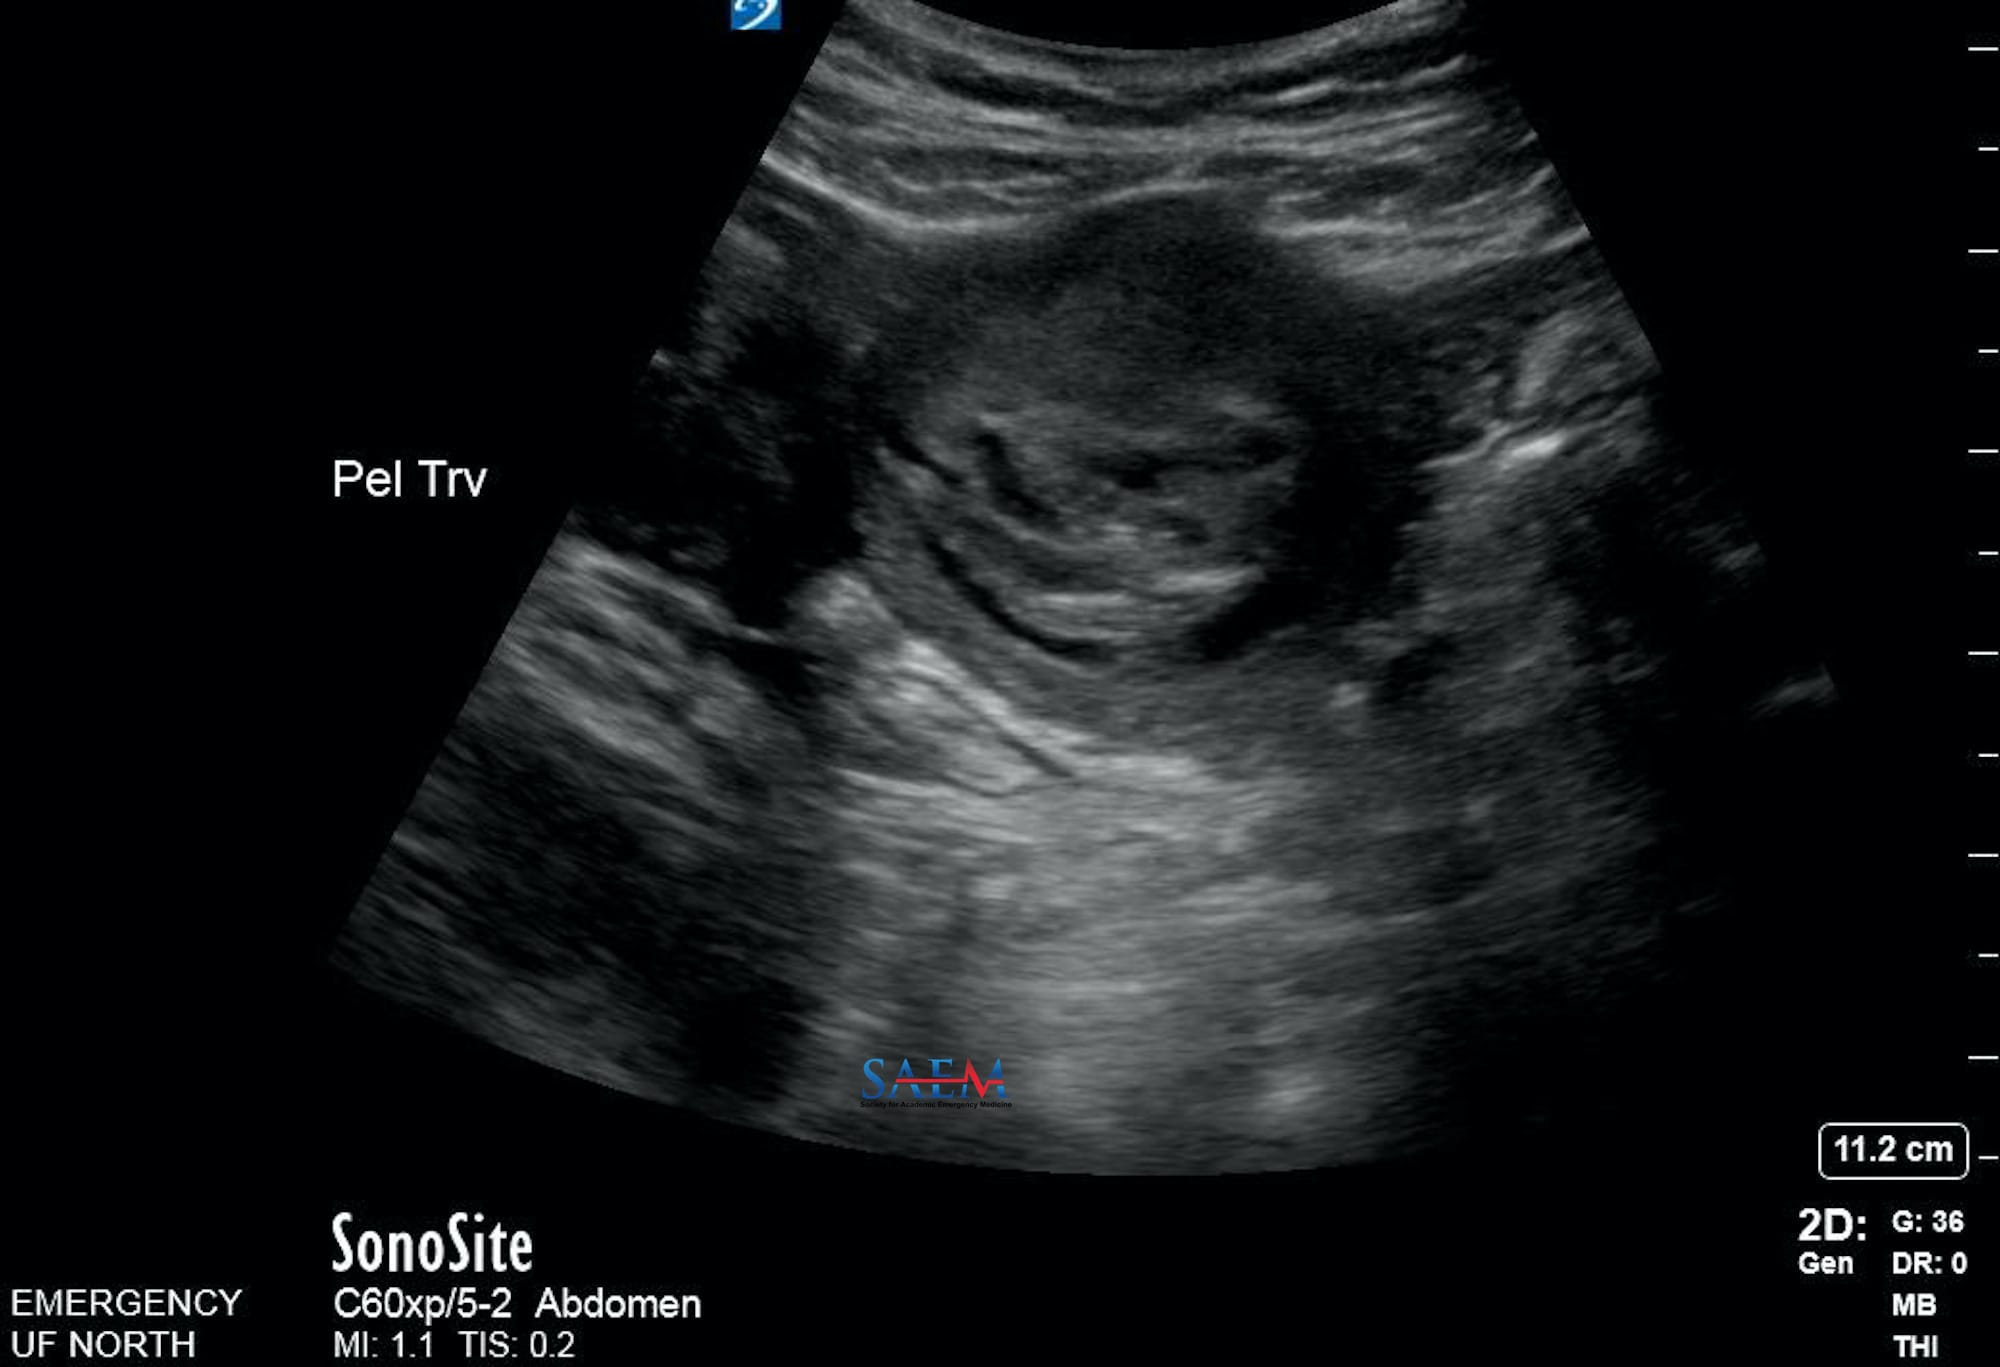
Her physical exam of a gravid uterus of approximately 10 weeks (despite reporting a miscarriage four weeks prior), persistent vaginal bleeding, and intractable nausea and vomiting are concerning for molar pregnancy [1]. Molar pregnancies typically present as abnormal uterine bleeding in the first or second trimester and are accompanied by symptoms of hyperemesis gravida secondary to the increase in beta-hCG [2]. The two main risk factors for gestational trophoblastic disease are the extremes of maternal age and prior molar pregnancy. However, there is an increased risk for molar pregnancy in patients with a history of prior spontaneous abortions and infertility [4]. Beta-hCG are typically greater than > 100,000 mlU/mL signifying excessive trophoblastic growth, however a value < 100,000 mlU/mL does not exclude the diagnosis of molar pregnancy as partial moles tend not to produce as much beta-HCG [3].
These images, taken by point of care ultrasound, show a heterogenic mass with mixed echogenicities within the uterine cavity consistent with gestational trophoblastic disease or molar pregnancy. Obstetrics and Gynecology was consulted for definitive management. The patient was taken to the operating room for dilation and curettage and was discharged the following day.
How do we best use high-sensitivity cardiac troponin (hs-cTn) to risk stratify patients with symptoms concerning for an acute myocardial infarction (AMI)? The 2022 American College of Cardiology (ACC) pathway provides timely guidance [1]. We help you translate this to your clinical practice, by illustrating with a case. Time to know your hs-cTn better.
Before delving into the specifics of the hs-cTn pathways, start with the ECG. The ACC 2022 pathway has a section dedicated to ECGs in ischemia [1], and FOAMcast has a great visual summary.
The 2022 ACC pathway [1] endorses clinical decision pathways that:
Examples of such pathways include [2]:
These clinical decision pathways take advantage of the diagnostic power of the delta hs-cTn value, resulting in higher sensitivity for AMI (99%) [3], more patients being able to be ruled-out for AMI [4], and more patients being discharged home with a shorter ED length of stay [5]. This contrasts traditional risk-stratification approaches, which compare hs-cTn values solely to the 99th percentile upper reference limit.
Let’s apply the ESC 2020 0/1 hour pathway [2], with some modifications based on the 2022 ACC guidelines [1]:
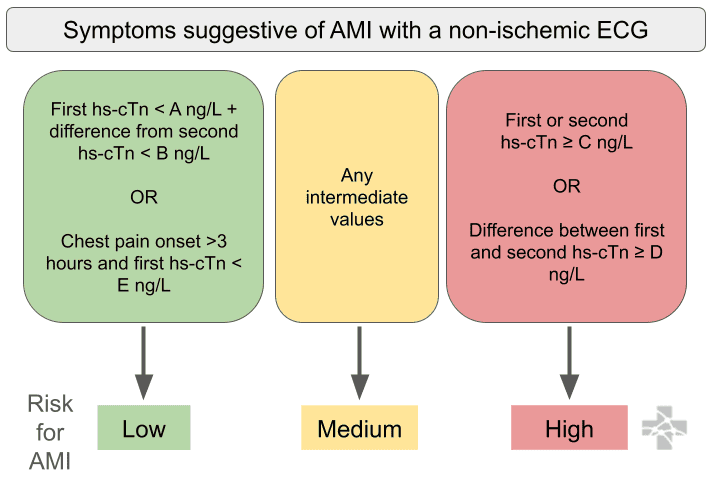
Figure 1. Stratification of patients for AMI based on high sensitivity troponin testing and the ESC 0/1 hour pathway (second hs-cTn drawn 1 hour after the initial hs-cTn test)
Notice how numbers are replaced with values A, B, C, D and E. That’s because these values are assay specific. You (or someone in your department) needs to know which assay your ED has, and use the appropriate values for that assay. Examples of cutoffs:
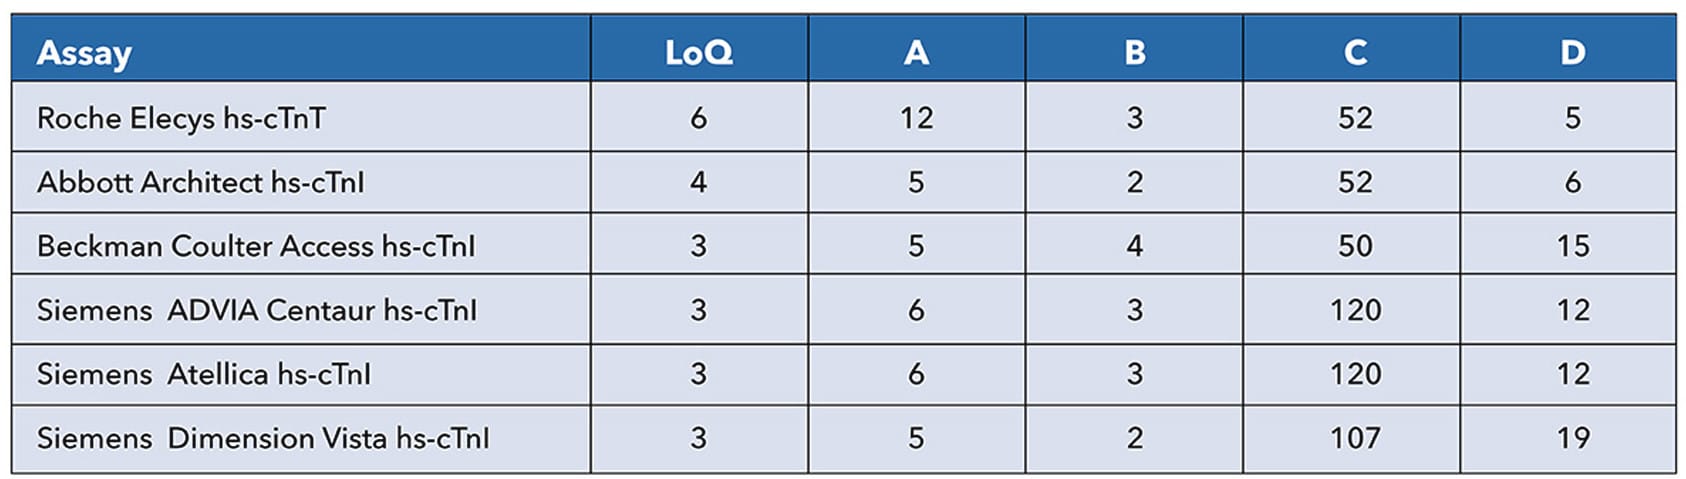
One concept that cuts across all assays is the limit of quantification (LoQ). That’s the lowest hs-cTn value that can be reliably reported as a number for that assay. In the risk stratification pathway (figure 1), value E is often the LoQ, or an optimized threshold slightly above the LoQ.
A 52-year-old woman presents with vague heaviness over the left side of the chest that does not radiate elsewhere. She does not recall clearly how it started, and it has been persistent for 5 hours. Its intensity does not change with walking or changes in posture. There are no associated symptoms such as diaphoresis, breathlessness, vomiting, fever, cough, or leg swelling.
She has hypertension and hyperlipidemia treated with lifestyle modification. She does not smoke. There is no family history of heart disease. She has no other recent illnesses or travel history.
On examination, her vital signs are normal. Heart sounds are dual with no murmurs and breath sounds are equal bilaterally. Pulses are well felt in all four limbs. There is no lower limb swelling or tenderness.
A 12-lead electrocardiogram (ECG) and chest x-ray (CXR) are unremarkable. The hs-cTn level on arrival is below the limit of quantification (LoQ).
High-risk category hs-cTn values in the ESC 2020 0/1 hour pathway or high STEACS pathway come in 2 types:
Those values are assay- and pathway-specific, so you’ll need to find out more about your local assay. These in the high-risk category are usually admitted to the hospital to assess for AMI as well as other causes of troponin elevation.
What if you have a patient with intermediate findings?
A 66-year-old man with hypertension, hyperlipidemia, diabetes mellitus, and chronic renal failure presents with poorly localized central chest discomfort while trying to sleep. It started 2 hours ago. The discomfort has a burning character, though he has never been diagnosed with reflux before.
His vital signs and physical exam are unremarkable other than an arteriovenous fistula on his left arm for hemodialysis. His ECG shows left ventricular hypertrophy.
The first hs-cTn results in the intermediate range on your assay-specific cutoff for the ESC 2020 pathway or high-STEACS pathway.
Featured image adapted from Adobe Firefly