



Paucis Verbis: Feedback card
Today's Paucis Verbis card is a little different. This card focuses on helping you give talking points when giving feedback to a learner on shift. This could be a medical student or resident. Dr. David Thompson (UCSF-San Francisco General Hospital) sent this great card to me and I thought it was too useful NOT to share. It's handy on shift, which ultimately is the purpose of these Paucis Verbis cards. These are useful especially for senior residents, who are supervising medical students and junior residents. This card can be used in many ways. For instance: Print these cards and fill [+]

Trick of the Trade: Bandaging the scalp laceration
Scalp lacerations are one of the most common injuries which present to the Emergency Department. Applying a dry bandage over the staples or sutures can be a challenge because the tape just has nothing to adhere to. We reviewed the use of tubular cotton gauze to create a beanie hat, but what should you do if you can’t find any tubular gauze? Ever since I wrote about the beanie hat trick, people in the ED have been using the tubular gauze more and we’re always out of stock whenever I look for it! [+]

Paucis Verbis: Acute vestibular syndrome and HINTS exam
What is your diagnostic approach to the acutely vertiginous patient? The bottom-line question is: Is the cause peripheral or central in etiology? In this great 2011 systematic review article in CMAJ on Acute Vestibular Syndrome (AVS), the authors review how (un)predictive elements of the history and physical exam are. By definition of AVS, symptoms must be continuous for at least 24 hours and have no focal neurologic deficits. Frighteningly, the authors report many of the signs and symptoms (type of dizziness, hearing loss, patterns of nystagmus, Hallpike-Dix) are not as predictive as we classically are taught! The take home point [+]
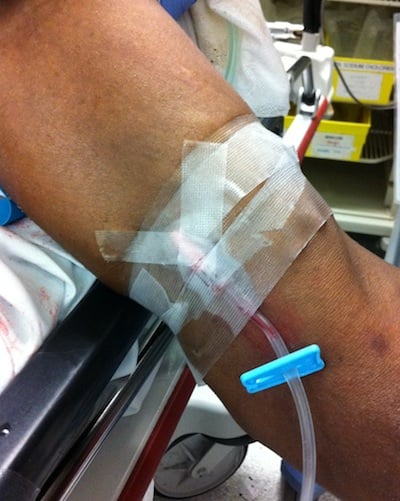
Trick of the Trade: Securing a peripheral IV on sweaty skin
Patients can become extremely diaphoretic with high fevers or if under the influence of PCP or a stimulant. Slippery, sweaty skin can pose a problem when securing peripheral IV’s. Adhesive tapes that are typically designed for securing these IV’s often slip off… immediately followed by the IV falling out. How can you secure the IV … without using staples and sutures? [+]
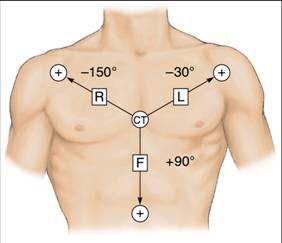
Paucis Verbis: aVR Lead on ECG
What lead is the most overlooked on the ECG? Answer: aVR Lead This lead can provide some unique insight into 5 different conditions: Acute MI Pericarditis Tricyclic antidepressant (TCA) and TCA-like overdose AVRT in narrow complex tachycardias Differentiating VT from SVT with aberrancy in wide complex tachycardias by using the Vereckei criteria (possibly better than Brugada criteria) PV Card: The aVR Lead on ECG Adapted from [1-4] Go to ALiEM (PV) Cards for more resources. See also: LifeInTheFastLane References Williamson K, Mattu A, Plautz C, Binder A, Brady W. Electrocardiographic applications of lead aVR. Am J Emerg Med. 2006;24(7):864-874. [+]
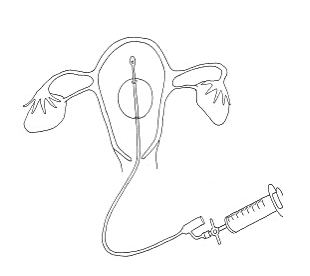
Trick of the trade: Foley catheter for DUB
Your next patient has heavy dysfunctional uterine bleeding (DUB). She is tachycardic and pre-syncopal. While you establish an IV, resuscitate her, and wait for the gynaecology team to arrive, is there any trick you can use to stem the bleeding? [+]
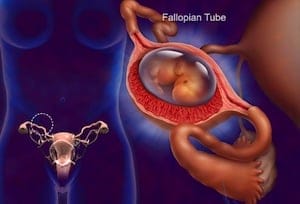
Paucis Verbis: Methotrexate for ectopic pregnancy
Ectopic pregnancies account for as many as 18% of patients who present with first-trimester bleeding or abdominal pain in the Emergency Department. This Paucis Verbis card summarizes the 2008 American College of Obstetricians and Gynecologists (ACOG) guidelines on the use of methotrexate (MTX) for ectopic pregnancies. Not all ectopic pregnancies require operative management. What are the indications and contraindications to MTX? When should they follow up with their obstetrician? Answer: In 4 days for a repeat b-HCG and possible second dose of MTX Note that one of the eligibility criteria is that the patient must have an "unruptured ectopic pregnancy". Many [+]

Trick of the Trade: Ultrasound-guided injection for shoulder dislocation
Who loves relocating shoulder dislocations as much as I do? I know you do. Often patients undergo procedural sedation in order to achieve adequate pain control and muscle relaxation. Alternatively or adjunctively, you can inject the shoulder joint with an anesthetic. Personally, I have had variable effectiveness with this technique. In cases of inadequate pain control, I always wonder if I was actually in the joint. How can you improve your success rate in injecting into glenohumeral joint injection? [+]

Paucis Verbis: Acetaminophen toxicity
Did you know that the American Association of Poison Control Centers reports that 10% of poison center calls are related to acetaminophen ingestions? That's a lot. This Paucis Verbis card reviews the basics of acetaminophen toxicity. I included the Rumack Matthew nomogram to help you plot out the patient's risk for hepatotoxicity. In the Emergency Department, we often screen for acetaminophen toxicity for patients who may have ingested substances as a suicide attempt. We check the serum acetaminophen level 4 hours post-ingestion. Occasionally, we are surprised by a toxic level because in the first 24 hours, because symptoms are can [+]
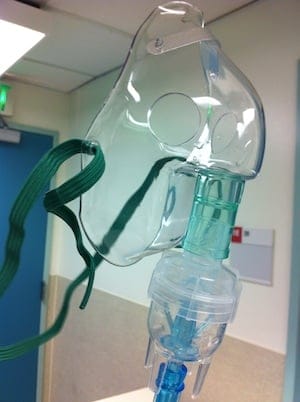
Trick of the trade: Nebulized naloxone
Overdoses of long-acting opiates, such as oxycodone and methadone, are challenging to manage, especially if these patients are chronically on opiates. On the one hand, you want to reverse some of the sedative effectives with naloxone so that they aren’t near-apneic and hypoxic. You also want to be able to take a history from them. On the other hand, you don’t want to abruptly withdraw them with naloxone such that they become violent and agitated. It is a fine balancing act. Long-acting opiates present a separate challenging because naloxone wears off fairly quickly in 30-45 minutes. [+]

Director of Growth, Strategic Alliance Initiative, Center for Innovation and Digital Health
Massachusetts General Hospital;
Chief Scientific Officer, Conductscience.com
Latest posts by Shuhan He, MD (see all)
- The Discharge Severity Index: Early Research on ED Readmission Risk Assessment - August 14, 2025
- Suboxone and the Emergency Physician: Get Waivered Training - August 12, 2022
- A Tale of Two Epidemics: COVID-19 and the Opioid Crisis - April 23, 2020