



Simulation Trick of the Trade: Bleeding Cricothyroidotomy Model
One advantage of simulation as an educational tool is the re-creation of cognitive and emotional stresses in caring for patients. Doing this for a high fidelity scenario is relatively easy – add additional patients, make a them loud, combative, or otherwise cantankerous, and add interruptions for good measure. However, when training for procedures in the simulation lab, we practice the procedure in isolation on a “task trainer” without cognitive and emotional stress for context. An off-the-shelf task trainer can do a superb job of teaching the mechanics of performing a procedure, but they lack complexity necessary to train for performing the procedure under stress. [+]
Transitions of Care: Top 10 things admitting providers wish we did for older adults
“Transitions of care” has become a hot topic in the care of older adults. It is usually applied to the transition from the hospital to home or the hospital to a nursing facility. But what about the transition from the ED to an inpatient service? It turns out there are plenty of things we could be doing (or not doing) to help smooth that transition and improve patient care. Here are some thoughts from admitting physicians with geriatrics training. [+]

Trick of the Trade: Nail Bed Repair With Tissue Adhesive Glue
Patients with fingertip injuries involving the nail bed typically present to the emergency department and require meticulous repair of the nail bed to prevent long-term cosmetic and functional disability. There are several methods to repair nail beds, typically involving absorbable suture, but maybe there is a faster way with similar cosmetic and functional outcomes. [+]

Ondansetron: Has it reduced need for IV rehydration in vomiting kids?
A 3-year-old male presents to the emergency department (ED) complaining of vomiting and diarrhea that has been occurring for 2 days. The mother states that the child has had fewer wet diapers today but has made tears when crying. On physical examination you note no rebound or guarding of the abdomen and determine that the child is moderately dehydrated. Your initial plan is to administer ondansetron and rehydrate the child orally. This is what you have been taught but is it actually efficacious? A just published 2014 JAMA Pediatrics article attempted to answer this question. [+]
Piperacillin/Tazobactam and Risk of Acute Kidney Injury with Vancomycin
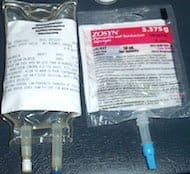
There are a few reasons why piperacillin/tazobactam (Zosyn) is not usually my first choice for a broad-spectrum gram-negative agent in the ED. First, at my institution, the Pseudomonas aeruginosa susceptibilities to pip-tazo are lower than that for cefepime. Second, pip-tazo does not have great CNS penetration, especially compared to ceftriaxone, cefepime, or even meropenem. Third, do we really need the anaerobic coverage that pip-tazo provides for every sick patient? Pip-tazo is great for empiric treatment of intra-abdominal and severe diabetic foot infections, but may not be needed for a hospital-acquired pneumonia. Fourth, with its frequent dosing (every 6 hours), too often the second dose is missed if the [+]

New Antibiotic Dalbavancin: Should we use this in the ED?
A new antibiotic will soon be approved for skin and soft tissue infections (SSTIs): dalbavancin. The company behind the drug will likely begin marketing heavily to emergency physicians as many patients with SSTIs seek care in the Emergency Department (ED). However, should we seriously consider dalbavancin as an addition to an ED’s arsenal against SSTIs and should it change our practice? [+]

Geriatric Emergency Departments: Coming to a Hospital Near You?
We are all familiar with the concept of pediatric EDs. We see them as medical students, we train in them as residents, and we work alongside pediatric EM fellows. It is generally clear what pediatric EDs have to offer: smaller sized beds and equipment, nurses trained in pediatric triage and assessment who know how to put IVs in babies and calm crying kids, and physicians with training in pediatric Emergency Medicine. But what about the other end of the age spectrum? Over the last 10 years geriatric EDs, also called Senior EDs, have been popping up around the country. You [+]

Deep Vein Thrombosis (DVT): Wells criteria and D-dimers happy together
You are evaluating a 45-year-old male who is complaining of calf pain. He has a history of cancer however he has never had a clot in the past. The leg is neither swollen nor warm but he notes a cramping sensation in the posterior portion of his calf. You are concerned for a deep vein thrombosis (DVT) and consider the multiple means to reliable exclude the diagnosis: Wells score, D-dimers, ultrasound? What works? [+]

Atypical Antipsychotic Medication Re-initiation in the ED
The acute episode of intoxication and agitation has subsided and your patient is calm. She has been medically cleared and is ready to be moved to a less acute, less monitored portion of the ED to await further assessment and treatment for her underlying psychiatric conditions. As a well-intentioned emergency medicine practitioner, you wish to give your patient the tools she needs to maintain this calm status by restarting her home atypical antipsychotic medication. What is the best way to go about doing this? While the atypical antipsychotics have generally been considered safer than the first generation agents due [+]

Trick of the Trade: Making your own homemade ultrasound gel
You are spending a month in rural Kenya, doing an ultrasound teaching course. Your enthusiastic participants have been ultrasounding every chance they get. Unfortunately, this has caused your ultrasound gel supplies to dwindle. It will be a month before a new shipment of gel arrives from Nairobi. This gel will cost about $5 per bottle, which is a considerable expense for the local hospital’s budget. [+]

Director of Growth, Strategic Alliance Initiative, Center for Innovation and Digital Health
Massachusetts General Hospital;
Chief Scientific Officer, Conductscience.com
Latest posts by Shuhan He, MD (see all)
- The Discharge Severity Index: Early Research on ED Readmission Risk Assessment - August 14, 2025
- Suboxone and the Emergency Physician: Get Waivered Training - August 12, 2022
- A Tale of Two Epidemics: COVID-19 and the Opioid Crisis - April 23, 2020