SAEM Clinical Images Series: Tropical Rash
rash

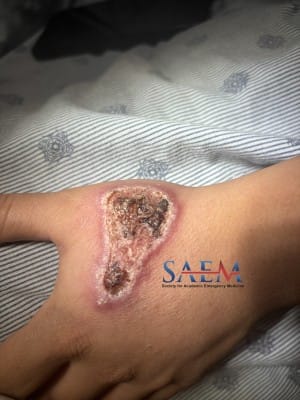
The patient is a 30-year-old female with no past medical history who presents to the Emergency Department with 2 months of non-healing ulcers on multiple parts of her body. She reports getting bitten by flies while traveling in wooded trails from Venezuela through Mexico. She reports the bites started as small scabs that have since enlarged, but they are non-painful or pruritic. She has ulcerative lesions on her left hand, right arm, back, and gluteal areas. She has taken multiple antibiotics from a doctor in Mexico including clindamycin, ceftriaxone, nitrofurantoin, flagyl, and doxycycline. She denies any fevers, chills, nausea, vomiting, weight loss, or night sweats, but given the persistence of the lesions, she comes in for evaluation.
Vitals: BP 143/91 HR 60 R 17 T 98.4 O2sat 100% room air.

General: Well-appearing, breast-feeding her child.

HEENT: Oropharynx is clear, moist mucous membranes, nares clear.
Cardiovascular: Regular rate and rhythm, no murmur.

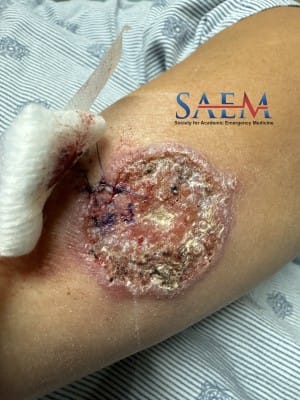
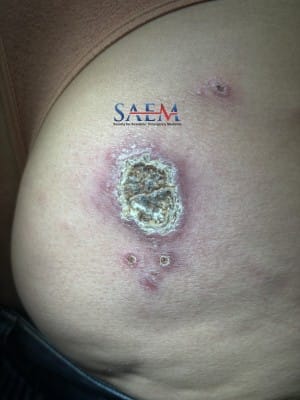
Skin: There are multiple lesions as shown in the images provided. These
are annular ulcerated pink plaques with erythematous indurated borders
and are located diffusely. The larger lesion shown is on her right arm and
is newer than the other lesions shown on her hand and trunk.

CBC: WBC: 7.6 Hgb 12.2

CRP: 0.3

Hep C/HIV/syphilis/GCCT: negative

This patient has cutaneous leishmaniasis.

Cutaneous leishmaniasis (CL) is caused by the protozoan parasite Leishmania and is transmitted through the bite of an infected female sandfly. CL is commonly diagnosed in travelers and immigrants who are susceptible to exposure. The lesions of CL usually begin as small erythematous papules that increases in size and eventually ulcerate and crust over. Lesions generally have distinct borders that are raised and erythematous. The diagnosis can be made based on travel history, lesion appearance, skin biopsy, and serology. Without treatment, the ulcers heal slowly but can leave disfiguring scars. Treatment modalities include pentamidine, amphotericin B, antimoniate, paromomycin, imiquimod, thermotherapy and cryotherapy. Visceral leishmaniasis (VL) is the most serious form of infection and is almost always fatal if untreated. With VL, the parasites directly infect organs including the spleen, liver, bone marrow, and other viscera. Common signs and symptoms of VL include fever, weight loss, fatigue, weakness, night sweats, hepatosplenomegaly, and pancytopenia.

Take-Home Points

  • Cutaneous Leishmaniasis should be suspected in travelers who have been to endemic areas and present with non-healing skin ulcerations. Visceral Leishmaniasis is the most severe form of disease and carries an extremely high mortality rate if untreated.
  • The vector for this disease is the sandfly; diagnosis is made through skin biopsy and direct microscopy of the parasite.

1. Eiras DP, Kirkman LA, Murray HW. Cutaneous Leishmaniasis: Current Treatment Practices in the USA for Returning Travelers. Curr Treat Options Infect Dis. 2015;7(1):52-62. doi:10.1007/s40506-015-0038-4

2. Chappuis, F., Sundar, S., Hailu, A. et al. Visceral leishmaniasis: what are the needs for diagnosis, treatment and control?. Nat Rev Microbiol 5, 873–882 (2007). https://doi.org/10.1038/nrmicro1748
By |2025-10-27T08:26:58-07:00Oct 3, 2025|Dermatology, SAEM Clinical Images|

SAEM Clinical Images Series: When in Doubt, Swab It Out

eczema

A 26-year-old female with a history of atopic dermatitis presents with one week of rash that began on her lower lip but spread over her face, eyelids, and neck, plus one day of fevers and headache. She was seen at an urgent care and referred to the emergency department for evaluation and management of “impetigo.” On presentation, she endorsed nausea, headache, and mild neck pain.

Vitals: Temp 100.7° F; BP 134/85; HR 121; SpO2: 100%

General: Uncomfortable appearing.

Cardiovascular: Tachycardia

Neurological: AOx3. CN II-XII grossly intact. Moves all extremities equally and spontaneously.

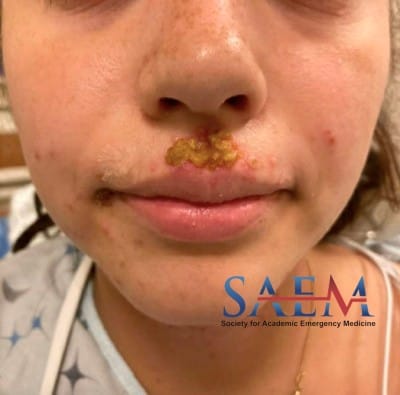
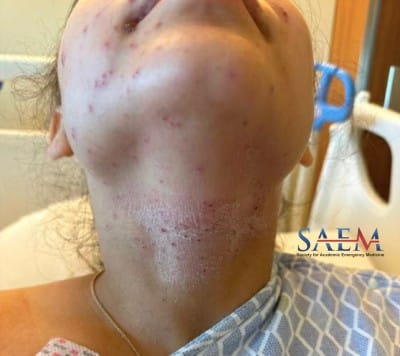
Skin: Upper cutaneous lip – eroded plaque with yellow crust. Bilateral jaw line, cheek, neck, eyelids – eroded papules. Lichenified patches in antecubital fossa bilaterally.

CBC: WBC 10.7; PLT 244

Lactate: 1.31

CSF: Colorless, clear; WBC 1; RBC<1; Protein 23; Glucose 55, Gram Stain Negative

Given the patient’s history of atopic dermatitis and evidence of crusted over papules/pustules on exam, this patient’s presentation was most consistent with diagnosis of eczema herpeticum (EH).

Swabs of the upper lip lesion were positive for HSV1 DNA, which confirmed the diagnosis. Early identification and treatment of EH is critical to preventing dangerous complications including ocular involvement, viremia, meningoencephalitis, hepatitis, or secondary infection with S. aureus resulting in bacteremia. Patients with EH involving the face, periocular areas, or systemic symptoms should be admitted for intravenous antiviral therapy and supportive care.

Take-Home Points

  • The diagnosis of EH is primarily based on history and physical, but the presence of HSV in skin lesions can be confirmed by PCR.
  • Delayed treatment is associated with increased risk of complications and prolonged hospitalization.

1.Wollenberg A, Wetzel S, Burgdorf WH, Haas J. Viral infections in atopic dermatitis: pathogenic aspects and clinical management. J Allergy Clin Immunol. 2003 Oct;112(4):667-74. PMID: 14564342.

2.Aronson PL, Yan AC, Mittal MK, Mohamad Z, Shah SS. Delayed acyclovir and outcomes of children hospitalized with eczema herpeticum. Pediatrics. 2011 Dec;128(6):1161-7. PMID: 22084327.

By |2025-10-27T08:24:25-07:00Sep 29, 2025|Dermatology, SAEM Clinical Images|

ACMT Toxicology Visual Pearl: Danger in the Shallows

In addition to local pain and dermal injury, stings from this marine animal can result in what systemic symptoms?

  1. Acute liver injury
  2. Hypotension, arrhythmia, and cardiac arrest
  3. Nausea, vomiting, and respiratory arrest
  4. Numbness, tingling, and muscle paralysis

[Image courtesy of Guido Gautsch, Wikimedia Commons]

(more…)

ALiEM AIR Series | Vascular Module (2025)

ALiEM AIR Certified seal and Vascular 2025 module shield badge


Welcome to the AIR Vascular Module! After carefully reviewing all relevant posts in the past 12 months from the top 50 sites of the Digital Impact Factor [1], the ALiEM AIR Team is proud to present the highest quality online content related to related to HEENT emergencies in the Emergency Department. 8 blog posts met our standard of online excellence and were approved for residency training by the AIR Series Board. More specifically, we identified 3 AIR and 5 Honorable Mentions. We recommend programs give 4 hours of III credit for this module.


AIR Stamp of Approval and Honorable Mentions


In an effort to truly emphasize the highest quality posts, we have 2 subsets of recommended resources. The AIR stamp of approval is awarded only to posts scoring above a strict scoring cut-off of ≥30 points (out of 35 total), based on our scoring instrument. The other subset is for "Honorable Mention" posts. These posts have been flagged by and agreed upon by AIR Board members as worthwhile, accurate, unbiased, and appropriately referenced despite an average score.


Want asynchronous Individualized Interactive Instruction (III) credit?
Take the AIR quiz at ALiEMU. Free, 1-time login required.

Take the Vascular Module →

Highlighted Quality Posts: Vascular 2025


Site Article Author Date Label
EMCrit Pulmonary embolism diagnosis and treatment of low-risk PE Dr. Josh Farkas March 5, 2024

AIR

EMCrit Aortic dissection Dr. Josh Farkas September 28, 2024 AIR
EMDocs Acute chest syndrome Dr. Rachel Bridwell June 27, 2024 AIR
EMCrit Approach to chest pain Dr. Josh Farkas January 15, 2024 HM
Rebel EM Don't forget the IO in the critically ill patient Dr. Kristen Wiley April 29, 2024 HM
RCEMlearning Cervical artery dissection Dr. Jason Louis January 22, 2024 HM
CanadiEM Is IO cannulation an underutilized method of emergency vascular access Dr. Ming Li October 15, 2024 HM
PedEM Morsels Kounis syndrome Dr. Christyn Magill March 22, 2023 HM


(AIR = Approved Instructional Resource; HM = Honorable Mention)


If you have any questions or comments on the AIR series, or this AIR module, please contact us!

Reference

    1. Lin M, Phipps M, Chan TM, et al. Digital Impact Factor: A Quality Index for Educational Blogs and Podcasts in Emergency Medicine and Critical Care. Ann Emerg Med. 2023;82(1):55-65. doi:10.1016/j.annemergmed.2023.02.011, PMID 36967275


Go to Top